Best Fertility Centre – Dr. Swapna Naik

Author: Swapna

Beta hCG After Embryo Transfer: When to Test & What Results Mean

After embryo transfer, many patients focus on one number: beta hCG. Human chorionic gonadotropin is produced after implantation begins, and a serum beta hCG test can detect pregnancy before ultrasound can show a gestational sac.

The challenge is that one hCG value has limited meaning by itself. The day of testing, embryo stage, laboratory assay and change over time all affect interpretation. A result should therefore be read against the clinic’s timing and followed according to medical advice rather than compared with an isolated number from another patient’s IVF cycle.

For a related clinical pathway, review IVF treatment.

You may also find frozen embryo transfer timeline useful when planning the next step.

What Is Beta hCG?

Beta hCG is the measurable component of human chorionic gonadotropin commonly used to detect and monitor early pregnancy. After implantation, hCG enters the blood and later becomes detectable in urine.

Searches for beta hCG after IVF and hCG levels after embryo transfer often lead to charts with wide ranges. Early values overlap greatly between normal and abnormal pregnancies, so a single value cannot diagnose pregnancy viability.

When to Test After Embryo Transfer

Testing too early can produce a negative result before hCG rises enough to detect. It can also be confusing if an hCG-containing trigger injection was used earlier in treatment.

ASRM’s 2026 RIF review notes routine hCG testing around 9-11 days after blastocyst and cleavage-stage transfers, respectively, although laboratories and clinic protocols vary. Follow the exact test date provided by your fertility team.

Related guide: recurrent implantation failure.

What Does a Positive Beta hCG Mean?

A positive test means hCG has been detected and implantation has occurred to some degree. It does not yet confirm where the pregnancy is located, whether cardiac activity will develop, or whether the pregnancy will continue.

This is why clinics often schedule another hCG test and then ultrasound at the appropriate gestational stage rather than declaring the outcome from the first number.

Why Are Serial hCG Tests Used?

In early pregnancy, clinicians may compare hCG values over time. The expected pattern is not a fixed ‘doubling every 48 hours’ rule for every pregnancy. The rate of rise depends on the starting concentration and the interval between tests.

Serial values can help identify a pattern that warrants closer review, but ultrasound eventually becomes more informative for pregnancy location and development.

For additional context, see fertility specialist.

What If hCG Is Low or Rises Slowly?

A low initial value may still progress normally, while a high value does not guarantee a healthy pregnancy. A slower-than-expected rise can occur with an early intrauterine pregnancy, miscarriage or ectopic pregnancy, so medical follow-up is important.

Do not stop progesterone or other support medication unless the clinic instructs you to do so.

When Does Ultrasound Become Important?

Once the pregnancy is far enough along, transvaginal ultrasound is used to identify the gestational sac and later fetal structures. The timing depends on gestational age, hCG pattern and symptoms.

Urgent assessment is needed for severe pain, heavy bleeding, dizziness, fainting or other symptoms that could indicate an ectopic pregnancy or significant bleeding.

Pregnancy Test After Embryo Transfer: Practical Advice

Use the clinic’s laboratory and timing when possible. Avoid repeated early home tests that may increase anxiety without changing care. Record the transfer date, embryo stage, medications and official beta hCG results.

After the first positive result, ask when the next blood test is needed, when ultrasound is planned and which symptoms should trigger urgent contact.

Related Questions Patients Commonly Search

People researching this topic often use related phrases such as beta hCG after IVF, pregnancy test after embryo transfer, hCG levels after embryo transfer, when to test after embryo transfer, beta hCG IVF, and positive pregnancy test after IVF. These phrases describe overlapping questions, but diagnosis and treatment should be based on the individual clinical situation rather than on a search term.

When to Speak With a Fertility Specialist in Hyderabad

A specialist review is useful when symptoms, test results, age, previous treatment or the length of time trying to conceive make the next decision unclear. Bring previous reports and ask what finding is driving the recommendation, what alternatives are reasonable, and how success will be measured.

You can review book a fertility consultation for more context.

When you are ready for an individual review, IVF process.

Practical Checklist Before Your Consultation

Before the appointment, use this checklist to turn online research into specific questions. It helps the clinician focus on findings that can change management and reduces the risk of ordering tests or procedures only because they are available.

  • What day was the embryo transferred and what developmental stage was it?
  • Was an hCG-containing trigger used earlier in treatment?
  • What is the clinic’s official blood-test date?
  • When should a repeat beta hCG be performed if the first result is positive?
  • Which symptoms require urgent assessment rather than waiting for the next blood test?

Bring previous reports, medication lists and procedure records where relevant. Ask for the reasoning behind each recommendation, the alternatives, the expected benefit and the point at which the plan would be reconsidered.

Frequently Asked Questions

1. What is beta hCG?

It is a blood measurement of human chorionic gonadotropin used to detect and follow early pregnancy.

2. When should beta hCG be tested after embryo transfer?

Follow your clinic’s date. Timing depends on embryo stage and treatment protocol.

3. Can I test at home before the scheduled blood test?

You can, but early home testing may be falsely negative or confusing after an hCG trigger.

4. What is a good first beta hCG number?

There is no single value that guarantees a healthy pregnancy. Timing and the trend over time matter.

5. Should hCG double every 48 hours?

Not every viable pregnancy follows a strict doubling rule. Clinicians interpret the rate of change based on the starting value and interval.

6. What if my first hCG is low?

A low result needs follow-up. Some low values progress normally while others indicate a nonviable or ectopic pregnancy.

7. What if hCG rises slowly?

A slow rise warrants medical follow-up and may require repeat testing and ultrasound.

8. Does high hCG mean twins?

Not reliably. hCG ranges overlap substantially between singleton and multiple pregnancies.

9. Can progesterone affect the hCG result?

Progesterone does not create hCG. An hCG-containing trigger injection, however, can affect very early testing.

10. When can ultrasound confirm the pregnancy?

Ultrasound is scheduled according to gestational age and the clinical situation rather than one universal hCG number.

11. Can hCG rise after a miscarriage?

hCG can remain detectable for a period after a pregnancy stops developing and generally falls over time.

12. When should I seek urgent care?

Seek urgent assessment for severe or one-sided pain, heavy bleeding, fainting, significant dizziness or other concerning symptoms.

Key Takeaway

The best use of information about beta hCG after embryo transfer is to improve the next clinical conversation. Use the article to understand the terminology and decision points, then confirm the diagnosis, evidence, risks and treatment options with the fertility team.

Author: Swapna

Frozen Embryo Transfer Timeline: Step-by-Step FET Cycle Guide

A frozen embryo transfer, or FET, uses an embryo that was previously cryopreserved and later warmed for transfer to the uterus. The exact frozen embryo transfer timeline varies because cycles can be prepared using natural ovulation, modified natural protocols or medication.

Regardless of protocol, the objective is the same: prepare the endometrium and coordinate embryo transfer with the correct biological window. The timing of progesterone is especially important in programmed cycles because embryo stage and endometrial exposure must be synchronized.

For a related clinical pathway, review IVF treatment.

You may also find fertility specialist useful when planning the next step.

Before the FET Cycle Starts

The team reviews embryo information, menstrual history, uterine evaluation and the reason for the frozen transfer. If there are symptoms or previous findings suggesting a cavity problem, additional assessment may be advised.

Baseline ultrasound or blood tests may be used depending on protocol. The clinic also confirms medication instructions and the expected transfer strategy.

Natural FET Cycle

In a natural FET cycle, the team monitors development of a dominant follicle and identifies spontaneous ovulation or coordinates it with a trigger in a modified natural cycle. Transfer is scheduled according to the timing of ovulation and embryo stage.

Natural-cycle FET may suit patients with predictable ovulation, but monitoring and timing remain important.

Related guide: day 3 vs day 5 embryo transfer.

Medicated FET Timeline

In a medicated or programmed cycle, estrogen is commonly used to prepare the endometrium, followed by progesterone. Ultrasound may assess lining development before progesterone is started.

The embryo transfer day is then matched to the number of days of progesterone exposure and the developmental stage of the frozen embryo. Patients should follow the clinic’s timing exactly rather than changing doses or times independently.

Embryo Warming and Transfer Day

On transfer day, the laboratory warms the selected embryo according to its vitrification protocol. Modern vitrification has improved embryo survival, but no laboratory can guarantee that every embryo will survive warming.

If the embryo is suitable, it is loaded into a transfer catheter and placed into the uterus under the clinic’s procedure protocol. Transfer is generally brief and does not usually require anaesthesia.

For additional context, see beta hCG after embryo transfer.

After Frozen Embryo Transfer

Continue prescribed medicines exactly as advised. Routine bed rest has not been shown to create implantation, and most patients can follow the activity guidance given by their clinic.

Symptoms such as mild cramping, bloating or breast tenderness can be caused by progesterone or normal cycle changes and cannot reliably predict whether implantation has occurred.

When Is the Pregnancy Test?

Clinics usually schedule serum beta hCG after enough time has passed for an implanted embryo to produce detectable hormone. Testing too early can create false reassurance or unnecessary alarm.

The exact date depends on embryo stage and clinic protocol. In ASRM’s RIF review, hCG testing is described as routinely performed roughly 9-11 days after blastocyst or cleavage-stage embryo transfer, respectively, but patients should follow the date given by their own clinic.

FET Step by Step: What to Confirm Before You Start

Ask whether your cycle is natural or medicated, what the monitoring schedule is, when progesterone begins, which embryo will be warmed, whether a backup plan exists if warming is unsuccessful, and the exact pregnancy-test date.

A clear FET step by step plan reduces medication errors and makes the cycle easier to follow.

Related Questions Patients Commonly Search

People researching this topic often use related phrases such as FET timeline, frozen embryo transfer process, frozen embryo transfer cycle, FET step by step, medicated FET timeline, and natural FET cycle. These phrases describe overlapping questions, but diagnosis and treatment should be based on the individual clinical situation rather than on a search term.

When to Speak With a Fertility Specialist in Hyderabad

A specialist review is useful when symptoms, test results, age, previous treatment or the length of time trying to conceive make the next decision unclear. Bring previous reports and ask what finding is driving the recommendation, what alternatives are reasonable, and how success will be measured.

You can review thin endometrium IVF for more context.

When you are ready for an individual review, book a fertility consultation.

Practical Checklist Before Your Consultation

Before the appointment, use this checklist to turn online research into specific questions. It helps the clinician focus on findings that can change management and reduces the risk of ordering tests or procedures only because they are available.

  • Is the FET natural, modified-natural or programmed?
  • What monitoring is required before transfer?
  • When exactly should progesterone start, and what happens if a dose is missed?
  • Which embryo is planned for warming and is there a backup embryo?
  • On what date should beta hCG be checked?

Bring previous reports, medication lists and procedure records where relevant. Ask for the reasoning behind each recommendation, the alternatives, the expected benefit and the point at which the plan would be reconsidered.

Frequently Asked Questions

1. What is a frozen embryo transfer?

It is transfer of an embryo that was previously cryopreserved and later warmed.

2. How long does an FET cycle take?

It varies by natural or medicated protocol and by the patient’s menstrual cycle.

3. What is a natural FET?

It times transfer around the patient’s own ovulation.

4. What is a medicated FET?

It uses medication, commonly estrogen and progesterone, to prepare and time the endometrium.

5. Why is progesterone timing important?

The duration of progesterone exposure needs to be synchronized with embryo developmental stage.

6. Can every frozen embryo survive warming?

No. Modern vitrification gives good survival, but survival cannot be guaranteed for every embryo.

7. Is FET painful?

Embryo transfer is usually brief and often causes little or mild discomfort.

8. Do I need bed rest after FET?

Routine prolonged bed rest is generally not required; follow your clinic’s individualized advice.

9. Can symptoms tell whether FET worked?

No. Progesterone and normal cycle changes can mimic early-pregnancy symptoms.

10. When is beta hCG checked?

The clinic schedules testing after enough time has passed for a meaningful result; exact timing depends on embryo stage and protocol.

11. Can I take a home pregnancy test early?

Early home testing can be misleading, especially if hCG trigger medicine was used or the test is done before sufficient time has passed.

12. What happens if the first FET fails?

The team reviews embryo, uterine, hormonal and transfer factors and decides whether further evaluation or another transfer is appropriate.

Key Takeaway

The best use of information about frozen embryo transfer timeline is to improve the next clinical conversation. Use the article to understand the terminology and decision points, then confirm the diagnosis, evidence, risks and treatment options with the fertility team.

Author: Swapna

Day 3 vs Day 5 Embryo Transfer: Which Is Better for IVF?

day 3 vs day 5 embryo transfer

During IVF, embryos can be transferred at different stages of development. A day 3 embryo is usually at the cleavage stage, while a day 5 embryo has ideally progressed to the blastocyst stage. The question ‘day 3 vs day 5 embryo transfer’ sounds simple, but the best timing depends on embryo number, development, laboratory experience and the individual patient’s prognosis.

Blastocyst culture provides additional time to observe embryo development and may improve selection in good-prognosis patients. At the same time, extending culture can result in some patients having no embryo available for transfer. The decision should therefore be individualized rather than presented as day 5 always being better.

For a related clinical pathway, review IVF treatment.

You may also find IVF process useful when planning the next step.

What Happens on Day 3?

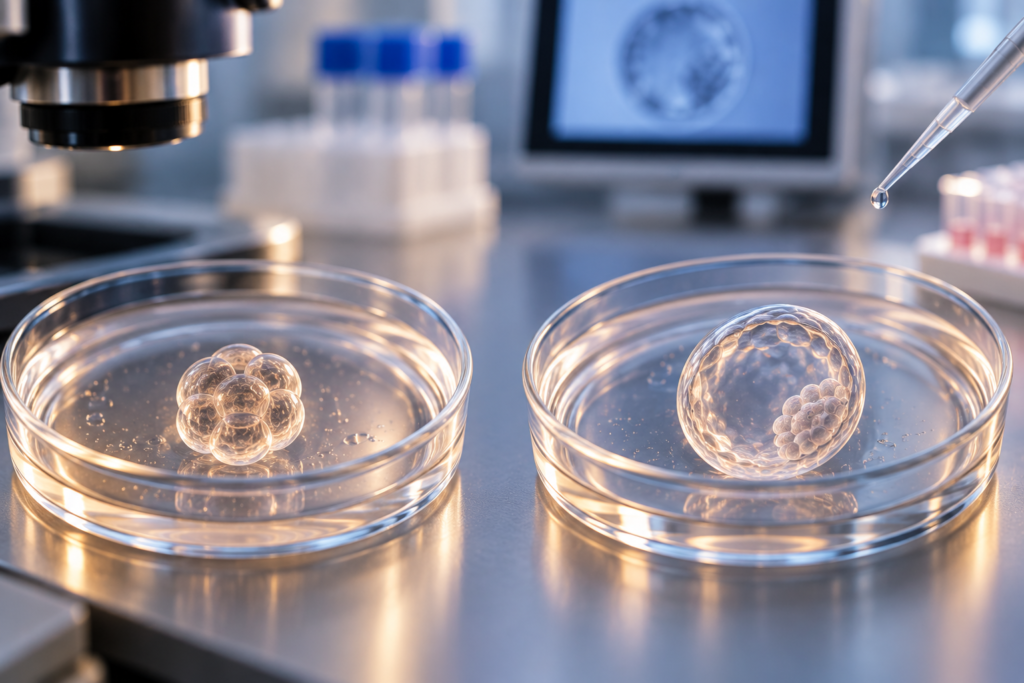
By day 3 after fertilisation, a normally developing embryo is typically in the cleavage stage and contains multiple cells. Embryologists assess cell number, symmetry, fragmentation and other features.

A day 3 embryo transfer may be considered when there are only a small number of embryos, when the laboratory or clinical team believes extended culture may not add useful selection, or for other individualized reasons.

What Happens on Day 5?

By day 5, an embryo that continues to develop may become a blastocyst with an inner cell mass and trophectoderm. Blastocyst transfer is more physiologically aligned with the stage at which the embryo normally reaches the uterus.

Day 5 embryo transfer can allow stronger selection among embryos that have continued to develop, which is one reason blastocyst transfer is widely used.

Related guide: IVF failure reasons.

Potential Advantages of Blastocyst Transfer

ASRM’s committee opinion notes that in good-prognosis patients, blastocyst transfer can be associated with higher live-birth rates when equal numbers of embryos are transferred. It also supports single-embryo transfer strategies because blastocysts may have higher implantation potential.

Another advantage is that embryos which stop developing before blastocyst stage are not selected for transfer. However, laboratory culture does not create embryo quality; it reveals developmental potential.

Potential Limitations of Waiting Until Day 5

Extended culture increases the chance that a patient with only a few embryos may have no embryo to transfer. Older studies found higher cancellation of transfer in unselected patients randomized to blastocyst culture.

The relevance of this risk depends on embryo number, prognosis, laboratory performance and cryopreservation strategy. A day 3 transfer is not automatically a ‘lower-quality’ choice.

For additional context, see frozen embryo transfer timeline.

Does Day 5 Always Have a Higher Success Rate?

Success-rate comparisons can be misleading if they ignore patient selection. Patients who reach blastocyst transfer often already have more embryos or a better prognosis. Cumulative outcome from all fresh and frozen embryos is also different from pregnancy per single transfer.

Day 3 vs blastocyst transfer should therefore be discussed using the patient’s embryo cohort and not only a clinic-wide percentage.

How Does the Clinic Decide?

The team may consider age, number of normally fertilised embryos, day 2-3 development, previous embryo history, whether PGT is planned and the laboratory’s blastocyst culture performance.

Sree Swapna’s IVF page describes embryo development from day 3 cleavage stage to day 5 blastocyst and notes that embryo quality and other factors guide the transfer decision. A personalised discussion is more useful than choosing a day before the embryos have developed.

Related Questions Patients Commonly Search

People researching this topic often use related phrases such as day 3 embryo transfer, day 5 embryo transfer, blastocyst transfer, cleavage stage embryo transfer, day 3 vs blastocyst transfer, and embryo transfer timing. These phrases describe overlapping questions, but diagnosis and treatment should be based on the individual clinical situation rather than on a search term.

When to Speak With a Fertility Specialist in Hyderabad

A specialist review is useful when symptoms, test results, age, previous treatment or the length of time trying to conceive make the next decision unclear. Bring previous reports and ask what finding is driving the recommendation, what alternatives are reasonable, and how success will be measured.

You can review fertility specialist for more context.

When you are ready for an individual review, book an appointment.

Practical Checklist Before Your Consultation

Before the appointment, use this checklist to turn online research into specific questions. It helps the clinician focus on findings that can change management and reduces the risk of ordering tests or procedures only because they are available.

  • How many normally fertilised embryos are available?
  • How are the embryos developing on day 2-3?
  • What is the laboratory’s experience with extended blastocyst culture?
  • Would waiting until day 5 create a meaningful risk of having no embryo to transfer?
  • Is single-embryo transfer appropriate based on prognosis?

Bring previous reports, medication lists and procedure records where relevant. Ask for the reasoning behind each recommendation, the alternatives, the expected benefit and the point at which the plan would be reconsidered.

Frequently Asked Questions

1. What is a day 3 embryo?

It is usually a cleavage-stage embryo that has undergone several cell divisions after fertilisation.

2. What is a day 5 embryo?

A normally developing day 5 embryo may reach the blastocyst stage.

3. Is day 5 embryo transfer always better?

No. It may be advantageous in good-prognosis patients, but the best stage depends on embryo number, development and clinical context.

4. Why would a clinic choose day 3 transfer?

It may be chosen when embryo numbers are limited or when extended culture is not expected to improve selection.

5. Can embryos stop growing between day 3 and day 5?

Yes. Not all cleavage-stage embryos develop into blastocysts.

6. Does waiting to day 5 damage embryos?

Modern culture systems are designed to support blastocyst development, but laboratory quality and embryo biology both matter.

7. Is pregnancy rate higher with blastocyst transfer?

Often higher per transfer in selected good-prognosis groups, but cumulative live birth and patient selection should also be considered.

8. Can a day 3 embryo become a healthy baby?

Yes. Day 3 embryos can result in healthy pregnancies and live births.

9. Is embryo grading the same on day 3 and day 5?

No. Cleavage-stage and blastocyst embryos are assessed using different developmental features.

10. Is PGT done on day 3 embryos?

Modern PGT commonly involves blastocyst-stage biopsy, though laboratory protocols vary.

11. Can a blastocyst be frozen?

Yes. Blastocysts are commonly vitrified for later frozen embryo transfer.

12. How many embryos should be transferred?

Current practice often favors single-embryo transfer in appropriate patients to reduce multiple pregnancy risk; the exact recommendation depends on age and prognosis.

Key Takeaway

The best use of information about day 3 vs day 5 embryo transfer is to improve the next clinical conversation. Use the article to understand the terminology and decision points, then confirm the diagnosis, evidence, risks and treatment options with the fertility team.

Author: Swapna

Why Does IVF Fail? Common Reasons After an Unsuccessful IVF Cycle

An unsuccessful IVF cycle can feel as if the entire treatment failed for one hidden reason. In reality, IVF is a sequence of biological steps: ovarian response, egg retrieval, fertilisation, embryo development, implantation and early pregnancy. A problem can occur at any stage, and sometimes no single cause can be identified.

Understanding IVF failure reasons is most useful when the discussion is tied to the actual cycle data. The number of follicles, mature eggs, fertilisation pattern, embryo development, transfer details and pregnancy testing can show where the treatment pathway narrowed and what may be reasonable to change next.

For a related clinical pathway, review IVF treatment in Hyderabad.

You may also find fertility investigations useful when planning the next step.

IVF Failure Can Mean Different Things

Some cycles are cancelled before egg retrieval because ovarian response is poor or unsafe. Some reach retrieval but produce few or no mature eggs. Others have fertilisation failure, poor embryo development, no embryo suitable for transfer, a negative pregnancy test after transfer, or a pregnancy that later miscarries.

Searches for why IVF fails and failed IVF reasons should therefore begin by defining which stage did not progress. That prevents a generic answer from replacing a meaningful cycle review.

Egg Number and Egg Quality

Age and ovarian reserve influence the expected number of eggs and the chance that eggs are chromosomally competent. AMH helps estimate ovarian response to stimulation but is not a direct measure of egg quality.

A low egg yield may reflect ovarian reserve, stimulation response or cycle-specific variation. An apparently good response can still produce embryos that are chromosomally abnormal. Treatment planning should consider both quantity and age-related biology.

Related guide: recurrent implantation failure causes.

Sperm and Fertilisation Factors

Sperm concentration, motility, morphology and severe male-factor conditions can affect fertilisation. ICSI may be used when there is a clear indication, but it does not eliminate all sperm-related or genetic factors.

If fertilisation was unexpectedly low, the team should review egg maturity, sperm parameters, fertilisation method and laboratory observations before assuming that the next cycle simply needs ‘more ICSI’ or an unproven add-on.

Embryo Development and Transfer

Not every fertilised egg develops into a blastocyst. Embryo attrition is a normal part of IVF biology, though severe or repeated developmental problems may influence future planning.

Day 3 versus day 5 transfer decisions depend on embryo number, development, laboratory performance and the clinical plan. A negative test after a high-quality transfer may still occur because morphology cannot guarantee embryo competence.

For additional context, see low AMH vs egg quality.

Uterine and Endometrial Factors

Polyps, submucosal fibroids, adhesions, hydrosalpinx or other structural problems may affect implantation in selected patients. Endometrial preparation and progesterone timing are also important, especially in frozen embryo transfer cycles.

However, one failed transfer does not automatically justify an extensive implantation-failure work-up. The number and quality of embryos transferred and the patient’s age affect how unexpected the result really is.

What Should a Post-IVF Review Include?

A useful review asks: How many follicles developed? How many eggs were retrieved and mature? How many fertilised normally? How did embryos progress? Was transfer technically straightforward? Was the uterine cavity adequately assessed? Were medications and progesterone timed correctly? Was the pregnancy test performed at the recommended time?

Repeated IVF failure deserves a deeper review, but even then testing should be evidence-based. The objective is to identify modifiable factors rather than to add treatments simply because the previous cycle was unsuccessful.

IVF Failure Reasons Hyderabad: Planning the Next Step

For patients looking for IVF failure reasons Hyderabad guidance, bring the complete embryology and stimulation record to the review. A clinic cannot responsibly estimate the next step from age and AMH alone.

The next plan may involve adjusting stimulation, reviewing fertilisation strategy, treating a uterine finding, changing embryo-transfer timing, using donor gametes in selected cases, or repeating a similar approach when the previous result falls within expected biological variation.

Related Questions Patients Commonly Search

People researching this topic often use related phrases such as why IVF fails, failed IVF reasons, IVF failure after embryo transfer, repeated IVF failure, IVF implantation failure, and IVF failure reasons Hyderabad. These phrases describe overlapping questions, but diagnosis and treatment should be based on the individual clinical situation rather than on a search term.

When to Speak With a Fertility Specialist in Hyderabad

A specialist review is useful when symptoms, test results, age, previous treatment or the length of time trying to conceive make the next decision unclear. Bring previous reports and ask what finding is driving the recommendation, what alternatives are reasonable, and how success will be measured.

You can review day 3 vs day 5 embryo transfer for more context.

When you are ready for an individual review, thin endometrium IVF.

Practical Checklist Before Your Consultation

Before the appointment, use this checklist to turn online research into specific questions. It helps the clinician focus on findings that can change management and reduces the risk of ordering tests or procedures only because they are available.

  • At which stage did the IVF cycle narrow: response, egg maturity, fertilisation, embryo development or implantation?
  • Were sperm and egg factors reviewed together?
  • Was embryo-transfer timing and technique appropriate?
  • Is there evidence of a uterine-cavity issue?
  • What specific change is proposed for the next cycle, and why?

Bring previous reports, medication lists and procedure records where relevant. Ask for the reasoning behind each recommendation, the alternatives, the expected benefit and the point at which the plan would be reconsidered.

Frequently Asked Questions

1. Why does IVF fail even with good embryos?

Embryo appearance cannot reveal every chromosomal or biological factor, and implantation also depends on uterine, hormonal and transfer-related factors.

2. Is age the main IVF failure factor?

Age is a major predictor because it affects egg and embryo chromosomal competence, but it is not the only factor.

3. Does low AMH mean IVF will fail?

No. Low AMH mainly predicts lower ovarian response; it does not by itself determine egg quality or live birth.

4. Can poor sperm cause IVF failure?

Severe sperm problems can affect fertilisation and embryo development, although IVF-ICSI may overcome some fertilisation barriers.

5. Why do embryos stop growing?

Embryos may arrest because of chromosomal, egg, sperm or developmental factors. Some attrition is expected in every IVF cycle.

6. Does a negative test after embryo transfer mean implantation failure?

It means the transfer did not result in a detectable pregnancy. Whether it qualifies as recurrent implantation failure depends on the broader transfer history.

7. Should I do PGT-A after one failed IVF cycle?

Not automatically. The potential benefits and limitations depend on age, embryo number, previous history and treatment goals.

8. Can hysteroscopy help after IVF failure?

It may be useful when there is suspicion of uterine-cavity pathology, but it is not required after every failed cycle.

9. Does thin endometrium cause IVF failure?

A persistently thin lining may be clinically relevant, but treatment depends on the underlying cause and cycle context.

10. Should the IVF protocol always change after failure?

No. Sometimes the previous protocol was appropriate and the result reflected biological probability rather than a correctable mistake.

11. How soon can IVF be repeated?

Timing depends on physical recovery, ovarian response, emotional readiness, diagnosis and the clinician’s review.

12. Can stress alone cause IVF failure?

Stress is common during IVF, but it should not be blamed as the cause of an unsuccessful cycle.

13. What records are needed for a second opinion?

Bring stimulation sheets, hormone and scan data, egg maturity, fertilisation and embryo reports, transfer details, uterine evaluation and pregnancy results.

14. Can IVF work after multiple failures?

Yes. Future success depends on age, embryo availability, diagnosis and what the review identifies.

15. What is the first step after a failed IVF cycle?

Schedule a structured cycle review rather than immediately adding new tests or treatments.

Key Takeaway

The best use of information about IVF failure reasons is to improve the next clinical conversation. Use the article to understand the terminology and decision points, then confirm the diagnosis, evidence, risks and treatment options with the fertility team.

Author: Swapna

Recurrent Implantation Failure: Causes, Tests & Treatment Options After Failed IVF

recurrent implantation failure causes

Recurrent implantation failure is one of the most difficult terms in fertility care because there has historically been no single universally accepted definition. A failed embryo transfer can occur for many reasons, and repeated unsuccessful transfers do not automatically prove that there is one hidden uterine or immune problem.

ASRM’s 2026 committee opinion recommends a probability-based approach to recurrent implantation failure, or RIF, and emphasizes careful review of embryo quality or ploidy, age, uterine factors, treatment details and previous transfers. Importantly, if a detailed review does not reveal a clear correctable cause, extensive testing and unproven treatment are not automatically beneficial.

For a related clinical pathway, review IVF treatment.

You may also find fertility investigations useful when planning the next step.

What Is Recurrent Implantation Failure?

Implantation begins when a blastocyst attaches to and penetrates the endometrium. Clinically, implantation may first be detected by hCG and later by ultrasound. Recurrent implantation failure refers to repeated failure of embryo transfer to achieve expected implantation.

ASRM now recommends defining RIF based on failure of the estimated number of good-quality blastocysts needed to reach a very high cumulative chance of a positive pregnancy test, rather than using a simple fixed number for every patient. Age, embryo testing and embryo quality influence that calculation.

Embryo Factors

Embryo chromosomal abnormality is a major reason for implantation failure, especially as maternal age increases. Even morphologically good embryos can be aneuploid. Embryo development, stage at transfer and laboratory factors also matter.

PGT-A may be discussed in selected patients, particularly when untested embryos are involved, but ASRM notes that it has not been shown to increase live birth for all patients with infertility or specifically for every patient with RIF. It should be a shared decision, not a universal add-on.

Related guide: IVF failure reasons.

Uterine and Endometrial Factors

Polyps, submucosal fibroids, intrauterine adhesions, hydrosalpinx, uterine anomalies and some other structural problems can interfere with implantation. Assessment may involve ultrasound, saline sonography, hysteroscopy or other imaging when indicated.

Thin endometrium or abnormal progesterone exposure may also be relevant in selected cycles, but evaluation should focus on findings that can realistically change management.

Male and Systemic Factors

Male factors can affect fertilisation and embryo development, while general health, smoking and certain medical conditions may influence reproductive outcomes. However, RIF should not become a reason to order every available blood, immune or sperm test.

The right evaluation starts with the details of the IVF cycle: number and stage of embryos transferred, embryo testing, endometrial preparation, transfer technique and previous outcomes.

For additional context, see thin endometrium and IVF.

Which Tests Are Not Routinely Supported?

Patients with repeated IVF failure are often offered immune panels, broad thrombophilia testing, endometrial receptivity tests and multiple add-on therapies. ASRM’s 2026 review concludes that evidence is insufficient for routine use of several such approaches, including routine ERA testing in RIF.

That does not mean no additional test is ever appropriate. It means each test should have a clear indication and a reasonable chance of changing a clinically meaningful decision.

Treatment After Repeated Implantation Failure

Treatment is directed at identified factors. A uterine lesion may be treated, embryo strategy may be reviewed, progesterone exposure may be optimized, and transfer technique can be assessed. If no correctable cause is found, proceeding with further embryo transfer may still be reasonable because many patients ultimately achieve pregnancy.

For recurrent implantation failure Hyderabad care, a second-look review of the complete IVF record is often more useful than immediately purchasing a package of add-ons.

Related Questions Patients Commonly Search

People researching this topic often use related phrases such as recurrent implantation failure, repeated IVF failure, embryo implantation failure causes, implantation failure tests, RIF treatment, and recurrent implantation failure Hyderabad. These phrases describe overlapping questions, but diagnosis and treatment should be based on the individual clinical situation rather than on a search term.

When to Speak With a Fertility Specialist in Hyderabad

A specialist review is useful when symptoms, test results, age, previous treatment or the length of time trying to conceive make the next decision unclear. Bring previous reports and ask what finding is driving the recommendation, what alternatives are reasonable, and how success will be measured.

You can review day 3 vs day 5 embryo transfer for more context.

When you are ready for an individual review, fertility specialist.

Practical Checklist Before Your Consultation

Before the appointment, use this checklist to turn online research into specific questions. It helps the clinician focus on findings that can change management and reduces the risk of ordering tests or procedures only because they are available.

  • How many embryos have been transferred and were they tested or untested?
  • Was the uterine cavity adequately evaluated?
  • Were progesterone exposure and transfer timing appropriate?
  • Is there a clear correctable factor, or are add-on tests being proposed without strong evidence?
  • What is the expected chance with another transfer based on age and embryo information?

Bring previous reports, medication lists and procedure records where relevant. Ask for the reasoning behind each recommendation, the alternatives, the expected benefit and the point at which the plan would be reconsidered.

Frequently Asked Questions

1. What is recurrent implantation failure?

It describes repeated failure of embryo transfer to achieve expected implantation, but the exact definition has varied historically.

2. How many failed transfers count as RIF?

There is no simple number for every patient. ASRM 2026 recommends considering embryo quality or ploidy, age and cumulative expected chance of implantation.

3. Is embryo aneuploidy a major cause?

Yes. Chromosomal abnormalities are an important cause of failed implantation, especially with increasing maternal age.

4. Does a good-looking embryo always implant?

No. Morphology cannot identify every chromosomal or biological factor that affects embryo competence.

5. Should everyone with failed IVF do PGT-A?

No. PGT-A may be discussed in selected cases, but it is not a universal solution and has not been shown to improve live birth for all patients.

6. Is ERA routinely recommended for RIF?

Current ASRM guidance states there is insufficient evidence to support routine ERA testing for RIF.

7. Can polyps or fibroids affect implantation?

Some intracavitary lesions can interfere with implantation and may warrant evaluation or treatment.

8. Does thin endometrium cause IVF failure?

Endometrial thickness is one factor. Its significance depends on the clinical situation, cycle preparation and underlying cause.

9. Are immune treatments proven for RIF?

Routine immunologic therapies are not supported by strong evidence for all patients with RIF.

10. Should sperm DNA fragmentation be checked after failed transfers?

Not automatically. It may be considered in selected male-factor or reproductive situations after specialist review.

11. Can pregnancy still happen after several failed transfers?

Yes. If no correctable cause is found, further embryo transfer may still result in pregnancy.

12. What records should I bring for a RIF review?

Bring stimulation records, embryo reports, PGT results if any, transfer notes, lining and progesterone information, hysteroscopy or imaging reports and prior pregnancy results.

13. Is RIF the same as recurrent miscarriage?

No. RIF refers to failure to establish implantation after embryo transfer, while recurrent pregnancy loss occurs after pregnancies have been established.

14. When should hysteroscopy be considered?

It may be useful when symptoms, imaging or treatment history raise concern about the uterine cavity.

15. What is the most useful first step after repeated failure?

A structured review of the diagnosis, embryos, uterine cavity, cycle preparation and transfer details before ordering broad add-on testing.

Key Takeaway

The best use of information about recurrent implantation failure causes is to improve the next clinical conversation. Use the article to understand the terminology and decision points, then confirm the diagnosis, evidence, risks and treatment options with the fertility team.

Author: Swapna

TESA vs PESA vs Micro-TESE: Which Sperm Retrieval Procedure Is Used?

TESA, PESA and micro-TESE are surgical or needle-based methods used to retrieve sperm when sperm cannot be obtained adequately from the ejaculate. They are not interchangeable procedures. The choice depends mainly on whether the problem is obstruction or impaired sperm production, previous procedures, anatomy and the experience of the treating team.

Understanding TESA vs PESA vs micro-TESE helps patients ask better questions before IVF. The procedure should be selected after the cause of azoospermia or severe male-factor infertility has been evaluated, not simply because one technique sounds more advanced.

For a related clinical pathway, review surgical sperm recovery.

You may also find ICSI treatment useful when planning the next step.

What Is PESA?

Percutaneous epididymal sperm aspiration, or PESA, uses a needle to aspirate fluid from the epididymis. It is generally associated with obstructive azoospermia, where sperm production is occurring but the pathway into the ejaculate is blocked.

Because sperm are being retrieved from the epididymis, PESA is not usually the procedure used when the main problem is severely reduced production inside the testis.

What Is TESA?

Testicular sperm aspiration, or TESA, uses a needle to obtain tissue or fluid directly from the testis. It may be used in selected obstructive cases and other situations depending on the clinical plan.

TESA procedure details vary by centre and diagnosis. The retrieved sample is examined for sperm and, when suitable, sperm may be used for ICSI.

Related guide: obstructive vs non-obstructive azoospermia.

What Is Micro-TESE?

Microdissection testicular sperm extraction, or micro-TESE, is a microsurgical procedure in which the surgeon examines testicular tissue under magnification to identify areas more likely to contain sperm. It is particularly associated with non-obstructive azoospermia.

Micro-TESE for azoospermia is more involved than needle aspiration and should be planned after hormonal, genetic and reproductive evaluation. It does not guarantee sperm retrieval.

PESA vs Micro-TESE: The Main Difference

The simplest difference is location and indication. PESA retrieves sperm from the epididymis and is generally used when sperm production is preserved but blocked. Micro-TESE searches within the testis for focal sperm production when production is severely impaired.

Therefore, choosing between PESA vs micro TESE is not a matter of which has the highest success rate in general. The diagnosis determines which procedure is biologically appropriate.

For additional context, see male infertility treatment.

How Are Retrieved Sperm Used?

Surgically retrieved sperm are commonly used with ICSI. Eggs are collected during an IVF cycle, and an embryologist injects a selected sperm into a mature egg. Coordination between the male procedure and the female IVF cycle is therefore important.

In some cases sperm retrieval may be performed in advance and sperm frozen; in others it may be coordinated with egg retrieval. The strategy depends on the expected chance of finding sperm, laboratory protocols and the couple’s treatment plan.

Questions to Ask Before Sperm Retrieval

Ask what type of azoospermia you have, whether genetic testing is indicated, why a specific retrieval technique is recommended, whether sperm will be frozen, what happens if no sperm are found, and how the procedure is coordinated with IVF.

A clear plan should include both the male procedure and the downstream fertility pathway rather than treating sperm retrieval as an isolated event.

Related Questions Patients Commonly Search

People researching this topic often use related phrases such as TESA vs PESA, PESA vs micro TESE, TESA procedure, PESA procedure, micro TESE for azoospermia, and sperm retrieval procedures. These phrases describe overlapping questions, but diagnosis and treatment should be based on the individual clinical situation rather than on a search term.

When to Speak With a Fertility Specialist in Hyderabad

A specialist review is useful when symptoms, test results, age, previous treatment or the length of time trying to conceive make the next decision unclear. Bring previous reports and ask what finding is driving the recommendation, what alternatives are reasonable, and how success will be measured.

You can review fertility investigations for more context.

When you are ready for an individual review, book a consultation.

Practical Checklist Before Your Consultation

Before the appointment, use this checklist to turn online research into specific questions. It helps the clinician focus on findings that can change management and reduces the risk of ordering tests or procedures only because they are available.

  • What type of azoospermia or sperm-retrieval indication has been diagnosed?
  • Why is PESA, TESA or micro-TESE recommended rather than another technique?
  • What is the plan if no usable sperm are found?
  • Will sperm be used fresh or frozen for ICSI?
  • Should genetic counselling or testing be completed before the procedure?

Bring previous reports, medication lists and procedure records where relevant. Ask for the reasoning behind each recommendation, the alternatives, the expected benefit and the point at which the plan would be reconsidered.

Frequently Asked Questions

1. What is PESA?

PESA is percutaneous epididymal sperm aspiration, a needle-based method of retrieving sperm from the epididymis.

2. What is TESA?

TESA is testicular sperm aspiration, in which a needle is used to obtain material directly from the testis.

3. What is micro-TESE?

Micro-TESE is microsurgical testicular sperm extraction using magnification to search for areas of sperm production.

4. Is PESA used for obstructive azoospermia?

It is commonly considered when sperm production is preserved but an obstruction prevents sperm reaching the ejaculate.

5. Is micro-TESE used for non-obstructive azoospermia?

Yes, it is commonly considered in selected men with severe testicular sperm-production failure.

6. Which is better: TESA or PESA?

Neither is universally better. The correct procedure depends on the diagnosis and where sperm are expected to be found.

7. Does micro-TESE guarantee sperm?

No. Even with microsurgical search, sperm may not be found in every man with non-obstructive azoospermia.

8. Is anaesthesia required?

The type of anaesthesia or sedation depends on the procedure, centre protocol and patient needs.

9. Can retrieved sperm be frozen?

Often yes, when enough usable sperm are found and laboratory protocols permit cryopreservation.

10. Why is ICSI used after sperm retrieval?

ICSI is useful because surgically retrieved sperm are usually limited in number and can be injected directly into mature eggs.

11. Should genetic tests be done before micro-TESE?

Genetic evaluation is important in severe male infertility because some findings affect counselling and the chance of sperm retrieval.

12. Can sperm retrieval and egg retrieval happen on the same day?

Sometimes. Other couples retrieve and freeze sperm earlier. Timing is individualized based on expected retrieval and IVF planning.

Key Takeaway

The best use of information about TESA vs PESA vs micro-TESE is to improve the next clinical conversation. Use the article to understand the terminology and decision points, then confirm the diagnosis, evidence, risks and treatment options with the fertility team.

Author: Swapna

Obstructive vs Non-Obstructive Azoospermia: Causes, Diagnosis & Treatment

Azoospermia means that no sperm are detected in the ejaculate after appropriate laboratory assessment. It does not describe one disease. The most important first distinction is whether sperm production is present but blocked from reaching the semen, or whether sperm production itself is severely impaired.

These two patterns are called obstructive azoospermia and non-obstructive azoospermia. The difference affects genetic evaluation, the chance of sperm retrieval, the procedure used to obtain sperm and how IVF with ICSI may be planned.

For a related clinical pathway, review surgical sperm recovery.

You may also find ICSI treatment useful when planning the next step.

What Is Obstructive Azoospermia?

In obstructive azoospermia, sperm production may be relatively preserved, but a blockage or absence in the reproductive tract prevents sperm from entering the ejaculate. Causes can include congenital absence of the vas deferens, prior infection, surgery, vasectomy or other obstructive conditions.

AUA/ASRM guidance highlights the importance of CFTR testing in men with vasal agenesis or idiopathic obstructive azoospermia because genetic findings can affect counselling for the couple.

What Is Non-Obstructive Azoospermia?

Non-obstructive azoospermia, or NOA, is caused by severely impaired sperm production within the testes. Causes can involve genetic abnormalities, testicular failure, prior chemotherapy, hormonal disorders and other conditions.

Some men with NOA may still have small areas of sperm production that can be found through surgical retrieval, but the likelihood varies by cause and cannot be guaranteed.

Related guide: TESA vs PESA vs micro-TESE.

How Do Doctors Tell the Difference?

The work-up usually starts with confirmation of azoospermia, a reproductive history and physical examination. Hormonal testing, testicular size, ultrasound in selected situations and genetic tests may help classify the cause.

Current guidance does not recommend routine diagnostic testicular biopsy simply to distinguish obstructive from non-obstructive azoospermia. The evaluation should be designed to identify the cause and guide treatment.

Genetic Testing and Counselling

Genetic testing can be particularly important in severe male infertility. Depending on the pattern, testing may include karyotype, Y-chromosome microdeletion analysis or CFTR evaluation. A positive result can affect the chance of sperm retrieval, the potential for transmission to offspring and decisions about reproductive options.

This is why azoospermia treatment should not begin with a procedure alone. Diagnostic classification comes first.

For additional context, see sperm DNA fragmentation.

Sperm Retrieval Options

For obstructive azoospermia, sperm may often be retrieved from the epididymis or testis using procedures such as PESA, TESA or TESE depending on the anatomy and centre’s practice. For NOA, micro-TESE may be considered because it allows microscopic search for areas of sperm production.

The specific technique should be chosen by the treating male-reproductive and fertility team. A procedure name by itself does not predict whether usable sperm will be found.

Azoospermia Treatment Hyderabad and IVF-ICSI

Retrieved sperm are commonly used with ICSI because the sperm count is limited and sperm is obtained surgically. The female partner’s age, ovarian reserve and IVF plan should therefore be considered in parallel with male testing.

Patients searching for azoospermia treatment Hyderabad should ask which type of azoospermia is suspected, what genetic tests are indicated, what retrieval procedure is appropriate, and how the retrieval will be coordinated with IVF.

Related Questions Patients Commonly Search

People researching this topic often use related phrases such as obstructive azoospermia, non obstructive azoospermia, azoospermia causes, azoospermia treatment, sperm retrieval azoospermia, and azoospermia treatment Hyderabad. These phrases describe overlapping questions, but diagnosis and treatment should be based on the individual clinical situation rather than on a search term.

When to Speak With a Fertility Specialist in Hyderabad

A specialist review is useful when symptoms, test results, age, previous treatment or the length of time trying to conceive make the next decision unclear. Bring previous reports and ask what finding is driving the recommendation, what alternatives are reasonable, and how success will be measured.

You can review male infertility treatment for more context.

When you are ready for an individual review, book an appointment.

Practical Checklist Before Your Consultation

Before the appointment, use this checklist to turn online research into specific questions. It helps the clinician focus on findings that can change management and reduces the risk of ordering tests or procedures only because they are available.

  • Has azoospermia been confirmed on repeat semen assessment?
  • Do the examination and hormones suggest obstruction or impaired sperm production?
  • Are karyotype, Y-chromosome microdeletion or CFTR tests indicated?
  • Which sperm-retrieval method fits the suspected diagnosis?
  • How will male treatment be coordinated with the female partner’s IVF plan?

Bring previous reports, medication lists and procedure records where relevant. Ask for the reasoning behind each recommendation, the alternatives, the expected benefit and the point at which the plan would be reconsidered.

Frequently Asked Questions

1. What is azoospermia?

Azoospermia means no sperm are detected in the ejaculate after appropriate semen assessment.

2. What is obstructive azoospermia?

It occurs when sperm production is present but a blockage or missing reproductive-tract structure prevents sperm from reaching the semen.

3. What is non-obstructive azoospermia?

It occurs when sperm production within the testes is severely impaired.

4. Can azoospermia be treated?

Options depend on the cause and may include treating hormonal or obstructive conditions, reconstruction in selected cases, or surgical sperm retrieval with IVF-ICSI.

5. Can sperm be found in obstructive azoospermia?

Often, because sperm production may be preserved, but the retrieval approach depends on anatomy and diagnosis.

6. Can sperm be found in non-obstructive azoospermia?

Sometimes. Surgical retrieval such as micro-TESE may identify sperm in selected men, but success cannot be guaranteed.

7. Is genetic testing needed?

It is often important in severe male infertility. The exact tests depend on whether obstruction, testicular failure or another cause is suspected.

8. What is CFTR testing for?

CFTR testing is relevant in men with congenital absence of the vas deferens and some forms of obstructive azoospermia.

9. What is a Y-chromosome microdeletion test?

It looks for genetic deletions associated with severe sperm-production problems and can help with counselling and retrieval planning.

10. Is testicular biopsy always needed to diagnose the type?

No. AUA/ASRM guidance does not recommend routine diagnostic testicular biopsy solely to distinguish obstructive from non-obstructive azoospermia.

11. Why is ICSI commonly used with surgically retrieved sperm?

ICSI allows an embryologist to inject a single sperm into a mature egg, which is useful when sperm numbers are limited.

12. Should the female partner be evaluated at the same time?

Yes. Coordinating both partners’ evaluation avoids delays and helps plan IVF and sperm retrieval efficiently.

Key Takeaway

The best use of information about obstructive vs non obstructive azoospermia is to improve the next clinical conversation. Use the article to understand the terminology and decision points, then confirm the diagnosis, evidence, risks and treatment options with the fertility team.

Author: Swapna

Varicocele and Male Infertility: Can It Affect Sperm Count & Fertility?

A varicocele is an enlargement of veins within the scrotum, usually around the testicle. Many men with a varicocele have no fertility problem, but in some men a clinical varicocele is associated with abnormal semen parameters and infertility.

The key SEO and patient-care question is not simply whether a varicocele is present. It is whether it is clinically significant in a man who is trying to conceive. A fertility evaluation considers physical examination, semen analysis, reproductive history, the female partner’s fertility factors and how much time is available before deciding whether treatment or assisted reproduction is appropriate.

For a related clinical pathway, review male infertility treatment in Hyderabad.

You may also find semen analysis useful when planning the next step.

How Can Varicocele Affect Fertility?

Varicoceles may alter the temperature and environment around the testicle and have been associated with impaired sperm production and function in some men. Possible semen changes include lower concentration, reduced motility and abnormal morphology.

Searches such as varicocele sperm count, varicocele sperm motility and varicocele infertility reflect these concerns. However, finding a varicocele does not prove it is the only reason for infertility. Semen results and the couple’s complete fertility picture matter.

How Is a Fertility-Relevant Varicocele Diagnosed?

A clinical varicocele is generally identified by physical examination. AUA/ASRM guidance distinguishes a palpable clinical varicocele from a nonpalpable varicocele found only on imaging. This distinction matters because treatment is not recommended simply because an ultrasound detects small dilated veins.

The male evaluation may also include semen analysis and, depending on the findings, hormonal or genetic tests. Testing should answer a treatment question rather than create a long list of abnormalities with no clear relevance.

Related guide: sperm DNA fragmentation test.

When Is Varicocele Treatment Considered?

AUA/ASRM guidance states that surgical varicocelectomy should be considered in men attempting conception who have a palpable varicocele, infertility and abnormal semen parameters, except in azoospermic men. This does not mean every man who meets those features must have surgery.

The decision depends on age and fertility factors in both partners, severity of semen abnormalities, symptoms, duration of infertility and whether waiting for semen improvement would delay a more effective treatment.

Varicocele and Assisted Reproduction

When semen abnormalities are mild, the couple may still be able to conceive naturally or use IUI depending on the female evaluation. More significant male-factor infertility may lead to IVF with ICSI.

Varicocele treatment for fertility should therefore be discussed alongside the couple’s overall plan. Surgery may be useful in selected men, but it takes time for sperm production to reflect changes after treatment, and assisted reproduction may still be needed.

For additional context, see azoospermia treatment options.

What About Varicocele and Azoospermia?

Non-obstructive azoospermia requires specialist evaluation. Current guidance notes that evidence supporting varicocele repair before assisted reproduction in men with clinical varicocele and non-obstructive azoospermia is not definitive.

This is a good example of why an online claim such as ‘varicocele surgery restores fertility’ is too broad. Diagnosis and treatment should be matched to the actual sperm-production problem.

Varicocele Treatment Hyderabad: What to Ask

If you are searching for varicocele treatment Hyderabad because of infertility, ask whether the varicocele is palpable, how abnormal the semen results are, whether repeat semen analysis is needed, and whether other male or female fertility factors change the plan.

The goal is not to treat an ultrasound report; it is to choose the strategy that offers the best balance of time, evidence and fertility potential for the couple.

Related Questions Patients Commonly Search

People researching this topic often use related phrases such as varicocele infertility, varicocele sperm count, varicocele sperm motility, varicocele treatment for fertility, male infertility varicocele, and varicocele treatment Hyderabad. These phrases describe overlapping questions, but diagnosis and treatment should be based on the individual clinical situation rather than on a search term.

When to Speak With a Fertility Specialist in Hyderabad

A specialist review is useful when symptoms, test results, age, previous treatment or the length of time trying to conceive make the next decision unclear. Bring previous reports and ask what finding is driving the recommendation, what alternatives are reasonable, and how success will be measured.

You can review ICSI treatment for more context.

When you are ready for an individual review, Dr. Swapna Naik.

Practical Checklist Before Your Consultation

Before the appointment, use this checklist to turn online research into specific questions. It helps the clinician focus on findings that can change management and reduces the risk of ordering tests or procedures only because they are available.

  • Is the varicocele palpable on examination or seen only on ultrasound?
  • Are semen parameters abnormal on more than one appropriately collected sample?
  • Are there female fertility factors that make time important?
  • What improvement is realistically expected from treatment?
  • When would IVF or ICSI be considered instead of waiting?

Bring previous reports, medication lists and procedure records where relevant. Ask for the reasoning behind each recommendation, the alternatives, the expected benefit and the point at which the plan would be reconsidered.

Frequently Asked Questions

1. What is a varicocele?

It is enlargement of veins in the scrotum, usually around the testicle.

2. Does every varicocele cause infertility?

No. Many men with a varicocele remain fertile.

3. Can varicocele lower sperm count?

A clinical varicocele can be associated with lower sperm concentration in some men.

4. Can varicocele reduce sperm motility?

Yes, reduced motility may occur, but semen changes vary between individuals.

5. How is varicocele diagnosed?

Physical examination is central; ultrasound may be used in selected situations.

6. Should an ultrasound-only varicocele be treated for infertility?

Current AUA/ASRM guidance advises against surgery for nonpalpable varicoceles detected only by imaging.

7. Who may be considered for varicocele repair?

Selected infertile men with a palpable varicocele and abnormal semen parameters may be considered after counselling.

8. How long does fertility treatment take after varicocele surgery?

Sperm production takes time, so semen changes are not immediate. Your clinician should discuss timing in relation to the couple’s age and fertility plan.

9. Can IVF be done without treating varicocele first?

Yes, in selected couples assisted reproduction may be the more appropriate or time-sensitive strategy.

10. Does varicocele cause azoospermia?

It may coexist with non-obstructive azoospermia, but severe sperm-production failure requires a broader evaluation.

11. Can varicocele come back after treatment?

Recurrence is possible and depends partly on technique and individual anatomy.

12. Should both partners be evaluated before varicocele surgery?

Yes. Parallel evaluation helps ensure that the male treatment fits the couple’s overall fertility needs.

Key Takeaway

The best use of information about varicocele and male infertility is to improve the next clinical conversation. Use the article to understand the terminology and decision points, then confirm the diagnosis, evidence, risks and treatment options with the fertility team.

Author: Swapna

Sperm DNA Fragmentation Test: When Is It Needed & What Do Results Mean?

A sperm DNA fragmentation test evaluates damage or breaks within sperm DNA. It is different from a routine semen analysis, which mainly measures semen volume, sperm concentration, motility and morphology. The test is often described using a DNA fragmentation index, or DFI.

DFI testing can be useful in selected fertility situations, but it should not be treated as a universal first-line test for every couple. AUA/ASRM guidance states that sperm DNA fragmentation analysis is not recommended routinely in the initial evaluation of the infertile couple. It may be considered in particular clinical contexts, including recurrent pregnancy loss or selected cases after specialist review.

For a related clinical pathway, review Sperm DNA Fragmentation Index.

You may also find male infertility treatment useful when planning the next step.

What Does a Sperm DNA Fragmentation Test Measure?

Sperm carry paternal genetic material to the egg. DNA fragmentation refers to breaks or damage within that genetic material. Different laboratory methods measure fragmentation in different ways, so a DFI result must be interpreted with the test method and laboratory reference range.

Searches for sperm DNA fragmentation, DFI test and sperm DNA fragmentation index often lead to a single percentage. That percentage is not a stand-alone diagnosis. It needs to be considered alongside semen analysis, reproductive history, female-partner factors and the clinical reason the test was ordered.

When May DFI Testing Be Considered?

Routine testing at the very beginning of every fertility evaluation is not supported by current AUA/ASRM guidance. A specialist may consider it after recurrent pregnancy loss, selected unexplained infertility, repeated treatment failure, or when there are male factors that raise concern about sperm DNA integrity.

Testing is most useful when the result could change counselling or management. Ordering a sperm DNA test for infertility without a clear decision pathway can add cost and anxiety without improving care.

Related guide: varicocele and male infertility.

What Can Be Associated With Higher Fragmentation?

Several factors have been associated with increased sperm DNA fragmentation, including oxidative stress, smoking, some infections, varicocele, heat exposure, advanced paternal age and certain medical or lifestyle factors. However, an association does not prove that one factor is the cause in an individual patient.

A careful history matters because some potentially reversible contributors may be identified. Treatment should address a demonstrated problem rather than simply chasing the DFI number.

What Does High DFI Mean for Fertility?

A high result may be associated with reduced reproductive potential in some settings, but thresholds and predictive value vary by assay. It does not mean pregnancy is impossible. It also does not prove that IVF or ICSI will fail.

High DFI treatment is not one standard protocol. Management may include addressing reversible factors, reviewing medications and lifestyle, treating a clinical varicocele when otherwise indicated, managing infection when present, or considering assisted reproductive strategies based on the complete fertility picture.

For additional context, see obstructive vs non-obstructive azoospermia.

DFI, IVF and ICSI

ICSI helps a selected sperm enter the egg but does not directly repair sperm DNA. In selected severe male-factor cases, clinicians may discuss alternative sperm sources or other strategies, but these decisions require specialist counselling because evidence and indications vary.

A DFI result should therefore be integrated with semen parameters, fertilisation history, embryo development, miscarriage history and female age rather than used as a single trigger for advanced treatment.

How to Prepare for a Useful Consultation

Bring the DFI report with the test method, the recent semen analysis, fertility-treatment history and relevant medical information. Ask why the test was ordered, whether the result is clearly abnormal for that laboratory, what potentially reversible factors exist, and whether changing the plan is expected to improve a meaningful outcome.

For patients considering sperm DNA fragmentation Hyderabad services, the priority should be interpretation by a fertility team rather than testing in isolation.

Related Questions Patients Commonly Search

People researching this topic often use related phrases such as sperm DNA fragmentation, DFI test, sperm DNA fragmentation index, high DFI treatment, sperm DNA test for infertility, and sperm DNA fragmentation Hyderabad. These phrases describe overlapping questions, but diagnosis and treatment should be based on the individual clinical situation rather than on a search term.

When to Speak With a Fertility Specialist in Hyderabad

A specialist review is useful when symptoms, test results, age, previous treatment or the length of time trying to conceive make the next decision unclear. Bring previous reports and ask what finding is driving the recommendation, what alternatives are reasonable, and how success will be measured.

You can review ICSI treatment for more context.

When you are ready for an individual review, book a consultation.

Practical Checklist Before Your Consultation

Before the appointment, use this checklist to turn online research into specific questions. It helps the clinician focus on findings that can change management and reduces the risk of ordering tests or procedures only because they are available.

  • Why is DFI being ordered in this case?
  • Which laboratory method and reference range will be used?
  • Is there a recent semen analysis for comparison?
  • Are there reversible male factors such as a clinical varicocele, infection, medication or smoking exposure?
  • How would a high or normal result change treatment?

Bring previous reports, medication lists and procedure records where relevant. Ask for the reasoning behind each recommendation, the alternatives, the expected benefit and the point at which the plan would be reconsidered.

Frequently Asked Questions

1. What is a sperm DNA fragmentation test?

It is a laboratory test that assesses damage or breaks within sperm DNA, often reported as a DNA fragmentation index or DFI.

2. Is DFI the same as semen analysis?

No. Semen analysis measures parameters such as concentration, motility and morphology, while DFI assesses sperm DNA integrity.

3. Is sperm DNA fragmentation testing required for every infertile couple?

No. AUA/ASRM guidance does not recommend it routinely in the initial evaluation of every couple.

4. When can DFI testing be useful?

It may be considered in selected situations such as recurrent pregnancy loss or other cases where a specialist believes the result could change management.

5. Can a man have normal semen analysis and high DFI?

Yes, because conventional semen parameters and DNA integrity measure different aspects of sperm.

6. What causes high sperm DNA fragmentation?

Possible associations include oxidative stress, smoking, varicocele, heat, infection, age and some medical factors.

7. Can high DFI be treated?

Management depends on the cause and clinical context. There is no single treatment that is appropriate for every high DFI result.

8. Does high DFI mean IVF will fail?

No. It may influence counselling in selected cases, but it does not determine the outcome of an individual IVF cycle.

9. Does ICSI solve DNA fragmentation?

ICSI assists fertilisation but does not repair damaged sperm DNA.

10. Should antioxidants be taken for high DFI?

Do not self-prescribe supplements based only on a DFI result. Evidence and product quality vary, and treatment should be individualized.

11. Can varicocele affect DFI?

Varicocele has been associated with sperm-quality problems and may be relevant in selected men, but treatment decisions depend on examination and the full fertility evaluation.

12. Should the DFI test be repeated?

Sometimes. Repeat testing may be considered when the result is unexpected, when a reversible factor has been treated or when the clinician believes it will change management.

Key Takeaway

The best use of information about sperm DNA fragmentation test is to improve the next clinical conversation. Use the article to understand the terminology and decision points, then confirm the diagnosis, evidence, risks and treatment options with the fertility team.

Author: Swapna

Secondary infertility means difficulty achieving another pregnancy after a previous pregnancy has occurred. It can be unexpected because a past conception often creates the impression that fertility should remain unchanged. In reality, reproductive health can change with time, age, medical conditions, surgery, sperm factors and events that occurred during or after a previous pregnancy.

The evaluation should not assume that the same factor is responsible as before. A structured work-up looks at ovulation, ovarian reserve when relevant, the uterus, fallopian tubes and semen parameters. It also considers how long the couple has been trying, age, menstrual history, previous pregnancy or delivery complications and any new health problems. The goal is to identify a practical next step rather than to rush directly into IVF.

For a related clinical pathway, review fertility investigations.

You may also find IVF treatment in Hyderabad useful when planning the next step.

What Is Secondary Infertility?

Secondary infertility is infertility after at least one previous pregnancy. It may occur even when the earlier pregnancy happened naturally and without difficulty. The term describes the current fertility situation; it does not identify the cause.

Common searches such as secondary infertility, causes of secondary infertility and secondary infertility after first pregnancy reflect the same clinical question: what changed, and what should be assessed now? Causes may involve the female partner, the male partner, both partners or may remain unexplained after standard evaluation.

Common Causes of Secondary Infertility

Age-related changes are important, particularly because egg quantity and chromosomal competence change over time. Ovulation disorders, thyroid or prolactin problems, endometriosis, adenomyosis, uterine polyps or fibroids, and tubal damage can also affect the chance of conception.

Previous pelvic infection, abdominal or pelvic surgery, or complications around a pregnancy can sometimes affect reproductive anatomy. Male factors can also change with time because of varicocele, illness, medicines, anabolic steroid use, heat exposure, smoking or other health conditions. That is why evaluation of both partners is usually more efficient than focusing on only one person.

Related guide: sperm DNA fragmentation test.

When Should You Seek Fertility Evaluation?

For many couples, evaluation is considered after 12 months of regular unprotected intercourse when the female partner is under 35, and earlier when age is 35 or above or when there are known risk factors. A consultation may also be appropriate sooner if periods are very irregular, there is a history of pelvic surgery or endometriosis, a previous ectopic pregnancy, known tubal disease, or concern about sperm quality.

If you are experiencing difficulty conceiving a second child, waiting indefinitely because a previous conception was easy can delay diagnosis. The most useful timing depends on age, reproductive history and known medical factors.

Tests That May Be Recommended

A fertility evaluation may include menstrual and ovulation history, ultrasound, ovarian reserve testing when it will influence treatment planning, and tests of the uterine cavity or fallopian tubes. HSG can assess tubal patency and the outline of the uterine cavity, while ultrasound and hysteroscopy answer different structural questions.

A semen analysis is a core part of evaluating the male partner. Additional male tests are not automatically required for everyone; they are selected when history or semen results suggest a need. The objective is targeted testing that changes management.

For additional context, see HSG vs hysteroscopy.

Treatment Options

Treatment depends on the cause. Ovulation problems may be managed with ovulation induction when appropriate. Tubal or uterine findings may require further assessment or treatment. Mild male-factor or unexplained infertility may sometimes be approached with IUI, while IVF may be considered for blocked tubes, more significant male-factor infertility, reduced time because of age, or unsuccessful simpler treatment.

Secondary infertility treatment should be individualized. A previous natural pregnancy does not mean IVF is unnecessary, but it also does not mean IVF is automatically required.

Secondary Infertility in Hyderabad: Building a Practical Plan

Patients searching for secondary infertility Hyderabad usually need both diagnosis and a treatment pathway. Start with a complete fertility review rather than choosing treatment from an online checklist. Bring previous pregnancy, delivery, surgery, fertility and semen reports if available.

A useful consultation should end with three clear points: what the likely causes are, what tests are genuinely needed next, and what treatment options are reasonable at this stage.

Related Questions Patients Commonly Search

People researching this topic often use related phrases such as secondary infertility, secondary infertility treatment, causes of secondary infertility, difficulty conceiving second child, secondary infertility after first pregnancy, and secondary infertility Hyderabad. These phrases describe overlapping questions, but diagnosis and treatment should be based on the individual clinical situation rather than on a search term.

When to Speak With a Fertility Specialist in Hyderabad

A specialist review is useful when symptoms, test results, age, previous treatment or the length of time trying to conceive make the next decision unclear. Bring previous reports and ask what finding is driving the recommendation, what alternatives are reasonable, and how success will be measured.

You can review fertility specialist for more context.

When you are ready for an individual review, book a fertility consultation.

Practical Checklist Before Your Consultation

Before the appointment, use this checklist to turn online research into specific questions. It helps the clinician focus on findings that can change management and reduces the risk of ordering tests or procedures only because they are available.

  • How long have you been trying for another pregnancy?
  • Have menstrual cycles, pelvic symptoms or medical conditions changed since the previous pregnancy?
  • Was there a previous ectopic pregnancy, pelvic infection, C-section complication or pelvic surgery?
  • Has the male partner had a recent semen analysis?
  • Which test result would actually change the next treatment step?

Bring previous reports, medication lists and procedure records where relevant. Ask for the reasoning behind each recommendation, the alternatives, the expected benefit and the point at which the plan would be reconsidered.

Frequently Asked Questions

1. Can secondary infertility happen after a normal first pregnancy?

Yes. Fertility can change with age, ovulation, tubal health, uterine conditions, sperm factors and new medical issues even after an uncomplicated previous pregnancy.

2. Is secondary infertility common?

It is a recognized form of infertility. WHO distinguishes primary infertility from secondary infertility, which occurs after at least one prior pregnancy.

3. What is the most common cause of secondary infertility?

There is no single cause. Age, ovulation disorders, tubal factors, uterine conditions and male factors are all important possibilities.

4. Does age matter if I conceived easily before?

Yes. Reproductive potential changes with age even when a previous pregnancy occurred without treatment.

5. Can a C-section cause secondary infertility?

A caesarean delivery does not automatically cause infertility. Specific complications, scarring or other pelvic factors may need evaluation when symptoms or history suggest them.

6. Can sperm quality change after the first child?

Yes. Semen parameters can change because of health conditions, medicines, lifestyle factors, varicocele, illness and other causes.

7. Should both partners be tested?

Usually yes. Parallel evaluation can identify male and female factors more efficiently.

8. Is HSG always required?

Not always. Tubal assessment is selected according to history and the treatment being considered.

9. Can PCOS cause secondary infertility?

Yes. If ovulation becomes irregular, PCOS can make conception more difficult, but other causes should still be considered.

10. Does secondary infertility always need IVF?

No. Treatment may range from addressing ovulation or a correctable condition to IUI or IVF depending on the diagnosis.

11. How long should we try before seeing a specialist?

Timing depends on age and risk factors. Earlier review is sensible with irregular cycles, known pelvic disease, previous ectopic pregnancy or male-factor concerns.

12. What should I bring to the first appointment?

Bring previous pregnancy and delivery records when relevant, surgery reports, fertility tests, semen reports, medication lists and menstrual information.

Key Takeaway

The best use of information about secondary infertility causes and treatment is to improve the next clinical conversation. Use the article to understand the terminology and decision points, then confirm the diagnosis, evidence, risks and treatment options with the fertility team.

Scroll to Top

To Book an Appointment

+917670804424 📞 Call Now

Recent Posts