Best Fertility Centre – Dr. Swapna Naik

Author: Swapna

What Is OHSS?

Ovarian hyperstimulation syndrome (OHSS) is a complication of ovarian stimulation in which enlarged ovaries and increased vascular permeability can lead to fluid shifts and symptoms ranging from mild discomfort to serious illness. Modern stimulation protocols have reduced risk, but patients still need to recognize warning signs.

Mild Symptoms After Egg Retrieval

Mild bloating, pelvic discomfort and temporary changes in bowel function can occur after egg retrieval even without clinically significant OHSS. Symptoms should gradually improve. What matters is severity, progression and whether warning signs develop.
OHSS risk is monitored during ovarian stimulation and after egg retrieval.

Warning Signs of Moderate or Severe OHSS

Contact the fertility clinic promptly for rapidly increasing abdominal swelling, significant or worsening pain, persistent vomiting, shortness of breath, dizziness, reduced urine output or rapid weight gain. Severe symptoms require medical assessment because complications can include dehydration, blood clots and breathing problems.

Who Is at Higher Risk?

Risk is higher in patients with a strong ovarian response, high follicle numbers, elevated ovarian-reserve markers and PCOS. ASRM guidance recommends individualized stimulation and preventive strategies for patients at higher risk. The clinic’s PCOS treatment guide provides additional context for patients with PCOS.

How Trigger Choice Can Affect OHSS Risk

The final maturation trigger is one of the tools fertility specialists use to manage OHSS risk. In suitable antagonist cycles, a GnRH agonist trigger can reduce the risk of moderate-to-severe OHSS compared with an hCG-only trigger. Patients can read the related guide on IVF trigger shot timing.

Freeze-All and OHSS Prevention

When risk is high, freezing embryos and postponing transfer may be considered because pregnancy-related hCG can worsen or prolong OHSS. The comparison of fresh vs frozen embryo transfer explains why a freeze-all strategy may be chosen in some cycles.

What to Do at Home

Follow the clinic’s instructions about fluids, activity, medicines and monitoring. Do not self-treat with prescription medicines or drastically change fluid intake without advice. If symptoms are progressing, contact the clinic rather than waiting for the next scheduled appointment.

OHSS and the IVF Journey

OHSS risk is assessed before and during stimulation using ovarian-reserve information and response to medication. The complete IVF process explains how monitoring fits into the cycle and why medication doses may be adjusted.

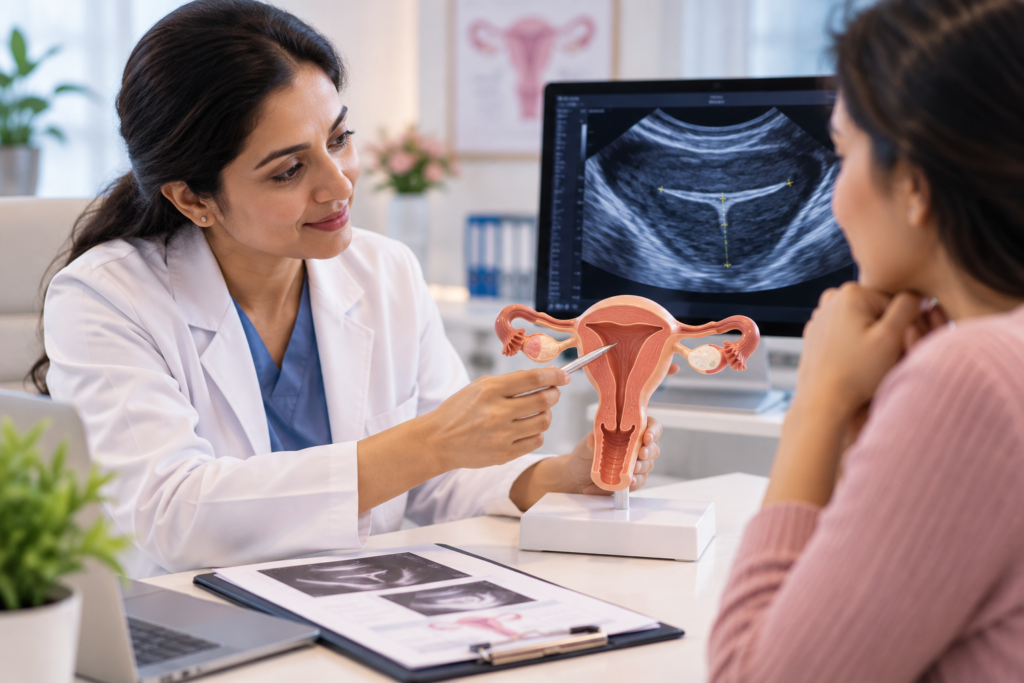
Ultrasound monitoring during ovarian stimulation

Ultrasound monitoring helps fertility teams individualize stimulation and reduce risk.

Related Fertility Topics to Understand

This topic is closely connected with several other parts of fertility evaluation and treatment. For a fuller picture, read the complete IVF process, then compare it with the PCOS treatment guide. Patients moving toward assisted reproduction may also find the AMH blood test guide useful, while the IVF success rate explains another related decision point. If treatment planning is already underway, the frozen embryo transfer timeline can help connect this topic with the next stage of care.

Fertility Guidance From Dr. Swapna Naik

At Sree Swapna Fertility Centre, patients can discuss OHSS symptoms after egg retrieval in the context of their complete fertility history rather than treating one test or symptom in isolation. Dr. Swapna Naik evaluates factors such as age, ovarian reserve, semen parameters, uterine and tubal health, previous treatment response and reproductive goals before recommending the next step. This individualized approach is especially important in fertility care because the same finding can have different implications for different patients.

Frequently Asked Questions

What is OHSS?

Ohss Symptoms After Egg Retrieval refers to a fertility-related concept that should be interpreted in the context of age, symptoms, test results and the couple’s overall treatment plan. A fertility specialist can explain what it means for an individual case.

What causes OHSS after IVF?

Several factors can contribute, and the exact cause may differ from one patient to another. Evaluation usually combines medical history, examination and targeted fertility tests rather than relying on one symptom or one laboratory value.

When do OHSS symptoms start?

Timing is individualized and can depend on the menstrual cycle, stimulation response, laboratory results and the treatment protocol. Follow the schedule given by the treating fertility team rather than changing medicines or appointments independently.

Is bloating normal after egg retrieval?

There is no single number that is ideal for everyone. Reference ranges vary by laboratory, age, treatment stage and clinical context, so results should be interpreted alongside ultrasound findings and other fertility tests.

What are mild OHSS symptoms?

The answer depends on the individual fertility history and clinical findings. For OHSS symptoms after egg retrieval, decisions are best made after reviewing the relevant tests, symptoms, age and reproductive goals with a fertility specialist.

What are severe OHSS symptoms?

The answer depends on the individual fertility history and clinical findings. For OHSS symptoms after egg retrieval, decisions are best made after reviewing the relevant tests, symptoms, age and reproductive goals with a fertility specialist.

When should I call the clinic after egg retrieval?

Timing is individualized and can depend on the menstrual cycle, stimulation response, laboratory results and the treatment protocol. Follow the schedule given by the treating fertility team rather than changing medicines or appointments independently.

Can OHSS cause shortness of breath?

Several factors can contribute, and the exact cause may differ from one patient to another. Evaluation usually combines medical history, examination and targeted fertility tests rather than relying on one symptom or one laboratory value.

Can OHSS cause rapid weight gain?

Several factors can contribute, and the exact cause may differ from one patient to another. Evaluation usually combines medical history, examination and targeted fertility tests rather than relying on one symptom or one laboratory value.

Can OHSS reduce urine output?

The answer depends on the individual fertility history and clinical findings. For OHSS symptoms after egg retrieval, decisions are best made after reviewing the relevant tests, symptoms, age and reproductive goals with a fertility specialist.

Who is at high risk of OHSS?

Safety depends on the procedure, medical history and treatment protocol. Patients should discuss expected side effects, uncommon complications and warning symptoms with their fertility specialist before starting treatment.

Does PCOS increase OHSS risk?

Safety depends on the procedure, medical history and treatment protocol. Patients should discuss expected side effects, uncommon complications and warning symptoms with their fertility specialist before starting treatment.

Does high AMH increase OHSS risk?

Safety depends on the procedure, medical history and treatment protocol. Patients should discuss expected side effects, uncommon complications and warning symptoms with their fertility specialist before starting treatment.

Can a trigger shot affect OHSS risk?

Safety depends on the procedure, medical history and treatment protocol. Patients should discuss expected side effects, uncommon complications and warning symptoms with their fertility specialist before starting treatment.

Can freeze-all reduce OHSS risk?

Safety depends on the procedure, medical history and treatment protocol. Patients should discuss expected side effects, uncommon complications and warning symptoms with their fertility specialist before starting treatment.

How is OHSS treated?

The answer depends on the individual fertility history and clinical findings. For OHSS symptoms after egg retrieval, decisions are best made after reviewing the relevant tests, symptoms, age and reproductive goals with a fertility specialist.

Does OHSS require hospitalization?

The answer depends on the individual fertility history and clinical findings. For OHSS symptoms after egg retrieval, decisions are best made after reviewing the relevant tests, symptoms, age and reproductive goals with a fertility specialist.

Can OHSS happen after frozen embryo transfer?

The answer depends on the individual fertility history and clinical findings. For OHSS symptoms after egg retrieval, decisions are best made after reviewing the relevant tests, symptoms, age and reproductive goals with a fertility specialist.

How long does OHSS last?

Timing is individualized and can depend on the menstrual cycle, stimulation response, laboratory results and the treatment protocol. Follow the schedule given by the treating fertility team rather than changing medicines or appointments independently.

Can OHSS be prevented completely?

The answer depends on the individual fertility history and clinical findings. For OHSS symptoms after egg retrieval, decisions are best made after reviewing the relevant tests, symptoms, age and reproductive goals with a fertility specialist.

Conclusion

Most post-retrieval discomfort is mild, but OHSS can become serious. Patients should know their individual risk, follow the clinic’s prevention plan and seek assessment quickly when symptoms are worsening or involve breathing, urine output, vomiting or rapid abdominal swelling.

Medical References

• World Health Organization: Guideline for the prevention, diagnosis and treatment of infertility (2025)

• ESHRE: Ovarian Stimulation for IVF/ICSI guideline update (2025)

• American Society for Reproductive Medicine: Practice Guidance

Medical review recommended before publication. Information is educational and does not replace individualized medical advice.

Author: Swapna

Why Symptoms After Transfer Are Hard to Interpret

After embryo transfer, many patients closely monitor every cramp, twinge and change in discharge. Unfortunately, symptoms cannot reliably confirm whether implantation has occurred. Progesterone, estrogen, the transfer procedure and normal premenstrual changes can all produce sensations similar to early pregnancy.

Mild Cramping

Mild pelvic cramping can occur after transfer and does not automatically indicate success or failure. Severe or worsening pain is different and should be discussed with the clinic, particularly when it is accompanied by heavy bleeding, breathing difficulty or significant abdominal swelling.

Fertility consultation after embryo transfer

Symptoms after embryo transfer cannot reliably confirm whether implantation occurred.

Spotting or Light Bleeding

Light spotting may occur for several reasons, including cervical irritation or hormonal changes. It is sometimes described as implantation bleeding, but bleeding pattern alone cannot diagnose implantation. Medication should not be stopped because of spotting unless the fertility team advises it.

Breast Tenderness, Fatigue and Bloating

These symptoms can occur with progesterone and other fertility medicines. They can also occur in early pregnancy, which is why they are not useful as a home diagnostic test. The article on progesterone after embryo transfer explains how luteal-support medication can create pregnancy-like symptoms.

What If There Are No Symptoms?

No symptoms after embryo transfer is also common and does not mean the cycle has failed. Implantation is a microscopic process, and many successful pregnancies begin without noticeable changes.

When to Test for Pregnancy

The clinic schedules testing based on embryo stage and transfer date. Testing too early can cause confusion, especially if hCG was used in the treatment cycle. The existing beta hCG after embryo transfer guide explains how blood testing is interpreted.

Symptoms After Fresh vs Frozen Transfer

Symptoms can vary because medication exposure differs between protocols, but they remain unreliable indicators of implantation. Patients comparing protocols can review fresh vs frozen embryo transfer and the existing frozen embryo transfer timeline.

When to Contact the Clinic Urgently

Seek medical advice for heavy bleeding, severe or one-sided pain, fainting, shortness of breath, fever, rapidly increasing abdominal swelling, persistent vomiting or reduced urine output. After a stimulated cycle, some of these symptoms can be associated with complications such as OHSS rather than implantation.

Ultrasound review during fertility treatment

Clinical follow-up and scheduled pregnancy testing are more reliable than symptom-checking.

Related Fertility Topics to Understand

This topic is closely connected with several other parts of fertility evaluation and treatment. For a fuller picture, read the beta hCG after embryo transfer, then compare it with the frozen embryo transfer timeline. Patients moving toward assisted reproduction may also find the complete IVF process useful, while the recurrent implantation failure explains another related decision point. If treatment planning is already underway, the IVF failure reasons can help connect this topic with the next stage of care.

Fertility Guidance From Dr. Swapna Naik

At Sree Swapna Fertility Centre, patients can discuss implantation symptoms after embryo transfer in the context of their complete fertility history rather than treating one test or symptom in isolation. Dr. Swapna Naik evaluates factors such as age, ovarian reserve, semen parameters, uterine and tubal health, previous treatment response and reproductive goals before recommending the next step. This individualized approach is especially important in fertility care because the same finding can have different implications for different patients.

Frequently Asked Questions

What are implantation symptoms after embryo transfer?

The answer depends on the individual fertility history and clinical findings. For implantation symptoms after embryo transfer, decisions are best made after reviewing the relevant tests, symptoms, age and reproductive goals with a fertility specialist.

Can cramping mean implantation after IVF?

It can influence IVF planning, but its importance depends on the broader clinical picture. The fertility team may adjust stimulation, embryo-transfer timing, medication support or additional evaluation based on the patient’s diagnosis.

Is spotting normal after embryo transfer?

There is no single number that is ideal for everyone. Reference ranges vary by laboratory, age, treatment stage and clinical context, so results should be interpreted alongside ultrasound findings and other fertility tests.

Does implantation bleeding happen after IVF?

It can influence IVF planning, but its importance depends on the broader clinical picture. The fertility team may adjust stimulation, embryo-transfer timing, medication support or additional evaluation based on the patient’s diagnosis.

Can breast tenderness mean pregnancy after transfer?

Pregnancy and live-birth chances depend on multiple factors, including age, ovarian reserve, sperm factors, embryo quality, uterine health and the underlying diagnosis. No single test, medication or add-on can guarantee success.

Can progesterone cause pregnancy symptoms?

Several factors can contribute, and the exact cause may differ from one patient to another. Evaluation usually combines medical history, examination and targeted fertility tests rather than relying on one symptom or one laboratory value.

Is bloating normal after embryo transfer?

There is no single number that is ideal for everyone. Reference ranges vary by laboratory, age, treatment stage and clinical context, so results should be interpreted alongside ultrasound findings and other fertility tests.

Is fatigue normal after embryo transfer?

There is no single number that is ideal for everyone. Reference ranges vary by laboratory, age, treatment stage and clinical context, so results should be interpreted alongside ultrasound findings and other fertility tests.

What if I have no symptoms after embryo transfer?

The answer depends on the individual fertility history and clinical findings. For implantation symptoms after embryo transfer, decisions are best made after reviewing the relevant tests, symptoms, age and reproductive goals with a fertility specialist.

Can symptoms predict IVF success?

Pregnancy and live-birth chances depend on multiple factors, including age, ovarian reserve, sperm factors, embryo quality, uterine health and the underlying diagnosis. No single test, medication or add-on can guarantee success.

When does implantation happen after embryo transfer?

Timing is individualized and can depend on the menstrual cycle, stimulation response, laboratory results and the treatment protocol. Follow the schedule given by the treating fertility team rather than changing medicines or appointments independently.

When should I take a pregnancy test after transfer?

Pregnancy and live-birth chances depend on multiple factors, including age, ovarian reserve, sperm factors, embryo quality, uterine health and the underlying diagnosis. No single test, medication or add-on can guarantee success.

Can a home pregnancy test be done early?

Pregnancy and live-birth chances depend on multiple factors, including age, ovarian reserve, sperm factors, embryo quality, uterine health and the underlying diagnosis. No single test, medication or add-on can guarantee success.

Can hCG trigger cause a false-positive test?

Several factors can contribute, and the exact cause may differ from one patient to another. Evaluation usually combines medical history, examination and targeted fertility tests rather than relying on one symptom or one laboratory value.

Are symptoms different after frozen embryo transfer?

The answer depends on the individual fertility history and clinical findings. For implantation symptoms after embryo transfer, decisions are best made after reviewing the relevant tests, symptoms, age and reproductive goals with a fertility specialist.

Are symptoms different after fresh transfer?

The answer depends on the individual fertility history and clinical findings. For implantation symptoms after embryo transfer, decisions are best made after reviewing the relevant tests, symptoms, age and reproductive goals with a fertility specialist.

Can I have period-like cramps and still be pregnant?

Pregnancy and live-birth chances depend on multiple factors, including age, ovarian reserve, sperm factors, embryo quality, uterine health and the underlying diagnosis. No single test, medication or add-on can guarantee success.

When is bleeding after transfer concerning?

Timing is individualized and can depend on the menstrual cycle, stimulation response, laboratory results and the treatment protocol. Follow the schedule given by the treating fertility team rather than changing medicines or appointments independently.

When should severe pain after transfer be reported?

Timing is individualized and can depend on the menstrual cycle, stimulation response, laboratory results and the treatment protocol. Follow the schedule given by the treating fertility team rather than changing medicines or appointments independently.

What is the most reliable way to know whether implantation occurred?

Implantation Symptoms After Embryo Transfer refers to a fertility-related concept that should be interpreted in the context of age, symptoms, test results and the couple’s overall treatment plan. A fertility specialist can explain what it means for an individual case.

Conclusion

Symptoms after embryo transfer are common but unreliable. The most useful approach is to continue prescribed medicines, follow the clinic’s testing schedule and report significant warning symptoms rather than using day-to-day sensations as a pregnancy test.

Medical References

• World Health Organization: Guideline for the prevention, diagnosis and treatment of infertility (2025)

• ESHRE: Ovarian Stimulation for IVF/ICSI guideline update (2025)

• American Society for Reproductive Medicine: Practice Guidance

Medical review recommended before publication. Information is educational and does not replace individualized medical advice.
Author: Swapna

Why Embryos Are Graded

Embryo grading is a laboratory method used to describe how embryos look and develop. It helps embryologists communicate developmental features and prioritize embryos for transfer or freezing. Grading is useful, but it is not a guarantee of chromosome status, implantation or live birth.

Day 3 Embryos and Blastocysts Are Graded Differently

Cleavage-stage embryos are assessed using features such as cell number, symmetry and fragmentation. Blastocysts are commonly described using an expansion stage plus letters for the inner cell mass and trophectoderm. The site’s Day 3 vs Day 5 embryo transfer guide explains why embryo stage is a separate decision from embryo grade.

Embryo grading describes development and morphology; it does not guarantee implantation or live birth.

What the Number in a Blastocyst Grade Means

The number generally describes how expanded the blastocyst is, while the letters describe the appearance of different cell groups. Systems can vary slightly between laboratories, so a grade should always be interpreted according to the clinic’s embryology system.

What Grades Like 3AA or 4AA Mean

In a commonly used blastocyst system, a grade such as 3AA or 4AA combines the expansion stage with assessments of the inner cell mass and trophectoderm. An apparently high morphological grade can be encouraging, but even high-grade embryos may not implant, while lower-graded embryos can still result in healthy births.

Embryo Grade vs Genetic Status

Morphology does not directly reveal whether an embryo is chromosomally normal. Genetic testing, when clinically considered, answers a different question. Patients should avoid treating a visual grade as a genetic diagnosis.

How Embryo Grading Influences Transfer

When multiple embryos are available, grading may help prioritize which embryo to transfer first. The choice also considers the patient’s age, previous treatment, embryo stage, genetic testing if performed, and the goal of reducing multiple pregnancy. The IVF process guide shows how embryology fits into the full treatment cycle.

Frozen Embryos and Grading

Embryos selected for freezing are assessed according to laboratory criteria. After thawing, the laboratory confirms survival and development before transfer. Patients planning FET can review the frozen embryo transfer timeline.

Why a Grade Should Not Be Read as a Percentage

A grade is a descriptive laboratory category, not a personal success rate. Pregnancy chances depend on age, embryo biology, uterine factors and treatment history. The clinic’s IVF success rate guide explains why success statistics need context.

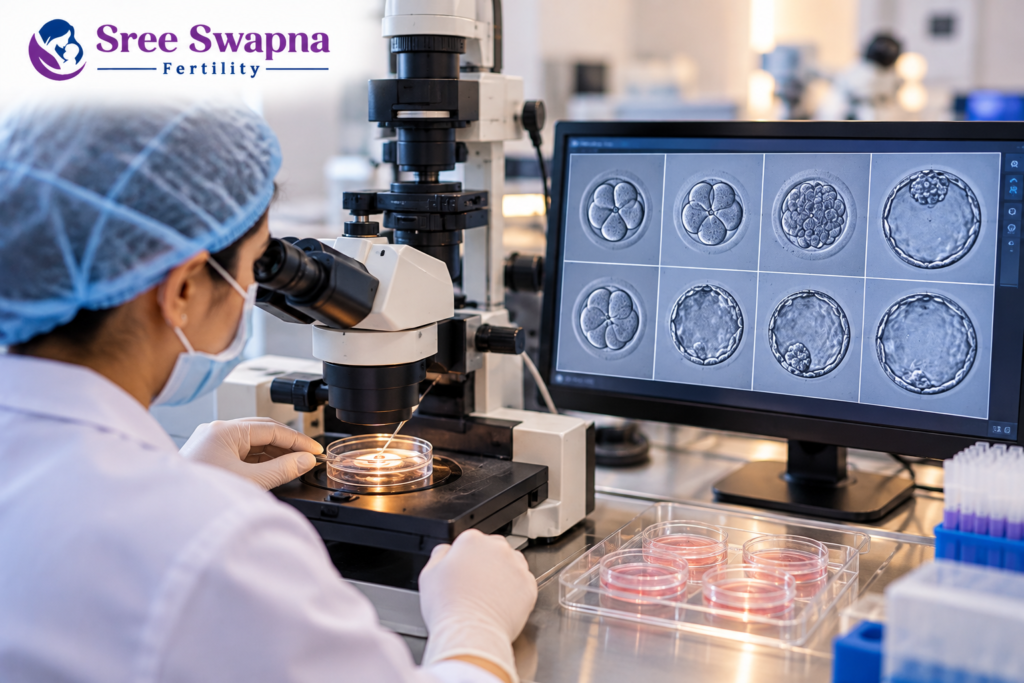
Laboratory microscopy used in embryo assessment

Embryologists assess developing embryos using laboratory criteria.

Related Fertility Topics to Understand

This topic is closely connected with several other parts of fertility evaluation and treatment. For a fuller picture, read the Day 3 vs Day 5 embryo transfer, then compare it with the complete IVF process. Patients moving toward assisted reproduction may also find the IVF success rate useful, while the frozen embryo transfer timeline explains another related decision point. If treatment planning is already underway, the IVF failure reasons can help connect this topic with the next stage of care.

Fertility Guidance From Dr. Swapna Naik

At Sree Swapna Fertility Centre, patients can discuss embryo grading IVF in the context of their complete fertility history rather than treating one test or symptom in isolation. Dr. Swapna Naik evaluates factors such as age, ovarian reserve, semen parameters, uterine and tubal health, previous treatment response and reproductive goals before recommending the next step. This individualized approach is especially important in fertility care because the same finding can have different implications for different patients.

Frequently Asked Questions

What is embryo grading in IVF?

Embryo Grading Ivf refers to a fertility-related concept that should be interpreted in the context of age, symptoms, test results and the couple’s overall treatment plan. A fertility specialist can explain what it means for an individual case.

How are Day 3 embryos graded?

The answer depends on the individual fertility history and clinical findings. For embryo grading IVF, decisions are best made after reviewing the relevant tests, symptoms, age and reproductive goals with a fertility specialist.

How are blastocysts graded?

The answer depends on the individual fertility history and clinical findings. For embryo grading IVF, decisions are best made after reviewing the relevant tests, symptoms, age and reproductive goals with a fertility specialist.

What does 3AA mean in IVF?

Embryo Grading Ivf refers to a fertility-related concept that should be interpreted in the context of age, symptoms, test results and the couple’s overall treatment plan. A fertility specialist can explain what it means for an individual case.

What does 4AA mean in IVF?

Embryo Grading Ivf refers to a fertility-related concept that should be interpreted in the context of age, symptoms, test results and the couple’s overall treatment plan. A fertility specialist can explain what it means for an individual case.

Is a 5AA embryo better than a 4AA embryo?

The answer depends on the individual fertility history and clinical findings. For embryo grading IVF, decisions are best made after reviewing the relevant tests, symptoms, age and reproductive goals with a fertility specialist.

What do the letters in blastocyst grading mean?

The answer depends on the individual fertility history and clinical findings. For embryo grading IVF, decisions are best made after reviewing the relevant tests, symptoms, age and reproductive goals with a fertility specialist.

What does the number in a blastocyst grade mean?

Embryo Grading Ivf refers to a fertility-related concept that should be interpreted in the context of age, symptoms, test results and the couple’s overall treatment plan. A fertility specialist can explain what it means for an individual case.

Can a low-grade embryo become a healthy baby?

The answer depends on the individual fertility history and clinical findings. For embryo grading IVF, decisions are best made after reviewing the relevant tests, symptoms, age and reproductive goals with a fertility specialist.

Does embryo grade predict implantation?

The answer depends on the individual fertility history and clinical findings. For embryo grading IVF, decisions are best made after reviewing the relevant tests, symptoms, age and reproductive goals with a fertility specialist.

Does embryo grade show chromosome status?

The answer depends on the individual fertility history and clinical findings. For embryo grading IVF, decisions are best made after reviewing the relevant tests, symptoms, age and reproductive goals with a fertility specialist.

Is embryo grading the same as PGT?

The answer depends on the individual fertility history and clinical findings. For embryo grading IVF, decisions are best made after reviewing the relevant tests, symptoms, age and reproductive goals with a fertility specialist.

Can embryo grades change?

The answer depends on the individual fertility history and clinical findings. For embryo grading IVF, decisions are best made after reviewing the relevant tests, symptoms, age and reproductive goals with a fertility specialist.

How are frozen embryos graded?

The answer depends on the individual fertility history and clinical findings. For embryo grading IVF, decisions are best made after reviewing the relevant tests, symptoms, age and reproductive goals with a fertility specialist.

Does embryo grade affect which embryo is transferred first?

The answer depends on the individual fertility history and clinical findings. For embryo grading IVF, decisions are best made after reviewing the relevant tests, symptoms, age and reproductive goals with a fertility specialist.

Can a good-grade embryo fail to implant?

The answer depends on the individual fertility history and clinical findings. For embryo grading IVF, decisions are best made after reviewing the relevant tests, symptoms, age and reproductive goals with a fertility specialist.

Can a lower-grade embryo implant successfully?

Pregnancy and live-birth chances depend on multiple factors, including age, ovarian reserve, sperm factors, embryo quality, uterine health and the underlying diagnosis. No single test, medication or add-on can guarantee success.

Is Day 5 always better than Day 3?

The answer depends on the individual fertility history and clinical findings. For embryo grading IVF, decisions are best made after reviewing the relevant tests, symptoms, age and reproductive goals with a fertility specialist.

Should embryo grade determine whether an embryo is discarded?

The answer depends on the individual fertility history and clinical findings. For embryo grading IVF, decisions are best made after reviewing the relevant tests, symptoms, age and reproductive goals with a fertility specialist.

What questions should I ask the embryologist about embryo grading?

The answer depends on the individual fertility history and clinical findings. For embryo grading IVF, decisions are best made after reviewing the relevant tests, symptoms, age and reproductive goals with a fertility specialist.

Conclusion

Embryo grading is a useful way to describe development and support laboratory decisions, but it should not be treated as a prediction of a baby. The grade is one piece of information that must be interpreted alongside age, embryo stage, genetics when tested, and the overall fertility history.

Medical References

• World Health Organization: Guideline for the prevention, diagnosis and treatment of infertility (2025)

• ESHRE: Ovarian Stimulation for IVF/ICSI guideline update (2025)

• American Society for Reproductive Medicine: Practice Guidance

Medical review recommended before publication. Information is educational and does not replace individualized medical advice.

Author: Swapna

What Is an Endometrial Polyp?

An endometrial polyp is an overgrowth of tissue arising from the lining of the uterus. Polyps vary in size, number and location. Some are found incidentally during an ultrasound, while others are investigated because of irregular bleeding, infertility or an abnormal uterine-cavity finding. The presence of a polyp does not automatically mean it is the cause of infertility, so the finding should be interpreted alongside age, ovulation, tubal health and sperm factors.

From a fertility perspective, the most relevant question is whether a polyp changes the uterine cavity where an embryo may implant. A small lesion in one patient may have little clinical importance, while a larger or strategically located polyp may be more significant. This is why a fertility specialist evaluates the entire reproductive history rather than treating a scan report in isolation.

Uterus illustration showing a focal endometrial polyp-like lesion

Endometrial polyps are focal growths arising from the uterine lining.

Can Endometrial Polyps Affect Fertility or Implantation?

Endometrial polyps may interfere with the uterine environment in some patients. Possible mechanisms include local inflammation, altered endometrial receptivity and physical distortion of the cavity. However, fertility is multifactorial. A patient with a polyp may also have diminished ovarian reserve, tubal disease, endometriosis or a male-factor issue, and those factors may contribute more strongly to the delay in conception.

For patients with repeated implantation problems, uterine-cavity assessment may be one part of a wider review. Read the existing Sree Swapna guide on recurrent implantation failure to understand why embryo, uterine, endometrial and treatment factors are considered together.

How Are Endometrial Polyps Diagnosed?

Transvaginal ultrasound is often the first test to suggest an endometrial polyp. Depending on the timing of the scan and the appearance of the cavity, a saline infusion sonography or hysteroscopy may provide a clearer view. Hysteroscopy has the advantage of directly visualizing the uterine cavity and can sometimes diagnose and treat a suitable polyp during the same procedure.

Different fertility tests answer different questions. HSG is mainly used to evaluate fallopian-tube patency and also outlines the cavity, while hysteroscopy directly examines the inside of the uterus. Patients can compare these investigations in the existing HSG vs hysteroscopy article.

When Is Hysteroscopic Polyp Removal Considered?

Hysteroscopic polypectomy is a minimally invasive procedure in which a camera and fine instruments are passed through the cervix to remove a polyp from inside the uterus. Removal may be discussed when a polyp is thought to distort the cavity, when abnormal bleeding is present, before certain fertility treatments, or when the clinical history suggests the finding may be relevant.

Not every tiny polyp requires immediate surgery. The decision should consider symptoms, size, location, age, fertility treatment plan and whether there are stronger competing causes of infertility. A targeted approach helps avoid unnecessary procedures while still addressing findings that may matter.

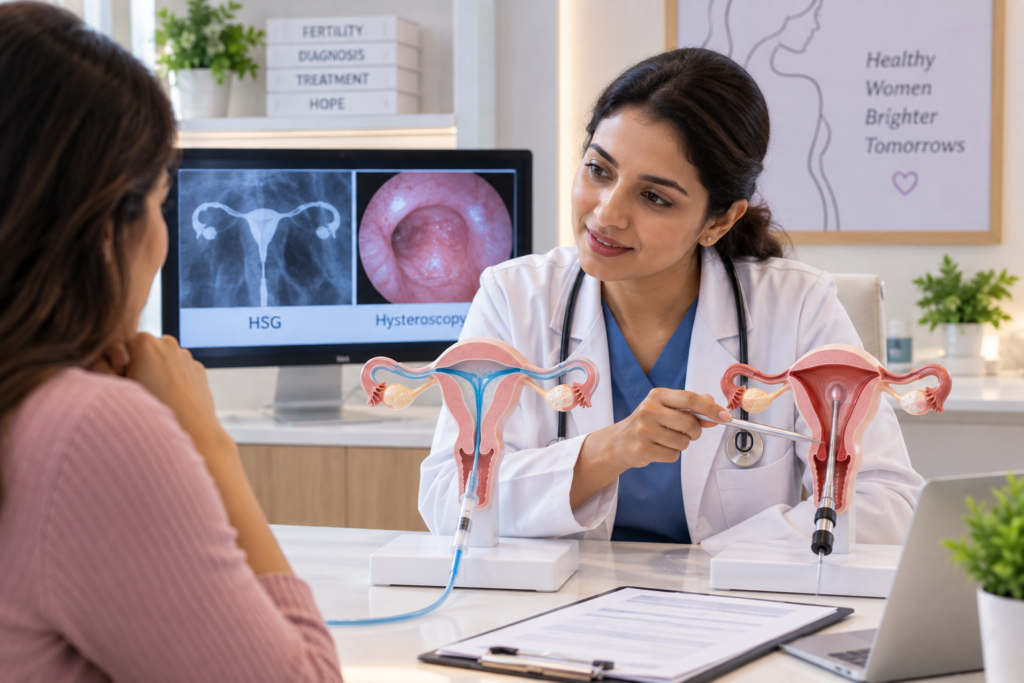
Fertility specialist discussing uterine cavity findings with a patient

Uterine-cavity findings should be interpreted alongside the complete fertility history.

Endometrial Polyps Before IVF or Embryo Transfer

Before IVF or frozen embryo transfer, the fertility team may review the uterine cavity to make sure there is no clinically important lesion that could interfere with implantation. If a polyp is identified, the team considers whether removal is likely to improve the uterine environment enough to justify postponing treatment.

The complete IVF process includes ovarian stimulation, egg retrieval, fertilization, embryo culture and embryo transfer, but success also depends on a suitable uterine environment. For this reason, uterine findings are evaluated in the context of the whole IVF plan rather than as an isolated checklist item.

Polyps, Thin Endometrium and Other Uterine Findings

Endometrial polyps are different from a thin endometrium, fibroids, adhesions and chronic endometritis, although more than one condition can coexist. A thin lining refers to endometrial thickness, while a polyp is a focal tissue overgrowth. Fibroids arise from uterine muscle, and chronic endometritis is an inflammatory condition of the endometrium.

Distinguishing these conditions matters because the treatment is different. The existing Sree Swapna articles on thin endometrium in IVF and chronic endometritis provide useful background for patients undergoing uterine or implantation evaluation.

Can Polyps Return After Removal?

Endometrial polyps can recur in some patients after hysteroscopic removal. Recurrence does not mean that repeated hysteroscopy is automatically needed. Follow-up depends on symptoms, fertility plans, ultrasound findings and whether a new cavity abnormality is suspected.

For a patient preparing for fertility treatment, the fertility specialist may repeat imaging when clinically appropriate rather than following a fixed testing schedule for everyone.

When Should You Speak With a Fertility Specialist?

Consider a fertility review if pregnancy has not occurred within the expected time for your age, if there is recurrent pregnancy loss, repeated implantation difficulty, abnormal uterine bleeding, or a scan showing a possible cavity lesion. The aim of the consultation is to determine whether the polyp is actually relevant and what other fertility factors should be evaluated.

At Sree Swapna Fertility Centre, Dr. Swapna Naik can review the uterine finding in the context of ovarian reserve, fallopian-tube status, semen analysis, previous treatment history and reproductive goals. A complete plan is more useful than assuming every uterine finding requires surgery.

Fertility Guidance From Dr. Swapna Naik

At Sree Swapna Fertility Centre, Dr. Swapna Naik evaluates endometrial polyps in the context of age, ovarian reserve, tubal health, semen factors, previous fertility treatment and reproductive goals. This helps determine whether a polyp is likely to be clinically relevant and whether hysteroscopic treatment is appropriate before natural conception, IUI, IVF or embryo transfer.

Frequently Asked Questions

Can endometrial polyps cause infertility?

They may contribute to infertility in some patients, especially when they alter the uterine cavity, but they are not the only possible cause. A complete fertility evaluation is needed.

Can a uterine polyp prevent implantation?

A polyp may interfere with implantation depending on its size and location, but implantation also depends on embryo and other uterine factors.

Can I get pregnant naturally with an endometrial polyp?

Yes. Many people with small or incidental polyps conceive naturally. The clinical relevance depends on the full fertility picture.

Do polyps cause miscarriage?

Some cavity abnormalities may be associated with pregnancy loss, but a polyp does not prove the cause of a miscarriage. Recurrent loss needs a broader evaluation.

How are endometrial polyps diagnosed?

Transvaginal ultrasound, saline sonography and hysteroscopy may be used depending on the clinical situation.

Can ultrasound detect a uterine polyp?

Ultrasound can often suggest a polyp, although additional cavity imaging may be needed when the diagnosis is uncertain.

Can HSG detect polyps?

HSG may show a filling defect in the cavity, but hysteroscopy or saline sonography can provide more direct cavity assessment.

Is hysteroscopy the best test for polyps?

Hysteroscopy directly visualizes the cavity and can allow treatment, but the best test depends on the clinical question and prior imaging.

How are uterine polyps removed?

Suitable polyps are commonly removed with hysteroscopic polypectomy through the cervix without an abdominal incision.

Is hysteroscopic polyp removal painful?

Discomfort varies with the procedure and anesthesia approach. Patients should discuss pain control and recovery with the treating team.

Does every endometrial polyp need removal?

No. The decision depends on symptoms, size, location, fertility history and planned treatment.

Should a polyp be removed before IVF?

Removal may be considered when the polyp is thought to affect the cavity, but this should be individualized rather than automatic.

Should a polyp be removed before frozen embryo transfer?

The fertility team may recommend removal if the lesion is clinically relevant to the uterine cavity before transfer.

How long after polyp removal can IVF start?

Timing depends on the extent of the procedure, healing and the treatment plan. Follow the schedule recommended by the fertility specialist.

Can endometrial polyps return?

Yes, recurrence can occur. Follow-up is based on symptoms and fertility needs rather than routine repeated procedures for everyone.

Are endometrial polyps cancerous?

Most are benign, but tissue removed during hysteroscopy may be sent for histopathology when clinically indicated.

Can polyps cause irregular bleeding?

Yes. Irregular or heavy bleeding can occur, although some polyps cause no symptoms.

Can polyps be confused with fibroids?

Yes, imaging sometimes needs to distinguish an endometrial polyp from a submucosal fibroid because treatment planning differs.

Can polyps coexist with thin endometrium or endometritis?

Yes. Different uterine and endometrial conditions can coexist, so evaluation should identify the specific abnormality.

When should infertility patients be checked for uterine polyps?

Testing may be considered when symptoms, imaging, repeated implantation difficulty or treatment planning raises concern about the uterine cavity.

Conclusion

Endometrial polyps can be relevant to fertility when they alter the uterine cavity, but the best decision is individualized. Accurate diagnosis, appropriate hysteroscopic treatment when indicated, and assessment of the rest of the fertility picture can help avoid both missed problems and unnecessary procedures.

Medical References

• World Health Organization: infertility guidance

• American Society for Reproductive Medicine: practice guidance

• ESHRE guidelines and good-practice recommendations

Author: Swapna

Why Progesterone Is Used in IVF

Progesterone helps prepare and support the endometrium during the luteal phase. After IVF or ICSI, progesterone is commonly used as luteal-phase support because ovarian stimulation and egg retrieval can alter the body’s normal hormone environment. ESHRE guidance recommends progesterone for luteal support after IVF/ICSI.

When Progesterone Is Started

The exact timing depends on whether the cycle involves fresh transfer, programmed frozen transfer or another protocol. In stimulated IVF, progesterone is usually started according to the clinic’s protocol after egg retrieval. Patients should follow the prescribed time closely because embryo and endometrial development need to remain synchronized.

IVF medications and treatment schedule including progesterone support

Progesterone is commonly used as luteal support in IVF and embryo-transfer protocols.

Different Ways Progesterone Can Be Given

Progesterone may be prescribed vaginally, by injection or through other clinic-selected routes. Each route has practical advantages and side effects. One method is not automatically best for every patient, and doses should not be compared directly across products without medical guidance.

Progesterone in Frozen Embryo Transfer

In a programmed FET cycle, progesterone timing is particularly important because the medication helps create the implantation window. The site’s frozen embryo transfer timeline explains the sequence of lining preparation, progesterone exposure and transfer.

Symptoms While Taking Progesterone

Progesterone can cause bloating, breast tenderness, fatigue, discharge with vaginal preparations, or soreness with injections. These symptoms overlap with early pregnancy symptoms and cannot confirm implantation. The article on beta hCG after embryo transfer explains why pregnancy testing is more informative than symptom-checking.

How Long Is Progesterone Continued?

Duration varies by protocol and clinic. Progesterone is commonly continued through the pregnancy test and, in some cycles, for a period after a positive result. Patients should not stop medication because of spotting, a home pregnancy test or symptoms unless the treating team advises it.

What If a Dose Is Missed?

If a dose is missed or taken late, contact the fertility clinic for instructions. Do not double the next dose unless specifically advised. The best response depends on the route, timing and treatment protocol.

Progesterone Does Not Fix Every Implantation Problem

Progesterone is important luteal support, but it cannot overcome every cause of failed implantation. Embryo factors, uterine conditions, timing and other clinical issues may contribute. The recurrent implantation failure guide provides a broader framework for evaluating repeated failure.

Fertility consultation after embryo transfer

Medication timing after embryo transfer should follow the treating fertility team’s protocol.

Related Fertility Topics to Understand

This topic is closely connected with several other parts of fertility evaluation and treatment. For a fuller picture, read the frozen embryo transfer timeline, then compare it with the beta hCG after embryo transfer. Patients moving toward assisted reproduction may also find the recurrent implantation failure useful, while the thin endometrium in IVF explains another related decision point. If treatment planning is already underway, the IVF process guide can help connect this topic with the next stage of care.

Fertility Guidance From Dr. Swapna Naik

At Sree Swapna Fertility Centre, patients can discuss progesterone after embryo transfer in the context of their complete fertility history rather than treating one test or symptom in isolation. Dr. Swapna Naik evaluates factors such as age, ovarian reserve, semen parameters, uterine and tubal health, previous treatment response and reproductive goals before recommending the next step. This individualized approach is especially important in fertility care because the same finding can have different implications for different patients.

Frequently Asked Questions

Why is progesterone given after embryo transfer?

Several factors can contribute, and the exact cause may differ from one patient to another. Evaluation usually combines medical history, examination and targeted fertility tests rather than relying on one symptom or one laboratory value.

When is progesterone started in IVF?

Timing is individualized and can depend on the menstrual cycle, stimulation response, laboratory results and the treatment protocol. Follow the schedule given by the treating fertility team rather than changing medicines or appointments independently.

How is progesterone taken after IVF?

It can influence IVF planning, but its importance depends on the broader clinical picture. The fertility team may adjust stimulation, embryo-transfer timing, medication support or additional evaluation based on the patient’s diagnosis.

Is vaginal progesterone better than injections?

The answer depends on the individual fertility history and clinical findings. For progesterone after embryo transfer, decisions are best made after reviewing the relevant tests, symptoms, age and reproductive goals with a fertility specialist.

Are progesterone injections painful?

The answer depends on the individual fertility history and clinical findings. For progesterone after embryo transfer, decisions are best made after reviewing the relevant tests, symptoms, age and reproductive goals with a fertility specialist.

Can progesterone cause pregnancy-like symptoms?

Several factors can contribute, and the exact cause may differ from one patient to another. Evaluation usually combines medical history, examination and targeted fertility tests rather than relying on one symptom or one laboratory value.

Can progesterone cause spotting?

Several factors can contribute, and the exact cause may differ from one patient to another. Evaluation usually combines medical history, examination and targeted fertility tests rather than relying on one symptom or one laboratory value.

How long is progesterone taken after embryo transfer?

Timing is individualized and can depend on the menstrual cycle, stimulation response, laboratory results and the treatment protocol. Follow the schedule given by the treating fertility team rather than changing medicines or appointments independently.

Can I stop progesterone after a positive pregnancy test?

Pregnancy and live-birth chances depend on multiple factors, including age, ovarian reserve, sperm factors, embryo quality, uterine health and the underlying diagnosis. No single test, medication or add-on can guarantee success.

What happens if I miss a progesterone dose?

The answer depends on the individual fertility history and clinical findings. For progesterone after embryo transfer, decisions are best made after reviewing the relevant tests, symptoms, age and reproductive goals with a fertility specialist.

Can low progesterone cause implantation failure?

Several factors can contribute, and the exact cause may differ from one patient to another. Evaluation usually combines medical history, examination and targeted fertility tests rather than relying on one symptom or one laboratory value.

Is progesterone used after frozen embryo transfer?

The answer depends on the individual fertility history and clinical findings. For progesterone after embryo transfer, decisions are best made after reviewing the relevant tests, symptoms, age and reproductive goals with a fertility specialist.

Is progesterone used after fresh embryo transfer?

The answer depends on the individual fertility history and clinical findings. For progesterone after embryo transfer, decisions are best made after reviewing the relevant tests, symptoms, age and reproductive goals with a fertility specialist.

Can progesterone delay a period?

The answer depends on the individual fertility history and clinical findings. For progesterone after embryo transfer, decisions are best made after reviewing the relevant tests, symptoms, age and reproductive goals with a fertility specialist.

Can progesterone affect a pregnancy test?

Pregnancy and live-birth chances depend on multiple factors, including age, ovarian reserve, sperm factors, embryo quality, uterine health and the underlying diagnosis. No single test, medication or add-on can guarantee success.

Does progesterone guarantee implantation?

The answer depends on the individual fertility history and clinical findings. For progesterone after embryo transfer, decisions are best made after reviewing the relevant tests, symptoms, age and reproductive goals with a fertility specialist.

What are common progesterone side effects?

Safety depends on the procedure, medical history and treatment protocol. Patients should discuss expected side effects, uncommon complications and warning symptoms with their fertility specialist before starting treatment.

When should progesterone levels be tested?

There is no single number that is ideal for everyone. Reference ranges vary by laboratory, age, treatment stage and clinical context, so results should be interpreted alongside ultrasound findings and other fertility tests.

Can I exercise while using progesterone after IVF?

It can influence IVF planning, but its importance depends on the broader clinical picture. The fertility team may adjust stimulation, embryo-transfer timing, medication support or additional evaluation based on the patient’s diagnosis.

When should I call my fertility clinic while taking progesterone?

Timing is individualized and can depend on the menstrual cycle, stimulation response, laboratory results and the treatment protocol. Follow the schedule given by the treating fertility team rather than changing medicines or appointments independently.

Conclusion

Progesterone is an established part of luteal support in many IVF and embryo-transfer protocols. The most important practical rule is to use the prescribed product at the prescribed time and not change or stop it without instructions from the fertility team.

Medical References

• World Health Organization: Guideline for the prevention, diagnosis and treatment of infertility (2025)

• ESHRE: Ovarian Stimulation for IVF/ICSI guideline update (2025)

• American Society for Reproductive Medicine: Practice Guidance

Medical review recommended before publication. Information is educational and does not replace individualized medical advice.

Author: Swapna

Signs Endometriosis May Be Returning After Surgery: Symptoms & Next Steps

Endometriosis is a chronic condition, and symptoms can recur after surgery. Recurrence may mean return of pain, new lesions seen on imaging, or disease confirmed at another operation. These are not the same thing, which is why recurrent pain should not automatically be labelled recurrent endometriosis.

ESHRE guidance notes that definitions of recurrence vary widely and that other causes of pain, including adenomyosis or pelvic-floor dysfunction, should be considered, particularly when symptoms return soon after surgery. A careful reassessment is therefore more useful than assuming another operation is immediately required.

For a related clinical pathway, review endometriosis and fertility care.

You may also find fertility specialist useful when planning the next step.

What Does Endometriosis Recurrence Mean?

Recurrence can be symptom-based, imaging-based or surgically confirmed. A patient may have recurrent pelvic pain without a visible recurrent lesion, while another may have imaging evidence of an endometrioma with few symptoms.

This difference helps explain why studies report very different recurrence rates. Follow-up duration, disease stage, surgical technique and postoperative treatment all influence what is counted as recurrence.

Symptoms That May Suggest Recurrence

Possible symptoms include return of painful periods, chronic pelvic pain, pain during intercourse, bowel or bladder symptoms that follow the menstrual cycle, and fertility difficulty. Symptoms may resemble those that existed before surgery.

However, signs of endometriosis returning after surgery overlap with other pelvic disorders. Pain location alone cannot confirm the diagnosis.

Related guide: low AMH vs egg quality.

Why Pain Can Return Without Recurrent Endometriosis

Pelvic-floor muscle dysfunction, adenomyosis, adhesions, irritable bowel syndrome, bladder pain syndromes and nerve-related pain can produce similar symptoms. Postoperative scar tissue can also contribute.

ESHRE specifically advises considering other causes when symptoms recur, especially soon after surgery. Repeating surgery without reassessment can expose a patient to risk without treating the real cause.

How Is Suspected Recurrence Evaluated?

The clinician reviews symptoms, previous operative findings and histology, fertility goals and current examination. Ultrasound is often useful for ovarian endometrioma and deep disease in experienced hands, while MRI may be selected for complex cases.

Laparoscopy is no longer treated as an automatic first diagnostic step for every suspected case. Surgery is chosen when it is likely to improve pain, address anatomy or support another defined clinical goal.

For additional context, see IVF failure reasons.

Treatment Options After Symptoms Return

Treatment depends on symptoms and whether pregnancy is currently desired. Hormonal therapies can reduce endometriosis-associated pain but suppress ovulation during use. Surgery may be considered for selected recurrent disease, especially when symptoms, anatomy or organ involvement justify it.

For patients trying to conceive, repeated ovarian surgery must be weighed carefully against ovarian reserve and the possibility of IVF, particularly after endometrioma surgery.

Endometriosis, AMH and Fertility After Surgery

Ovarian endometriosis and ovarian surgery can both be relevant to ovarian reserve. AMH may help with treatment planning but does not provide a direct measurement of egg quality.

If fertility is a priority, the plan should consider age, ovarian reserve, tubal status, semen factors, duration of infertility and whether further surgery is likely to improve or delay the chance of pregnancy.

Endometriosis Treatment Hyderabad: When to Return for Review

Seek review if pelvic pain is progressively returning, periods become markedly more painful, bowel or bladder symptoms are cyclical, an ovarian cyst is found again, or pregnancy is not occurring as expected.

For endometriosis treatment Hyderabad planning, bring the previous operative note and histopathology report when possible. The details of the original disease and surgery often matter more than the label ‘endometriosis surgery’ alone.

Related Questions Patients Commonly Search

People researching this topic often use related phrases such as endometriosis recurrence symptoms, endometriosis after surgery, can endometriosis return after surgery, pelvic pain after endometriosis surgery, recurrent endometriosis, and endometriosis treatment Hyderabad. These phrases describe overlapping questions, but diagnosis and treatment should be based on the individual clinical situation rather than on a search term.

When to Speak With a Fertility Specialist in Hyderabad

A specialist review is useful when symptoms, test results, age, previous treatment or the length of time trying to conceive make the next decision unclear. Bring previous reports and ask what finding is driving the recommendation, what alternatives are reasonable, and how success will be measured.

You can review fertility investigations for more context.

When you are ready for an individual review, IVF treatment.

Practical Checklist Before Your Consultation

Before the appointment, use this checklist to turn online research into specific questions. It helps the clinician focus on findings that can change management and reduces the risk of ordering tests or procedures only because they are available.

  • Are the returning symptoms the same as before surgery?
  • Was the previous disease ovarian, deep, superficial or multi-organ?
  • Is there new imaging evidence of an endometrioma or deep lesion?
  • Could adenomyosis, pelvic-floor dysfunction, adhesions or another pain condition explain symptoms?
  • How do age, AMH and pregnancy goals affect the choice between medical treatment, surgery and IVF?

Bring previous reports, medication lists and procedure records where relevant. Ask for the reasoning behind each recommendation, the alternatives, the expected benefit and the point at which the plan would be reconsidered.

Frequently Asked Questions

1. Can endometriosis come back after surgery?

Yes. Symptoms or lesions can recur after surgery because endometriosis is a chronic condition.

2. What are common recurrence symptoms?

Painful periods, pelvic pain, pain with intercourse, cyclical bowel or bladder symptoms and fertility difficulty may recur.

3. Does recurrent pain always mean endometriosis is back?

No. Adenomyosis, pelvic-floor dysfunction, adhesions and other pain conditions can cause similar symptoms.

4. Can ultrasound detect recurrent endometriosis?

It can identify ovarian endometriomas and some deep disease, especially when performed by an experienced examiner.

5. Is MRI always needed?

No. MRI is selected for specific clinical questions or complex disease.

6. Do I need another laparoscopy if pain returns?

Not automatically. Re-evaluation should establish whether surgery is likely to improve the problem.

7. Can hormonal treatment prevent recurrence?

Postoperative hormonal treatment can reduce recurrence of pain or disease in some patients not trying to conceive; the approach is individualized.

8. Can I take hormonal treatment if I am trying to get pregnant?

Many hormonal treatments suppress ovulation and are not used while actively attempting conception.

9. Can repeated ovarian surgery reduce AMH?

Ovarian surgery can affect ovarian reserve, so repeat surgery should be carefully weighed against fertility goals.

10. Does endometriosis reduce IVF success?

Endometriosis can influence fertility, but IVF remains an effective treatment option for many patients.

11. Can endometriosis cause miscarriage?

Some studies show associations with adverse reproductive outcomes, but miscarriage has many causes and should not automatically be attributed to endometriosis.

12. When should I see a fertility specialist after endometriosis surgery?

Earlier review is reasonable when age, ovarian reserve, tubal disease, male-factor infertility or prolonged attempts to conceive make time important.

Key Takeaway

The best use of information about signs of endometriosis returning after surgery is to improve the next clinical conversation. Use the article to understand the terminology and decision points, then confirm the diagnosis, evidence, risks and treatment options with the fertility team.

Author: Swapna

Recurrent Miscarriage Tests: What Investigations May Be Recommended?

Recurrent miscarriage can create an understandable desire to test everything possible. The challenge is that broad panels often identify abnormalities that do not actually explain the losses or change treatment.

ASRM’s 2026 recurrent pregnancy loss guidance defines RPL as two or more presumed intrauterine pregnancy losses before 22 completed weeks. Evaluation should be evidence-based and adapted to the pregnancy history, genetic findings, age and clinical context. Even after appropriate testing, some couples will not receive one clear cause.

For a related clinical pathway, review recurrent pregnancy loss investigations.

You may also find fertility specialist useful when planning the next step.

Confirming the Pregnancy-Loss History

Before ordering tests, the clinician reviews how many losses occurred, gestational age, whether pregnancies were confirmed by ultrasound or pathology, whether chromosome testing was performed, and whether there have been live births or ectopic pregnancies.

Recurrent pregnancy loss tests should be selected from this history rather than from a standard internet package.

Genetic Evaluation

Chromosomal abnormalities in the embryo are a major cause of miscarriage and are strongly influenced by maternal age. Testing pregnancy tissue after a loss can sometimes clarify whether an aneuploid pregnancy was responsible.

Parental karyotyping may be appropriate in selected couples, particularly when pregnancy genetic results or the pattern of losses raises concern about a balanced chromosomal rearrangement.

Related guide: sperm DNA fragmentation test.

Uterine Assessment

Structural abnormalities such as a uterine septum, some fibroids, polyps or adhesions may be relevant to pregnancy loss. Ultrasound, saline sonography, HSG, 3D ultrasound or hysteroscopy may be used according to the clinical question.

The presence of an abnormality does not automatically prove causation, so treatment should be matched to evidence and the exact lesion.

Hormonal and Medical Factors

Thyroid disease, diabetes and other medical conditions may be assessed based on history. Antiphospholipid syndrome is an important acquired thrombophilia associated with recurrent pregnancy loss and has specific diagnostic criteria.

Testing every patient for broad inherited thrombophilia, immune markers or multiple unvalidated biomarkers is not supported by evidence.

For additional context, see HSG vs hysteroscopy.

Male Factors and Sperm Testing

Male reproductive history and semen evaluation remain relevant to the couple. AUA/ASRM male-infertility guidance allows sperm DNA fragmentation testing to be considered in couples with recurrent pregnancy loss, although it is not recommended as a universal initial male test.

The result should be interpreted in context because changing a laboratory marker does not necessarily prove improvement in live birth.

Treatments That Should Not Be Used Empirically

ASRM 2026 notes that several empiric approaches have not shown benefit for unexplained RPL, including routine low-dose aspirin, heparin or enoxaparin without an indication, glucocorticoids, intralipids and several immune therapies.

This is important because patients with unexplained losses are particularly vulnerable to expensive treatments promoted as the missing solution.

Recurrent Miscarriage Hyderabad: Building the Work-Up

For recurrent miscarriage Hyderabad evaluation, bring ultrasound reports, discharge summaries, pathology or genetic results from previous losses, medication history and any fertility-treatment records.

A useful consultation should separate tests that are clearly indicated from optional tests with weak evidence and should include a plan for the next pregnancy, not only a list of investigations.

Related Questions Patients Commonly Search

People researching this topic often use related phrases such as recurrent pregnancy loss tests, repeated miscarriage tests, recurrent miscarriage causes, RPL investigations, miscarriage fertility tests, and recurrent miscarriage Hyderabad. These phrases describe overlapping questions, but diagnosis and treatment should be based on the individual clinical situation rather than on a search term.

When to Speak With a Fertility Specialist in Hyderabad

A specialist review is useful when symptoms, test results, age, previous treatment or the length of time trying to conceive make the next decision unclear. Bring previous reports and ask what finding is driving the recommendation, what alternatives are reasonable, and how success will be measured.

You can review secondary infertility for more context.

When you are ready for an individual review, book a consultation.

Practical Checklist Before Your Consultation

Before the appointment, use this checklist to turn online research into specific questions. It helps the clinician focus on findings that can change management and reduces the risk of ordering tests or procedures only because they are available.

  • How many losses occurred and at what gestational ages?
  • Was chromosome testing performed on pregnancy tissue?
  • Is uterine imaging complete?
  • Are antiphospholipid syndrome or other evidence-based medical tests indicated?
  • Which proposed tests or treatments are optional and which are supported by current RPL guidance?

Bring previous reports, medication lists and procedure records where relevant. Ask for the reasoning behind each recommendation, the alternatives, the expected benefit and the point at which the plan would be reconsidered.

Frequently Asked Questions

1. How many miscarriages are considered recurrent pregnancy loss?

ASRM 2026 identifies RPL as two or more presumed intrauterine pregnancy losses before 22 completed weeks.

2. Should testing start after two miscarriages?

Evaluation can be considered after two losses, with the exact work-up based on age, pregnancy details and clinical judgment.

3. Are chromosome problems a common cause?

Yes. Embryo chromosomal abnormalities are a major cause of miscarriage and become more common with maternal age.

4. Should miscarriage tissue be genetically tested?

It can be useful in selected cases because the result may clarify the cause and guide the need for parental testing.

5. Do both partners need karyotyping?

Not every couple does. It is considered when the loss pattern or pregnancy genetic results suggest a parental rearrangement.

6. What uterine tests are used?

Ultrasound, 3D ultrasound, saline sonography, HSG or hysteroscopy may be chosen according to the suspected problem.

7. Is thyroid testing part of the work-up?

Thyroid evaluation may be appropriate based on clinical history and standard RPL assessment.

8. Should every patient be tested for inherited thrombophilia?

Broad inherited thrombophilia testing is not routinely supported for all recurrent miscarriage patients.

9. What is antiphospholipid syndrome?

It is an autoimmune clotting disorder associated with pregnancy loss and has specific clinical and laboratory diagnostic criteria.

10. Is sperm DNA fragmentation relevant?

It may be considered in RPL according to male-infertility guidance, but it is not a universal answer to recurrent miscarriage.

11. Should aspirin be taken after recurrent miscarriage?

Do not start aspirin without an indication. ASRM does not support routine empiric aspirin for unexplained RPL.

12. Are immune treatments recommended?

Many immune tests and treatments lack evidence for routine use in unexplained recurrent miscarriage.

13. Can IVF prevent miscarriage?

IVF does not prevent every miscarriage. In selected genetic situations, reproductive options may be discussed, but the benefit depends on the diagnosis.

14. What if all tests are normal?

Unexplained RPL is common. Many patients still have a meaningful chance of future live birth with supportive, evidence-based care.

15. What should I bring to an RPL consultation?

Bring records from each pregnancy loss, ultrasound reports, pathology or genetic results and any prior fertility investigations.

Key Takeaway

The best use of information about recurrent miscarriage tests is to improve the next clinical conversation. Use the article to understand the terminology and decision points, then confirm the diagnosis, evidence, risks and treatment options with the fertility team.

Author: Swapna

HSG vs Hysteroscopy: Which Test Checks Blocked Fallopian Tubes & Uterus?

HSG and hysteroscopy are both used in fertility evaluation, but they answer different questions. Hysterosalpingography, or HSG, uses contrast and X-ray imaging to assess the uterine cavity outline and whether the fallopian tubes appear open. Hysteroscopy passes a small camera through the cervix to directly visualise the inside of the uterus.

Because the tests are different, one does not universally replace the other. HSG vs hysteroscopy should be chosen according to whether the main clinical concern is tubal patency, an intrauterine lesion, or both.

For a related clinical pathway, review fertility investigations.

You may also find hysteroscopy useful when planning the next step.

What Does an HSG Test Check?

HSG is commonly used to assess fallopian-tube patency. Contrast is introduced through the cervix and X-ray images show whether it passes through the tubes and spills into the pelvis.

HSG also outlines the uterine cavity and can suggest abnormalities, but it is less accurate than direct or sonographic cavity assessment for some polyps, submucosal fibroids and adhesions.

What Does Hysteroscopy Check?

Hysteroscopy allows direct visual examination of the uterine cavity. It can identify polyps, submucosal fibroids, adhesions and some uterine structural abnormalities.

It also has a treatment advantage: depending on the finding and setup, the clinician may be able to remove a polyp, divide adhesions or treat another cavity lesion during the procedure.

Related guide: secondary infertility causes.

HSG vs Hysteroscopy for Blocked Fallopian Tubes

If the clinical question is whether the fallopian tubes are open, HSG is generally more useful because hysteroscopy does not show the entire fallopian tubes. Hysteroscopy can see the tubal openings inside the uterus but cannot reliably demonstrate patency through to the pelvis.

A finding of blocked tubes on HSG sometimes requires interpretation or confirmation because temporary tubal spasm can mimic proximal blockage.

Which Test Is Better for the Uterine Cavity?

Hysteroscopy is considered the definitive method for diagnosing and treating intrauterine pathology. ASRM notes that it may be more invasive and costly than HSG or saline sonography when used only for diagnosis.

Ultrasound and saline infusion sonography may therefore be used before hysteroscopy depending on symptoms, history and the suspected lesion.

For additional context, see thin endometrium IVF.

Does Every Infertility Patient Need Both?

No. Test selection depends on age, duration of infertility, previous pregnancy, symptoms, pelvic infection or surgery history, ultrasound findings and the treatment being planned.

A patient going directly to IVF may need different tubal information from a patient planning natural conception or IUI. Similarly, abnormal bleeding or a suspected polyp may make cavity evaluation more important.

HSG Hyderabad and Hysteroscopy: Preparing for Testing

For HSG Hyderabad or hysteroscopy planning, ask when in the menstrual cycle the test is performed, whether pain medicine is recommended, what infection precautions are used, and how the result will change treatment.

Sree Swapna’s Investigation page lists HSG as a radiology test for cavity shape and tubal patency, while the Hysteroscopy page explains direct visualisation of the uterine lining and cavity.

Related Questions Patients Commonly Search

People researching this topic often use related phrases such as HSG test, hysteroscopy test, HSG vs hysteroscopy for infertility, blocked fallopian tubes test, uterine cavity test, and HSG Hyderabad. These phrases describe overlapping questions, but diagnosis and treatment should be based on the individual clinical situation rather than on a search term.

When to Speak With a Fertility Specialist in Hyderabad

A specialist review is useful when symptoms, test results, age, previous treatment or the length of time trying to conceive make the next decision unclear. Bring previous reports and ask what finding is driving the recommendation, what alternatives are reasonable, and how success will be measured.

You can review IVF treatment for more context.

When you are ready for an individual review, book a consultation.

Practical Checklist Before Your Consultation

Before the appointment, use this checklist to turn online research into specific questions. It helps the clinician focus on findings that can change management and reduces the risk of ordering tests or procedures only because they are available.

  • Is the main question tubal patency, uterine-cavity pathology or both?
  • Has ultrasound already shown a polyp, fibroid or suspected adhesion?
  • Is HSG appropriate before IUI or natural-conception planning?
  • Would hysteroscopy diagnose and potentially treat the suspected cavity lesion?
  • How will the result change the fertility plan?

Bring previous reports, medication lists and procedure records where relevant. Ask for the reasoning behind each recommendation, the alternatives, the expected benefit and the point at which the plan would be reconsidered.

Frequently Asked Questions

1. What is HSG?

Hysterosalpingography is an X-ray test using contrast to evaluate the uterine cavity outline and fallopian-tube patency.

2. What is hysteroscopy?

It is direct visual examination of the uterine cavity using a thin telescope passed through the cervix.

3. Which test checks blocked fallopian tubes?

HSG is commonly used to assess whether contrast passes through the fallopian tubes.

4. Can hysteroscopy show blocked tubes?

It can see the tubal openings inside the uterus but does not evaluate the full tubes the way HSG does.

5. Which test is better for polyps?

Hysteroscopy directly visualises the cavity and can diagnose and often treat polyps.

6. Can HSG detect fibroids?

It may suggest submucosal or cavity-distorting abnormalities, but other imaging or hysteroscopy may better define them.

7. Is HSG painful?

Cramping can occur during contrast injection. Experience varies between patients.

8. Does hysteroscopy require anaesthesia?

Office diagnostic hysteroscopy may use little or no anaesthesia, while operative procedures may require more. Protocols vary.

9. Can HSG show false blockage?

Yes. Tubal spasm or technical factors can sometimes mimic proximal blockage.

10. Do I need both HSG and hysteroscopy before IVF?

Not automatically. Testing depends on history, prior imaging and the treatment plan.

11. When is HSG performed?

It is commonly scheduled after menstruation and before ovulation; follow the clinic’s specific cycle instructions.

12. Can hysteroscopy treat a problem at the same time?

Depending on the setup, polyps, adhesions or submucosal lesions may sometimes be treated during hysteroscopy.

Key Takeaway

The best use of information about HSG vs hysteroscopy is to improve the next clinical conversation. Use the article to understand the terminology and decision points, then confirm the diagnosis, evidence, risks and treatment options with the fertility team.

Author: Swapna

Does Low AMH Mean Poor Egg Quality? Ovarian Reserve Explained

AMH, or anti-Mullerian hormone, is widely used in fertility care because it provides information about ovarian reserve. A low result can be alarming, and many patients immediately interpret it as proof of poor egg quality or inability to become pregnant.

That interpretation is too simple. AMH primarily reflects the remaining pool of recruitable follicles and helps predict ovarian response to stimulation. Egg quality, especially the chance of chromosomal normality, is much more strongly related to age. Low AMH vs egg quality is therefore an important distinction when counselling patients.

For a related clinical pathway, review AMH fertility testing.

You may also find IVF treatment useful when planning the next step.

What Does AMH Measure?

AMH is produced by granulosa cells in small growing ovarian follicles. Lower AMH levels are generally associated with lower ovarian reserve and may predict fewer eggs in response to IVF stimulation.

AMH test results should be interpreted with age, antral follicle count, menstrual history and the clinical reason for testing. A single number does not describe every aspect of fertility.

Ovarian Reserve Is Not the Same as Egg Quality

Ovarian reserve describes the quantity of remaining oocytes and expected response to stimulation. Egg quality is a broader concept that includes the egg’s ability to fertilise, support embryo development and contribute to a chromosomally competent embryo.

ASRM guidance emphasizes that female age is the single most important predictor of fecundity and that ovarian reserve testing should supplement, not replace, age-based counselling.

Related guide: IVF failure reasons.

Does Low AMH Mean You Cannot Conceive Naturally?

No. AMH is not a direct natural-fertility test. A person with low AMH may still ovulate and conceive, while someone with a higher AMH can have other fertility problems such as tubal blockage or severe male-factor infertility.

AMH is most useful when it changes treatment planning, such as anticipating response to ovarian stimulation.

Low AMH and IVF

In IVF, low AMH can help predict a lower egg yield. That may influence starting medication dose, counselling about the possibility of cycle cancellation, and discussion of expected embryo numbers.

However, a lower number of eggs does not mean zero chance of success. Age, sperm factors, embryo development and uterine health still matter.

For additional context, see secondary infertility.

Can AMH Be Increased?

AMH naturally varies and declines with age. Some products claim to raise AMH, but increasing the blood number is not the same as increasing the underlying pool of eggs or reversing ovarian ageing.

Patients should be cautious with supplements marketed as treatments for low ovarian reserve. Discuss any supplement because products may interact with treatment or provide unrealistic expectations.

Low Ovarian Reserve: What to Ask Your Specialist

Ask whether the AMH result matches the antral follicle count, what ovarian response is expected, whether time is clinically important because of age, and what alternatives exist if few eggs are obtained.

For low AMH IVF planning, realistic counselling is more valuable than focusing on a target AMH number.

Related Questions Patients Commonly Search

People researching this topic often use related phrases such as does low AMH mean poor egg quality, low AMH fertility, AMH and egg quality, low ovarian reserve, AMH test, and low AMH IVF. These phrases describe overlapping questions, but diagnosis and treatment should be based on the individual clinical situation rather than on a search term.

When to Speak With a Fertility Specialist in Hyderabad

A specialist review is useful when symptoms, test results, age, previous treatment or the length of time trying to conceive make the next decision unclear. Bring previous reports and ask what finding is driving the recommendation, what alternatives are reasonable, and how success will be measured.

You can review fertility specialist for more context.

When you are ready for an individual review, book a consultation.

Practical Checklist Before Your Consultation

Before the appointment, use this checklist to turn online research into specific questions. It helps the clinician focus on findings that can change management and reduces the risk of ordering tests or procedures only because they are available.

  • What is the patient’s age and antral follicle count?
  • Is AMH being used to estimate IVF response or incorrectly treated as a general fertility score?
  • Are there other infertility factors such as tubal disease or male-factor infertility?
  • How many eggs might reasonably be expected from stimulation?
  • Would delaying treatment materially change the reproductive options?

Bring previous reports, medication lists and procedure records where relevant. Ask for the reasoning behind each recommendation, the alternatives, the expected benefit and the point at which the plan would be reconsidered.

Frequently Asked Questions

1. What is AMH?

AMH is anti-Mullerian hormone, a marker produced by small ovarian follicles and used to estimate ovarian reserve.

2. Does low AMH mean poor egg quality?

Not necessarily. AMH mainly reflects egg quantity or expected ovarian response, while age is a stronger predictor of egg chromosomal quality.

3. Can I get pregnant naturally with low AMH?

Yes. Low AMH does not mean natural conception is impossible.

4. Does high AMH guarantee fertility?

No. High AMH does not assess tubal health, sperm factors or every aspect of egg quality.

5. What is ovarian reserve?

It refers to the remaining quantity of oocytes and the ovaries’ expected response to stimulation.

6. Is AMH affected by age?

Yes. AMH generally declines as ovarian reserve decreases with age.

7. Can PCOS cause high AMH?

People with PCOS often have higher AMH because they may have more small antral follicles.

8. Should AMH be tested every month?

Usually not. Small variations occur, and repeated testing should have a clinical reason.

9. Can supplements increase egg reserve?

No supplement has been proven to restore the lost ovarian pool. Be cautious with products promising to reverse ovarian ageing.

10. Does low AMH mean IVF should start immediately?

Not automatically. Timing depends on age, fertility goals, other diagnoses and how long pregnancy has been attempted.

11. Can low AMH cause miscarriage?

AMH itself is not a direct miscarriage diagnosis. Age-related embryo chromosomal factors are more important.

12. What other test is used with AMH?

Antral follicle count on ultrasound is commonly considered alongside AMH and age.

Key Takeaway

The best use of information about low AMH vs egg quality is to improve the next clinical conversation. Use the article to understand the terminology and decision points, then confirm the diagnosis, evidence, risks and treatment options with the fertility team.

Author: Swapna

Thin Endometrium and IVF: Causes, Implantation Impact & Treatment Approach

The endometrium is the inner lining of the uterus where an embryo implants. During IVF or frozen embryo transfer, ultrasound is commonly used to assess endometrial development. When the lining remains thinner than expected, patients often worry that implantation is impossible.

Thin endometrium is a clinical observation, not a complete diagnosis. Endometrial thickness is only one part of receptivity, and pregnancy can occur at a range of measurements. The useful question is why the lining is persistently thin in a particular patient and whether a correctable uterine or hormonal factor is present.

For a related clinical pathway, review IVF treatment.

You may also find hysteroscopy useful when planning the next step.

How Is Endometrial Thickness Measured?

Transvaginal ultrasound measures the endometrium in the midline, usually at its thickest point. Measurements can vary slightly between observers and with uterine position.

Searches for endometrial thickness IVF often focus on one target number. Clinics may use thresholds when deciding whether to proceed with transfer, but the relationship between thickness and outcome is continuous rather than a simple pass-or-fail line.

Possible Causes of a Thin Uterine Lining

A lining may remain thin because of inadequate estrogen exposure, previous uterine surgery or curettage, intrauterine adhesions, chronic endometrial injury or individual variation. Some patients have a thin lining without a clearly identifiable structural cause.

Medication response should be reviewed before assuming the uterus is abnormal. In frozen cycles, the route, dose and duration of estrogen or the timing of ovulation may affect development.

Related guide: recurrent implantation failure.

When Is Uterine Evaluation Needed?

If the lining is persistently thin, particularly after previous uterine procedures or with abnormal bleeding, the clinician may review the uterine cavity. Ultrasound, saline sonography and hysteroscopy answer different questions.

Hysteroscopy directly visualises the uterine cavity and can diagnose and sometimes treat intrauterine adhesions or polyps. It should be used when the history and findings make it clinically relevant, not as an automatic add-on for every thin lining.

Does Thin Endometrium Reduce Implantation?

Studies often show lower average implantation or pregnancy rates at very low endometrial measurements, but no single thickness perfectly predicts whether an embryo will implant. Embryo competence remains a major determinant of outcome.

Thin lining embryo transfer decisions therefore involve embryo availability, cycle history, the persistence of the thin measurement, cause, and whether further intervention is likely to improve the endometrium.

For additional context, see frozen embryo transfer timeline.

Treatment Approaches

Management begins with correcting the identifiable cause. In medicated cycles, estrogen exposure may be adjusted. If adhesions are present, hysteroscopic treatment may be appropriate. Other approaches advertised for thin endometrium have variable or limited evidence.

Patients should be cautious with expensive experimental treatments promoted as guaranteed lining boosters. Ask whether the intervention improves live birth rather than only changing ultrasound thickness.

Thin Endometrium Hyderabad: IVF Planning

For thin endometrium Hyderabad fertility care, bring records from previous cycles showing lining measurements, medication doses, hysteroscopy or surgery reports, and embryo information.

A useful plan should state whether the lining is consistently thin, whether the cavity has been adequately evaluated, what change is being attempted, and what the clinic will do if the target thickness is not reached.

Related Questions Patients Commonly Search

People researching this topic often use related phrases such as thin endometrium treatment, thin uterine lining IVF, endometrial thickness IVF, thin lining embryo transfer, thin endometrium implantation, and thin endometrium Hyderabad. These phrases describe overlapping questions, but diagnosis and treatment should be based on the individual clinical situation rather than on a search term.

When to Speak With a Fertility Specialist in Hyderabad

A specialist review is useful when symptoms, test results, age, previous treatment or the length of time trying to conceive make the next decision unclear. Bring previous reports and ask what finding is driving the recommendation, what alternatives are reasonable, and how success will be measured.

You can review fertility investigations for more context.

When you are ready for an individual review, book an appointment.

Practical Checklist Before Your Consultation

Before the appointment, use this checklist to turn online research into specific questions. It helps the clinician focus on findings that can change management and reduces the risk of ordering tests or procedures only because they are available.

  • Is the lining consistently thin across cycles or only in one cycle?
  • What estrogen route, dose and duration were used?
  • Is there a history of uterine surgery, curettage, infection or abnormal bleeding?
  • Has the uterine cavity been assessed with ultrasound, saline sonography or hysteroscopy when indicated?
  • What evidence supports any proposed add-on treatment?

Bring previous reports, medication lists and procedure records where relevant. Ask for the reasoning behind each recommendation, the alternatives, the expected benefit and the point at which the plan would be reconsidered.

Frequently Asked Questions

1. What is thin endometrium?

It refers to an endometrial lining that remains thinner than expected during a fertility-treatment cycle.

2. What endometrial thickness is needed for IVF?

Clinics use different thresholds, and no single measurement guarantees or rules out pregnancy.

3. Can pregnancy occur with a thin lining?

Yes. Pregnancy is possible, although very thin measurements may be associated with lower average success in some studies.

4. What causes thin endometrium?

Possible causes include inadequate hormonal response, intrauterine adhesions, prior uterine procedures, chronic injury and individual variation.

5. Can previous D&C cause a thin lining?

It can be associated with intrauterine adhesions in some patients, especially when the lining is persistently thin afterward.

6. How is the uterine cavity checked?

Ultrasound, saline sonography and hysteroscopy may be used depending on the clinical question.

7. Does hysteroscopy increase lining thickness?

Hysteroscopy treats specific cavity problems such as adhesions; it is not a general thickness treatment when the cavity is normal.

8. Can estrogen improve a thin lining?

Adjusting estrogen may help in selected medicated cycles, but response varies.

9. Are PRP and G-CSF proven for thin endometrium?

Evidence remains limited for routine use. Ask whether an add-on has been shown to improve live birth.

10. Should embryo transfer be cancelled if the lining is thin?

The decision is individualized based on measurement, pattern, embryo availability, history and clinic protocol.

11. Does a trilaminar pattern matter?

Ultrasound pattern may be considered alongside thickness, but neither measure alone determines implantation.

12. Can thin endometrium cause recurrent implantation failure?

It may be one contributing factor in selected patients, but repeated failure requires a broader embryo and uterine review.

Key Takeaway

The best use of information about thin endometrium IVF is to improve the next clinical conversation. Use the article to understand the terminology and decision points, then confirm the diagnosis, evidence, risks and treatment options with the fertility team.

Scroll to Top

To Book an Appointment

+917670804424 📞 Call Now

Recent Posts