Best Fertility Centre – Dr. Swapna Naik

Category: Blog

Signs Endometriosis May Be Returning After Surgery: Symptoms & Next Steps

Endometriosis is a chronic condition, and symptoms can recur after surgery. Recurrence may mean return of pain, new lesions seen on imaging, or disease confirmed at another operation. These are not the same thing, which is why recurrent pain should not automatically be labelled recurrent endometriosis.

ESHRE guidance notes that definitions of recurrence vary widely and that other causes of pain, including adenomyosis or pelvic-floor dysfunction, should be considered, particularly when symptoms return soon after surgery. A careful reassessment is therefore more useful than assuming another operation is immediately required.

For a related clinical pathway, review endometriosis and fertility care.

You may also find fertility specialist useful when planning the next step.

What Does Endometriosis Recurrence Mean?

Recurrence can be symptom-based, imaging-based or surgically confirmed. A patient may have recurrent pelvic pain without a visible recurrent lesion, while another may have imaging evidence of an endometrioma with few symptoms.

This difference helps explain why studies report very different recurrence rates. Follow-up duration, disease stage, surgical technique and postoperative treatment all influence what is counted as recurrence.

Symptoms That May Suggest Recurrence

Possible symptoms include return of painful periods, chronic pelvic pain, pain during intercourse, bowel or bladder symptoms that follow the menstrual cycle, and fertility difficulty. Symptoms may resemble those that existed before surgery.

However, signs of endometriosis returning after surgery overlap with other pelvic disorders. Pain location alone cannot confirm the diagnosis.

Related guide: low AMH vs egg quality.

Why Pain Can Return Without Recurrent Endometriosis

Pelvic-floor muscle dysfunction, adenomyosis, adhesions, irritable bowel syndrome, bladder pain syndromes and nerve-related pain can produce similar symptoms. Postoperative scar tissue can also contribute.

ESHRE specifically advises considering other causes when symptoms recur, especially soon after surgery. Repeating surgery without reassessment can expose a patient to risk without treating the real cause.

How Is Suspected Recurrence Evaluated?

The clinician reviews symptoms, previous operative findings and histology, fertility goals and current examination. Ultrasound is often useful for ovarian endometrioma and deep disease in experienced hands, while MRI may be selected for complex cases.

Laparoscopy is no longer treated as an automatic first diagnostic step for every suspected case. Surgery is chosen when it is likely to improve pain, address anatomy or support another defined clinical goal.

For additional context, see IVF failure reasons.

Treatment Options After Symptoms Return

Treatment depends on symptoms and whether pregnancy is currently desired. Hormonal therapies can reduce endometriosis-associated pain but suppress ovulation during use. Surgery may be considered for selected recurrent disease, especially when symptoms, anatomy or organ involvement justify it.

For patients trying to conceive, repeated ovarian surgery must be weighed carefully against ovarian reserve and the possibility of IVF, particularly after endometrioma surgery.

Endometriosis, AMH and Fertility After Surgery

Ovarian endometriosis and ovarian surgery can both be relevant to ovarian reserve. AMH may help with treatment planning but does not provide a direct measurement of egg quality.

If fertility is a priority, the plan should consider age, ovarian reserve, tubal status, semen factors, duration of infertility and whether further surgery is likely to improve or delay the chance of pregnancy.

Endometriosis Treatment Hyderabad: When to Return for Review

Seek review if pelvic pain is progressively returning, periods become markedly more painful, bowel or bladder symptoms are cyclical, an ovarian cyst is found again, or pregnancy is not occurring as expected.

For endometriosis treatment Hyderabad planning, bring the previous operative note and histopathology report when possible. The details of the original disease and surgery often matter more than the label ‘endometriosis surgery’ alone.

Related Questions Patients Commonly Search

People researching this topic often use related phrases such as endometriosis recurrence symptoms, endometriosis after surgery, can endometriosis return after surgery, pelvic pain after endometriosis surgery, recurrent endometriosis, and endometriosis treatment Hyderabad. These phrases describe overlapping questions, but diagnosis and treatment should be based on the individual clinical situation rather than on a search term.

When to Speak With a Fertility Specialist in Hyderabad

A specialist review is useful when symptoms, test results, age, previous treatment or the length of time trying to conceive make the next decision unclear. Bring previous reports and ask what finding is driving the recommendation, what alternatives are reasonable, and how success will be measured.

You can review fertility investigations for more context.

When you are ready for an individual review, IVF treatment.

Practical Checklist Before Your Consultation

Before the appointment, use this checklist to turn online research into specific questions. It helps the clinician focus on findings that can change management and reduces the risk of ordering tests or procedures only because they are available.

  • Are the returning symptoms the same as before surgery?
  • Was the previous disease ovarian, deep, superficial or multi-organ?
  • Is there new imaging evidence of an endometrioma or deep lesion?
  • Could adenomyosis, pelvic-floor dysfunction, adhesions or another pain condition explain symptoms?
  • How do age, AMH and pregnancy goals affect the choice between medical treatment, surgery and IVF?

Bring previous reports, medication lists and procedure records where relevant. Ask for the reasoning behind each recommendation, the alternatives, the expected benefit and the point at which the plan would be reconsidered.

Frequently Asked Questions

1. Can endometriosis come back after surgery?

Yes. Symptoms or lesions can recur after surgery because endometriosis is a chronic condition.

2. What are common recurrence symptoms?

Painful periods, pelvic pain, pain with intercourse, cyclical bowel or bladder symptoms and fertility difficulty may recur.

3. Does recurrent pain always mean endometriosis is back?

No. Adenomyosis, pelvic-floor dysfunction, adhesions and other pain conditions can cause similar symptoms.

4. Can ultrasound detect recurrent endometriosis?

It can identify ovarian endometriomas and some deep disease, especially when performed by an experienced examiner.

5. Is MRI always needed?

No. MRI is selected for specific clinical questions or complex disease.

6. Do I need another laparoscopy if pain returns?

Not automatically. Re-evaluation should establish whether surgery is likely to improve the problem.

7. Can hormonal treatment prevent recurrence?

Postoperative hormonal treatment can reduce recurrence of pain or disease in some patients not trying to conceive; the approach is individualized.

8. Can I take hormonal treatment if I am trying to get pregnant?

Many hormonal treatments suppress ovulation and are not used while actively attempting conception.

9. Can repeated ovarian surgery reduce AMH?

Ovarian surgery can affect ovarian reserve, so repeat surgery should be carefully weighed against fertility goals.

10. Does endometriosis reduce IVF success?

Endometriosis can influence fertility, but IVF remains an effective treatment option for many patients.

11. Can endometriosis cause miscarriage?

Some studies show associations with adverse reproductive outcomes, but miscarriage has many causes and should not automatically be attributed to endometriosis.

12. When should I see a fertility specialist after endometriosis surgery?

Earlier review is reasonable when age, ovarian reserve, tubal disease, male-factor infertility or prolonged attempts to conceive make time important.

Key Takeaway

The best use of information about signs of endometriosis returning after surgery is to improve the next clinical conversation. Use the article to understand the terminology and decision points, then confirm the diagnosis, evidence, risks and treatment options with the fertility team.

Category: Blog

Recurrent Miscarriage Tests: What Investigations May Be Recommended?

Recurrent miscarriage can create an understandable desire to test everything possible. The challenge is that broad panels often identify abnormalities that do not actually explain the losses or change treatment.

ASRM’s 2026 recurrent pregnancy loss guidance defines RPL as two or more presumed intrauterine pregnancy losses before 22 completed weeks. Evaluation should be evidence-based and adapted to the pregnancy history, genetic findings, age and clinical context. Even after appropriate testing, some couples will not receive one clear cause.

For a related clinical pathway, review recurrent pregnancy loss investigations.

You may also find fertility specialist useful when planning the next step.

Confirming the Pregnancy-Loss History

Before ordering tests, the clinician reviews how many losses occurred, gestational age, whether pregnancies were confirmed by ultrasound or pathology, whether chromosome testing was performed, and whether there have been live births or ectopic pregnancies.

Recurrent pregnancy loss tests should be selected from this history rather than from a standard internet package.

Genetic Evaluation

Chromosomal abnormalities in the embryo are a major cause of miscarriage and are strongly influenced by maternal age. Testing pregnancy tissue after a loss can sometimes clarify whether an aneuploid pregnancy was responsible.

Parental karyotyping may be appropriate in selected couples, particularly when pregnancy genetic results or the pattern of losses raises concern about a balanced chromosomal rearrangement.

Related guide: sperm DNA fragmentation test.

Uterine Assessment

Structural abnormalities such as a uterine septum, some fibroids, polyps or adhesions may be relevant to pregnancy loss. Ultrasound, saline sonography, HSG, 3D ultrasound or hysteroscopy may be used according to the clinical question.

The presence of an abnormality does not automatically prove causation, so treatment should be matched to evidence and the exact lesion.

Hormonal and Medical Factors

Thyroid disease, diabetes and other medical conditions may be assessed based on history. Antiphospholipid syndrome is an important acquired thrombophilia associated with recurrent pregnancy loss and has specific diagnostic criteria.

Testing every patient for broad inherited thrombophilia, immune markers or multiple unvalidated biomarkers is not supported by evidence.

For additional context, see HSG vs hysteroscopy.

Male Factors and Sperm Testing

Male reproductive history and semen evaluation remain relevant to the couple. AUA/ASRM male-infertility guidance allows sperm DNA fragmentation testing to be considered in couples with recurrent pregnancy loss, although it is not recommended as a universal initial male test.

The result should be interpreted in context because changing a laboratory marker does not necessarily prove improvement in live birth.

Treatments That Should Not Be Used Empirically

ASRM 2026 notes that several empiric approaches have not shown benefit for unexplained RPL, including routine low-dose aspirin, heparin or enoxaparin without an indication, glucocorticoids, intralipids and several immune therapies.

This is important because patients with unexplained losses are particularly vulnerable to expensive treatments promoted as the missing solution.

Recurrent Miscarriage Hyderabad: Building the Work-Up

For recurrent miscarriage Hyderabad evaluation, bring ultrasound reports, discharge summaries, pathology or genetic results from previous losses, medication history and any fertility-treatment records.

A useful consultation should separate tests that are clearly indicated from optional tests with weak evidence and should include a plan for the next pregnancy, not only a list of investigations.

Related Questions Patients Commonly Search

People researching this topic often use related phrases such as recurrent pregnancy loss tests, repeated miscarriage tests, recurrent miscarriage causes, RPL investigations, miscarriage fertility tests, and recurrent miscarriage Hyderabad. These phrases describe overlapping questions, but diagnosis and treatment should be based on the individual clinical situation rather than on a search term.

When to Speak With a Fertility Specialist in Hyderabad

A specialist review is useful when symptoms, test results, age, previous treatment or the length of time trying to conceive make the next decision unclear. Bring previous reports and ask what finding is driving the recommendation, what alternatives are reasonable, and how success will be measured.

You can review secondary infertility for more context.

When you are ready for an individual review, book a consultation.

Practical Checklist Before Your Consultation

Before the appointment, use this checklist to turn online research into specific questions. It helps the clinician focus on findings that can change management and reduces the risk of ordering tests or procedures only because they are available.

  • How many losses occurred and at what gestational ages?
  • Was chromosome testing performed on pregnancy tissue?
  • Is uterine imaging complete?
  • Are antiphospholipid syndrome or other evidence-based medical tests indicated?
  • Which proposed tests or treatments are optional and which are supported by current RPL guidance?

Bring previous reports, medication lists and procedure records where relevant. Ask for the reasoning behind each recommendation, the alternatives, the expected benefit and the point at which the plan would be reconsidered.

Frequently Asked Questions

1. How many miscarriages are considered recurrent pregnancy loss?

ASRM 2026 identifies RPL as two or more presumed intrauterine pregnancy losses before 22 completed weeks.

2. Should testing start after two miscarriages?

Evaluation can be considered after two losses, with the exact work-up based on age, pregnancy details and clinical judgment.

3. Are chromosome problems a common cause?

Yes. Embryo chromosomal abnormalities are a major cause of miscarriage and become more common with maternal age.

4. Should miscarriage tissue be genetically tested?

It can be useful in selected cases because the result may clarify the cause and guide the need for parental testing.

5. Do both partners need karyotyping?

Not every couple does. It is considered when the loss pattern or pregnancy genetic results suggest a parental rearrangement.

6. What uterine tests are used?

Ultrasound, 3D ultrasound, saline sonography, HSG or hysteroscopy may be chosen according to the suspected problem.

7. Is thyroid testing part of the work-up?

Thyroid evaluation may be appropriate based on clinical history and standard RPL assessment.

8. Should every patient be tested for inherited thrombophilia?

Broad inherited thrombophilia testing is not routinely supported for all recurrent miscarriage patients.

9. What is antiphospholipid syndrome?

It is an autoimmune clotting disorder associated with pregnancy loss and has specific clinical and laboratory diagnostic criteria.

10. Is sperm DNA fragmentation relevant?

It may be considered in RPL according to male-infertility guidance, but it is not a universal answer to recurrent miscarriage.

11. Should aspirin be taken after recurrent miscarriage?

Do not start aspirin without an indication. ASRM does not support routine empiric aspirin for unexplained RPL.

12. Are immune treatments recommended?

Many immune tests and treatments lack evidence for routine use in unexplained recurrent miscarriage.

13. Can IVF prevent miscarriage?

IVF does not prevent every miscarriage. In selected genetic situations, reproductive options may be discussed, but the benefit depends on the diagnosis.

14. What if all tests are normal?

Unexplained RPL is common. Many patients still have a meaningful chance of future live birth with supportive, evidence-based care.

15. What should I bring to an RPL consultation?

Bring records from each pregnancy loss, ultrasound reports, pathology or genetic results and any prior fertility investigations.

Key Takeaway

The best use of information about recurrent miscarriage tests is to improve the next clinical conversation. Use the article to understand the terminology and decision points, then confirm the diagnosis, evidence, risks and treatment options with the fertility team.

Category: Blog

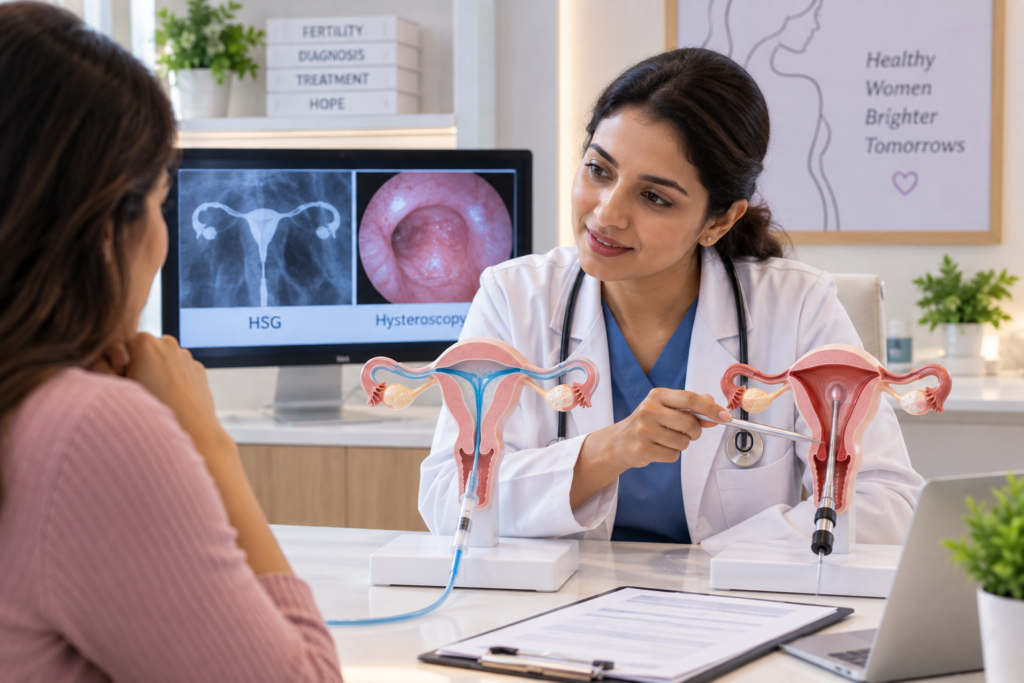
HSG vs Hysteroscopy: Which Test Checks Blocked Fallopian Tubes & Uterus?

HSG and hysteroscopy are both used in fertility evaluation, but they answer different questions. Hysterosalpingography, or HSG, uses contrast and X-ray imaging to assess the uterine cavity outline and whether the fallopian tubes appear open. Hysteroscopy passes a small camera through the cervix to directly visualise the inside of the uterus.

Because the tests are different, one does not universally replace the other. HSG vs hysteroscopy should be chosen according to whether the main clinical concern is tubal patency, an intrauterine lesion, or both.

For a related clinical pathway, review fertility investigations.

You may also find hysteroscopy useful when planning the next step.

What Does an HSG Test Check?

HSG is commonly used to assess fallopian-tube patency. Contrast is introduced through the cervix and X-ray images show whether it passes through the tubes and spills into the pelvis.

HSG also outlines the uterine cavity and can suggest abnormalities, but it is less accurate than direct or sonographic cavity assessment for some polyps, submucosal fibroids and adhesions.

What Does Hysteroscopy Check?

Hysteroscopy allows direct visual examination of the uterine cavity. It can identify polyps, submucosal fibroids, adhesions and some uterine structural abnormalities.

It also has a treatment advantage: depending on the finding and setup, the clinician may be able to remove a polyp, divide adhesions or treat another cavity lesion during the procedure.

Related guide: secondary infertility causes.

HSG vs Hysteroscopy for Blocked Fallopian Tubes

If the clinical question is whether the fallopian tubes are open, HSG is generally more useful because hysteroscopy does not show the entire fallopian tubes. Hysteroscopy can see the tubal openings inside the uterus but cannot reliably demonstrate patency through to the pelvis.

A finding of blocked tubes on HSG sometimes requires interpretation or confirmation because temporary tubal spasm can mimic proximal blockage.

Which Test Is Better for the Uterine Cavity?

Hysteroscopy is considered the definitive method for diagnosing and treating intrauterine pathology. ASRM notes that it may be more invasive and costly than HSG or saline sonography when used only for diagnosis.

Ultrasound and saline infusion sonography may therefore be used before hysteroscopy depending on symptoms, history and the suspected lesion.

For additional context, see thin endometrium IVF.

Does Every Infertility Patient Need Both?

No. Test selection depends on age, duration of infertility, previous pregnancy, symptoms, pelvic infection or surgery history, ultrasound findings and the treatment being planned.

A patient going directly to IVF may need different tubal information from a patient planning natural conception or IUI. Similarly, abnormal bleeding or a suspected polyp may make cavity evaluation more important.

HSG Hyderabad and Hysteroscopy: Preparing for Testing

For HSG Hyderabad or hysteroscopy planning, ask when in the menstrual cycle the test is performed, whether pain medicine is recommended, what infection precautions are used, and how the result will change treatment.

Sree Swapna’s Investigation page lists HSG as a radiology test for cavity shape and tubal patency, while the Hysteroscopy page explains direct visualisation of the uterine lining and cavity.

Related Questions Patients Commonly Search

People researching this topic often use related phrases such as HSG test, hysteroscopy test, HSG vs hysteroscopy for infertility, blocked fallopian tubes test, uterine cavity test, and HSG Hyderabad. These phrases describe overlapping questions, but diagnosis and treatment should be based on the individual clinical situation rather than on a search term.

When to Speak With a Fertility Specialist in Hyderabad

A specialist review is useful when symptoms, test results, age, previous treatment or the length of time trying to conceive make the next decision unclear. Bring previous reports and ask what finding is driving the recommendation, what alternatives are reasonable, and how success will be measured.

You can review IVF treatment for more context.

When you are ready for an individual review, book a consultation.

Practical Checklist Before Your Consultation

Before the appointment, use this checklist to turn online research into specific questions. It helps the clinician focus on findings that can change management and reduces the risk of ordering tests or procedures only because they are available.

  • Is the main question tubal patency, uterine-cavity pathology or both?
  • Has ultrasound already shown a polyp, fibroid or suspected adhesion?
  • Is HSG appropriate before IUI or natural-conception planning?
  • Would hysteroscopy diagnose and potentially treat the suspected cavity lesion?
  • How will the result change the fertility plan?

Bring previous reports, medication lists and procedure records where relevant. Ask for the reasoning behind each recommendation, the alternatives, the expected benefit and the point at which the plan would be reconsidered.

Frequently Asked Questions

1. What is HSG?

Hysterosalpingography is an X-ray test using contrast to evaluate the uterine cavity outline and fallopian-tube patency.

2. What is hysteroscopy?

It is direct visual examination of the uterine cavity using a thin telescope passed through the cervix.

3. Which test checks blocked fallopian tubes?

HSG is commonly used to assess whether contrast passes through the fallopian tubes.

4. Can hysteroscopy show blocked tubes?

It can see the tubal openings inside the uterus but does not evaluate the full tubes the way HSG does.

5. Which test is better for polyps?

Hysteroscopy directly visualises the cavity and can diagnose and often treat polyps.

6. Can HSG detect fibroids?

It may suggest submucosal or cavity-distorting abnormalities, but other imaging or hysteroscopy may better define them.

7. Is HSG painful?

Cramping can occur during contrast injection. Experience varies between patients.

8. Does hysteroscopy require anaesthesia?

Office diagnostic hysteroscopy may use little or no anaesthesia, while operative procedures may require more. Protocols vary.

9. Can HSG show false blockage?

Yes. Tubal spasm or technical factors can sometimes mimic proximal blockage.

10. Do I need both HSG and hysteroscopy before IVF?

Not automatically. Testing depends on history, prior imaging and the treatment plan.

11. When is HSG performed?

It is commonly scheduled after menstruation and before ovulation; follow the clinic’s specific cycle instructions.

12. Can hysteroscopy treat a problem at the same time?

Depending on the setup, polyps, adhesions or submucosal lesions may sometimes be treated during hysteroscopy.

Key Takeaway

The best use of information about HSG vs hysteroscopy is to improve the next clinical conversation. Use the article to understand the terminology and decision points, then confirm the diagnosis, evidence, risks and treatment options with the fertility team.
Category: Blog

Does Low AMH Mean Poor Egg Quality? Ovarian Reserve Explained

AMH, or anti-Mullerian hormone, is widely used in fertility care because it provides information about ovarian reserve. A low result can be alarming, and many patients immediately interpret it as proof of poor egg quality or inability to become pregnant.

That interpretation is too simple. AMH primarily reflects the remaining pool of recruitable follicles and helps predict ovarian response to stimulation. Egg quality, especially the chance of chromosomal normality, is much more strongly related to age. Low AMH vs egg quality is therefore an important distinction when counselling patients.

For a related clinical pathway, review AMH fertility testing.

You may also find IVF treatment useful when planning the next step.

What Does AMH Measure?

AMH is produced by granulosa cells in small growing ovarian follicles. Lower AMH levels are generally associated with lower ovarian reserve and may predict fewer eggs in response to IVF stimulation.

AMH test results should be interpreted with age, antral follicle count, menstrual history and the clinical reason for testing. A single number does not describe every aspect of fertility.

Ovarian Reserve Is Not the Same as Egg Quality

Ovarian reserve describes the quantity of remaining oocytes and expected response to stimulation. Egg quality is a broader concept that includes the egg’s ability to fertilise, support embryo development and contribute to a chromosomally competent embryo.

ASRM guidance emphasizes that female age is the single most important predictor of fecundity and that ovarian reserve testing should supplement, not replace, age-based counselling.

Related guide: IVF failure reasons.

Does Low AMH Mean You Cannot Conceive Naturally?

No. AMH is not a direct natural-fertility test. A person with low AMH may still ovulate and conceive, while someone with a higher AMH can have other fertility problems such as tubal blockage or severe male-factor infertility.

AMH is most useful when it changes treatment planning, such as anticipating response to ovarian stimulation.

Low AMH and IVF

In IVF, low AMH can help predict a lower egg yield. That may influence starting medication dose, counselling about the possibility of cycle cancellation, and discussion of expected embryo numbers.

However, a lower number of eggs does not mean zero chance of success. Age, sperm factors, embryo development and uterine health still matter.

For additional context, see secondary infertility.

Can AMH Be Increased?

AMH naturally varies and declines with age. Some products claim to raise AMH, but increasing the blood number is not the same as increasing the underlying pool of eggs or reversing ovarian ageing.

Patients should be cautious with supplements marketed as treatments for low ovarian reserve. Discuss any supplement because products may interact with treatment or provide unrealistic expectations.

Low Ovarian Reserve: What to Ask Your Specialist

Ask whether the AMH result matches the antral follicle count, what ovarian response is expected, whether time is clinically important because of age, and what alternatives exist if few eggs are obtained.

For low AMH IVF planning, realistic counselling is more valuable than focusing on a target AMH number.

Related Questions Patients Commonly Search

People researching this topic often use related phrases such as does low AMH mean poor egg quality, low AMH fertility, AMH and egg quality, low ovarian reserve, AMH test, and low AMH IVF. These phrases describe overlapping questions, but diagnosis and treatment should be based on the individual clinical situation rather than on a search term.

When to Speak With a Fertility Specialist in Hyderabad

A specialist review is useful when symptoms, test results, age, previous treatment or the length of time trying to conceive make the next decision unclear. Bring previous reports and ask what finding is driving the recommendation, what alternatives are reasonable, and how success will be measured.

You can review fertility specialist for more context.

When you are ready for an individual review, book a consultation.

Practical Checklist Before Your Consultation

Before the appointment, use this checklist to turn online research into specific questions. It helps the clinician focus on findings that can change management and reduces the risk of ordering tests or procedures only because they are available.

  • What is the patient’s age and antral follicle count?
  • Is AMH being used to estimate IVF response or incorrectly treated as a general fertility score?
  • Are there other infertility factors such as tubal disease or male-factor infertility?
  • How many eggs might reasonably be expected from stimulation?
  • Would delaying treatment materially change the reproductive options?

Bring previous reports, medication lists and procedure records where relevant. Ask for the reasoning behind each recommendation, the alternatives, the expected benefit and the point at which the plan would be reconsidered.

Frequently Asked Questions

1. What is AMH?

AMH is anti-Mullerian hormone, a marker produced by small ovarian follicles and used to estimate ovarian reserve.

2. Does low AMH mean poor egg quality?

Not necessarily. AMH mainly reflects egg quantity or expected ovarian response, while age is a stronger predictor of egg chromosomal quality.

3. Can I get pregnant naturally with low AMH?

Yes. Low AMH does not mean natural conception is impossible.

4. Does high AMH guarantee fertility?

No. High AMH does not assess tubal health, sperm factors or every aspect of egg quality.

5. What is ovarian reserve?

It refers to the remaining quantity of oocytes and the ovaries’ expected response to stimulation.

6. Is AMH affected by age?

Yes. AMH generally declines as ovarian reserve decreases with age.

7. Can PCOS cause high AMH?

People with PCOS often have higher AMH because they may have more small antral follicles.

8. Should AMH be tested every month?

Usually not. Small variations occur, and repeated testing should have a clinical reason.

9. Can supplements increase egg reserve?

No supplement has been proven to restore the lost ovarian pool. Be cautious with products promising to reverse ovarian ageing.

10. Does low AMH mean IVF should start immediately?

Not automatically. Timing depends on age, fertility goals, other diagnoses and how long pregnancy has been attempted.

11. Can low AMH cause miscarriage?

AMH itself is not a direct miscarriage diagnosis. Age-related embryo chromosomal factors are more important.

12. What other test is used with AMH?

Antral follicle count on ultrasound is commonly considered alongside AMH and age.

Key Takeaway

The best use of information about low AMH vs egg quality is to improve the next clinical conversation. Use the article to understand the terminology and decision points, then confirm the diagnosis, evidence, risks and treatment options with the fertility team.

Category: Blog

Thin Endometrium and IVF: Causes, Implantation Impact & Treatment Approach

The endometrium is the inner lining of the uterus where an embryo implants. During IVF or frozen embryo transfer, ultrasound is commonly used to assess endometrial development. When the lining remains thinner than expected, patients often worry that implantation is impossible.

Thin endometrium is a clinical observation, not a complete diagnosis. Endometrial thickness is only one part of receptivity, and pregnancy can occur at a range of measurements. The useful question is why the lining is persistently thin in a particular patient and whether a correctable uterine or hormonal factor is present.

For a related clinical pathway, review IVF treatment.

You may also find hysteroscopy useful when planning the next step.

How Is Endometrial Thickness Measured?

Transvaginal ultrasound measures the endometrium in the midline, usually at its thickest point. Measurements can vary slightly between observers and with uterine position.

Searches for endometrial thickness IVF often focus on one target number. Clinics may use thresholds when deciding whether to proceed with transfer, but the relationship between thickness and outcome is continuous rather than a simple pass-or-fail line.

Possible Causes of a Thin Uterine Lining

A lining may remain thin because of inadequate estrogen exposure, previous uterine surgery or curettage, intrauterine adhesions, chronic endometrial injury or individual variation. Some patients have a thin lining without a clearly identifiable structural cause.

Medication response should be reviewed before assuming the uterus is abnormal. In frozen cycles, the route, dose and duration of estrogen or the timing of ovulation may affect development.

Related guide: recurrent implantation failure.

When Is Uterine Evaluation Needed?

If the lining is persistently thin, particularly after previous uterine procedures or with abnormal bleeding, the clinician may review the uterine cavity. Ultrasound, saline sonography and hysteroscopy answer different questions.

Hysteroscopy directly visualises the uterine cavity and can diagnose and sometimes treat intrauterine adhesions or polyps. It should be used when the history and findings make it clinically relevant, not as an automatic add-on for every thin lining.

Does Thin Endometrium Reduce Implantation?

Studies often show lower average implantation or pregnancy rates at very low endometrial measurements, but no single thickness perfectly predicts whether an embryo will implant. Embryo competence remains a major determinant of outcome.

Thin lining embryo transfer decisions therefore involve embryo availability, cycle history, the persistence of the thin measurement, cause, and whether further intervention is likely to improve the endometrium.

For additional context, see frozen embryo transfer timeline.

Treatment Approaches

Management begins with correcting the identifiable cause. In medicated cycles, estrogen exposure may be adjusted. If adhesions are present, hysteroscopic treatment may be appropriate. Other approaches advertised for thin endometrium have variable or limited evidence.

Patients should be cautious with expensive experimental treatments promoted as guaranteed lining boosters. Ask whether the intervention improves live birth rather than only changing ultrasound thickness.

Thin Endometrium Hyderabad: IVF Planning

For thin endometrium Hyderabad fertility care, bring records from previous cycles showing lining measurements, medication doses, hysteroscopy or surgery reports, and embryo information.

A useful plan should state whether the lining is consistently thin, whether the cavity has been adequately evaluated, what change is being attempted, and what the clinic will do if the target thickness is not reached.

Related Questions Patients Commonly Search

People researching this topic often use related phrases such as thin endometrium treatment, thin uterine lining IVF, endometrial thickness IVF, thin lining embryo transfer, thin endometrium implantation, and thin endometrium Hyderabad. These phrases describe overlapping questions, but diagnosis and treatment should be based on the individual clinical situation rather than on a search term.

When to Speak With a Fertility Specialist in Hyderabad

A specialist review is useful when symptoms, test results, age, previous treatment or the length of time trying to conceive make the next decision unclear. Bring previous reports and ask what finding is driving the recommendation, what alternatives are reasonable, and how success will be measured.

You can review fertility investigations for more context.

When you are ready for an individual review, book an appointment.

Practical Checklist Before Your Consultation

Before the appointment, use this checklist to turn online research into specific questions. It helps the clinician focus on findings that can change management and reduces the risk of ordering tests or procedures only because they are available.

  • Is the lining consistently thin across cycles or only in one cycle?
  • What estrogen route, dose and duration were used?
  • Is there a history of uterine surgery, curettage, infection or abnormal bleeding?
  • Has the uterine cavity been assessed with ultrasound, saline sonography or hysteroscopy when indicated?
  • What evidence supports any proposed add-on treatment?

Bring previous reports, medication lists and procedure records where relevant. Ask for the reasoning behind each recommendation, the alternatives, the expected benefit and the point at which the plan would be reconsidered.

Frequently Asked Questions

1. What is thin endometrium?

It refers to an endometrial lining that remains thinner than expected during a fertility-treatment cycle.

2. What endometrial thickness is needed for IVF?

Clinics use different thresholds, and no single measurement guarantees or rules out pregnancy.

3. Can pregnancy occur with a thin lining?

Yes. Pregnancy is possible, although very thin measurements may be associated with lower average success in some studies.

4. What causes thin endometrium?

Possible causes include inadequate hormonal response, intrauterine adhesions, prior uterine procedures, chronic injury and individual variation.

5. Can previous D&C cause a thin lining?

It can be associated with intrauterine adhesions in some patients, especially when the lining is persistently thin afterward.

6. How is the uterine cavity checked?

Ultrasound, saline sonography and hysteroscopy may be used depending on the clinical question.

7. Does hysteroscopy increase lining thickness?

Hysteroscopy treats specific cavity problems such as adhesions; it is not a general thickness treatment when the cavity is normal.

8. Can estrogen improve a thin lining?

Adjusting estrogen may help in selected medicated cycles, but response varies.

9. Are PRP and G-CSF proven for thin endometrium?

Evidence remains limited for routine use. Ask whether an add-on has been shown to improve live birth.

10. Should embryo transfer be cancelled if the lining is thin?

The decision is individualized based on measurement, pattern, embryo availability, history and clinic protocol.

11. Does a trilaminar pattern matter?

Ultrasound pattern may be considered alongside thickness, but neither measure alone determines implantation.

12. Can thin endometrium cause recurrent implantation failure?

It may be one contributing factor in selected patients, but repeated failure requires a broader embryo and uterine review.

Key Takeaway

The best use of information about thin endometrium IVF is to improve the next clinical conversation. Use the article to understand the terminology and decision points, then confirm the diagnosis, evidence, risks and treatment options with the fertility team.

Category: Blog

Beta hCG After Embryo Transfer: When to Test & What Results Mean

After embryo transfer, many patients focus on one number: beta hCG. Human chorionic gonadotropin is produced after implantation begins, and a serum beta hCG test can detect pregnancy before ultrasound can show a gestational sac.

The challenge is that one hCG value has limited meaning by itself. The day of testing, embryo stage, laboratory assay and change over time all affect interpretation. A result should therefore be read against the clinic’s timing and followed according to medical advice rather than compared with an isolated number from another patient’s IVF cycle.

For a related clinical pathway, review IVF treatment.

You may also find frozen embryo transfer timeline useful when planning the next step.

What Is Beta hCG?

Beta hCG is the measurable component of human chorionic gonadotropin commonly used to detect and monitor early pregnancy. After implantation, hCG enters the blood and later becomes detectable in urine.

Searches for beta hCG after IVF and hCG levels after embryo transfer often lead to charts with wide ranges. Early values overlap greatly between normal and abnormal pregnancies, so a single value cannot diagnose pregnancy viability.

When to Test After Embryo Transfer

Testing too early can produce a negative result before hCG rises enough to detect. It can also be confusing if an hCG-containing trigger injection was used earlier in treatment.

ASRM’s 2026 RIF review notes routine hCG testing around 9-11 days after blastocyst and cleavage-stage transfers, respectively, although laboratories and clinic protocols vary. Follow the exact test date provided by your fertility team.

Related guide: recurrent implantation failure.

What Does a Positive Beta hCG Mean?

A positive test means hCG has been detected and implantation has occurred to some degree. It does not yet confirm where the pregnancy is located, whether cardiac activity will develop, or whether the pregnancy will continue.

This is why clinics often schedule another hCG test and then ultrasound at the appropriate gestational stage rather than declaring the outcome from the first number.

Why Are Serial hCG Tests Used?

In early pregnancy, clinicians may compare hCG values over time. The expected pattern is not a fixed ‘doubling every 48 hours’ rule for every pregnancy. The rate of rise depends on the starting concentration and the interval between tests.

Serial values can help identify a pattern that warrants closer review, but ultrasound eventually becomes more informative for pregnancy location and development.

For additional context, see fertility specialist.

What If hCG Is Low or Rises Slowly?

A low initial value may still progress normally, while a high value does not guarantee a healthy pregnancy. A slower-than-expected rise can occur with an early intrauterine pregnancy, miscarriage or ectopic pregnancy, so medical follow-up is important.

Do not stop progesterone or other support medication unless the clinic instructs you to do so.

When Does Ultrasound Become Important?

Once the pregnancy is far enough along, transvaginal ultrasound is used to identify the gestational sac and later fetal structures. The timing depends on gestational age, hCG pattern and symptoms.

Urgent assessment is needed for severe pain, heavy bleeding, dizziness, fainting or other symptoms that could indicate an ectopic pregnancy or significant bleeding.

Pregnancy Test After Embryo Transfer: Practical Advice

Use the clinic’s laboratory and timing when possible. Avoid repeated early home tests that may increase anxiety without changing care. Record the transfer date, embryo stage, medications and official beta hCG results.

After the first positive result, ask when the next blood test is needed, when ultrasound is planned and which symptoms should trigger urgent contact.

Related Questions Patients Commonly Search

People researching this topic often use related phrases such as beta hCG after IVF, pregnancy test after embryo transfer, hCG levels after embryo transfer, when to test after embryo transfer, beta hCG IVF, and positive pregnancy test after IVF. These phrases describe overlapping questions, but diagnosis and treatment should be based on the individual clinical situation rather than on a search term.

When to Speak With a Fertility Specialist in Hyderabad

A specialist review is useful when symptoms, test results, age, previous treatment or the length of time trying to conceive make the next decision unclear. Bring previous reports and ask what finding is driving the recommendation, what alternatives are reasonable, and how success will be measured.

You can review book a fertility consultation for more context.

When you are ready for an individual review, IVF process.

Practical Checklist Before Your Consultation

Before the appointment, use this checklist to turn online research into specific questions. It helps the clinician focus on findings that can change management and reduces the risk of ordering tests or procedures only because they are available.

  • What day was the embryo transferred and what developmental stage was it?
  • Was an hCG-containing trigger used earlier in treatment?
  • What is the clinic’s official blood-test date?
  • When should a repeat beta hCG be performed if the first result is positive?
  • Which symptoms require urgent assessment rather than waiting for the next blood test?

Bring previous reports, medication lists and procedure records where relevant. Ask for the reasoning behind each recommendation, the alternatives, the expected benefit and the point at which the plan would be reconsidered.

Frequently Asked Questions

1. What is beta hCG?

It is a blood measurement of human chorionic gonadotropin used to detect and follow early pregnancy.

2. When should beta hCG be tested after embryo transfer?

Follow your clinic’s date. Timing depends on embryo stage and treatment protocol.

3. Can I test at home before the scheduled blood test?

You can, but early home testing may be falsely negative or confusing after an hCG trigger.

4. What is a good first beta hCG number?

There is no single value that guarantees a healthy pregnancy. Timing and the trend over time matter.

5. Should hCG double every 48 hours?

Not every viable pregnancy follows a strict doubling rule. Clinicians interpret the rate of change based on the starting value and interval.

6. What if my first hCG is low?

A low result needs follow-up. Some low values progress normally while others indicate a nonviable or ectopic pregnancy.

7. What if hCG rises slowly?

A slow rise warrants medical follow-up and may require repeat testing and ultrasound.

8. Does high hCG mean twins?

Not reliably. hCG ranges overlap substantially between singleton and multiple pregnancies.

9. Can progesterone affect the hCG result?

Progesterone does not create hCG. An hCG-containing trigger injection, however, can affect very early testing.

10. When can ultrasound confirm the pregnancy?

Ultrasound is scheduled according to gestational age and the clinical situation rather than one universal hCG number.

11. Can hCG rise after a miscarriage?

hCG can remain detectable for a period after a pregnancy stops developing and generally falls over time.

12. When should I seek urgent care?

Seek urgent assessment for severe or one-sided pain, heavy bleeding, fainting, significant dizziness or other concerning symptoms.

Key Takeaway

The best use of information about beta hCG after embryo transfer is to improve the next clinical conversation. Use the article to understand the terminology and decision points, then confirm the diagnosis, evidence, risks and treatment options with the fertility team.
Category: Blog

Frozen Embryo Transfer Timeline: Step-by-Step FET Cycle Guide

A frozen embryo transfer, or FET, uses an embryo that was previously cryopreserved and later warmed for transfer to the uterus. The exact frozen embryo transfer timeline varies because cycles can be prepared using natural ovulation, modified natural protocols or medication.

Regardless of protocol, the objective is the same: prepare the endometrium and coordinate embryo transfer with the correct biological window. The timing of progesterone is especially important in programmed cycles because embryo stage and endometrial exposure must be synchronized.

For a related clinical pathway, review IVF treatment.

You may also find fertility specialist useful when planning the next step.

Before the FET Cycle Starts

The team reviews embryo information, menstrual history, uterine evaluation and the reason for the frozen transfer. If there are symptoms or previous findings suggesting a cavity problem, additional assessment may be advised.

Baseline ultrasound or blood tests may be used depending on protocol. The clinic also confirms medication instructions and the expected transfer strategy.

Natural FET Cycle

In a natural FET cycle, the team monitors development of a dominant follicle and identifies spontaneous ovulation or coordinates it with a trigger in a modified natural cycle. Transfer is scheduled according to the timing of ovulation and embryo stage.

Natural-cycle FET may suit patients with predictable ovulation, but monitoring and timing remain important.

Related guide: day 3 vs day 5 embryo transfer.

Medicated FET Timeline

In a medicated or programmed cycle, estrogen is commonly used to prepare the endometrium, followed by progesterone. Ultrasound may assess lining development before progesterone is started.

The embryo transfer day is then matched to the number of days of progesterone exposure and the developmental stage of the frozen embryo. Patients should follow the clinic’s timing exactly rather than changing doses or times independently.

Embryo Warming and Transfer Day

On transfer day, the laboratory warms the selected embryo according to its vitrification protocol. Modern vitrification has improved embryo survival, but no laboratory can guarantee that every embryo will survive warming.

If the embryo is suitable, it is loaded into a transfer catheter and placed into the uterus under the clinic’s procedure protocol. Transfer is generally brief and does not usually require anaesthesia.

For additional context, see beta hCG after embryo transfer.

After Frozen Embryo Transfer

Continue prescribed medicines exactly as advised. Routine bed rest has not been shown to create implantation, and most patients can follow the activity guidance given by their clinic.

Symptoms such as mild cramping, bloating or breast tenderness can be caused by progesterone or normal cycle changes and cannot reliably predict whether implantation has occurred.

When Is the Pregnancy Test?

Clinics usually schedule serum beta hCG after enough time has passed for an implanted embryo to produce detectable hormone. Testing too early can create false reassurance or unnecessary alarm.

The exact date depends on embryo stage and clinic protocol. In ASRM’s RIF review, hCG testing is described as routinely performed roughly 9-11 days after blastocyst or cleavage-stage embryo transfer, respectively, but patients should follow the date given by their own clinic.

FET Step by Step: What to Confirm Before You Start

Ask whether your cycle is natural or medicated, what the monitoring schedule is, when progesterone begins, which embryo will be warmed, whether a backup plan exists if warming is unsuccessful, and the exact pregnancy-test date.

A clear FET step by step plan reduces medication errors and makes the cycle easier to follow.

Related Questions Patients Commonly Search

People researching this topic often use related phrases such as FET timeline, frozen embryo transfer process, frozen embryo transfer cycle, FET step by step, medicated FET timeline, and natural FET cycle. These phrases describe overlapping questions, but diagnosis and treatment should be based on the individual clinical situation rather than on a search term.

When to Speak With a Fertility Specialist in Hyderabad

A specialist review is useful when symptoms, test results, age, previous treatment or the length of time trying to conceive make the next decision unclear. Bring previous reports and ask what finding is driving the recommendation, what alternatives are reasonable, and how success will be measured.

You can review thin endometrium IVF for more context.

When you are ready for an individual review, book a fertility consultation.

Practical Checklist Before Your Consultation

Before the appointment, use this checklist to turn online research into specific questions. It helps the clinician focus on findings that can change management and reduces the risk of ordering tests or procedures only because they are available.

  • Is the FET natural, modified-natural or programmed?
  • What monitoring is required before transfer?
  • When exactly should progesterone start, and what happens if a dose is missed?
  • Which embryo is planned for warming and is there a backup embryo?
  • On what date should beta hCG be checked?

Bring previous reports, medication lists and procedure records where relevant. Ask for the reasoning behind each recommendation, the alternatives, the expected benefit and the point at which the plan would be reconsidered.

Frequently Asked Questions

1. What is a frozen embryo transfer?

It is transfer of an embryo that was previously cryopreserved and later warmed.

2. How long does an FET cycle take?

It varies by natural or medicated protocol and by the patient’s menstrual cycle.

3. What is a natural FET?

It times transfer around the patient’s own ovulation.

4. What is a medicated FET?

It uses medication, commonly estrogen and progesterone, to prepare and time the endometrium.

5. Why is progesterone timing important?

The duration of progesterone exposure needs to be synchronized with embryo developmental stage.

6. Can every frozen embryo survive warming?

No. Modern vitrification gives good survival, but survival cannot be guaranteed for every embryo.

7. Is FET painful?

Embryo transfer is usually brief and often causes little or mild discomfort.

8. Do I need bed rest after FET?

Routine prolonged bed rest is generally not required; follow your clinic’s individualized advice.

9. Can symptoms tell whether FET worked?

No. Progesterone and normal cycle changes can mimic early-pregnancy symptoms.

10. When is beta hCG checked?

The clinic schedules testing after enough time has passed for a meaningful result; exact timing depends on embryo stage and protocol.

11. Can I take a home pregnancy test early?

Early home testing can be misleading, especially if hCG trigger medicine was used or the test is done before sufficient time has passed.

12. What happens if the first FET fails?

The team reviews embryo, uterine, hormonal and transfer factors and decides whether further evaluation or another transfer is appropriate.

Key Takeaway

The best use of information about frozen embryo transfer timeline is to improve the next clinical conversation. Use the article to understand the terminology and decision points, then confirm the diagnosis, evidence, risks and treatment options with the fertility team.

Category: Blog

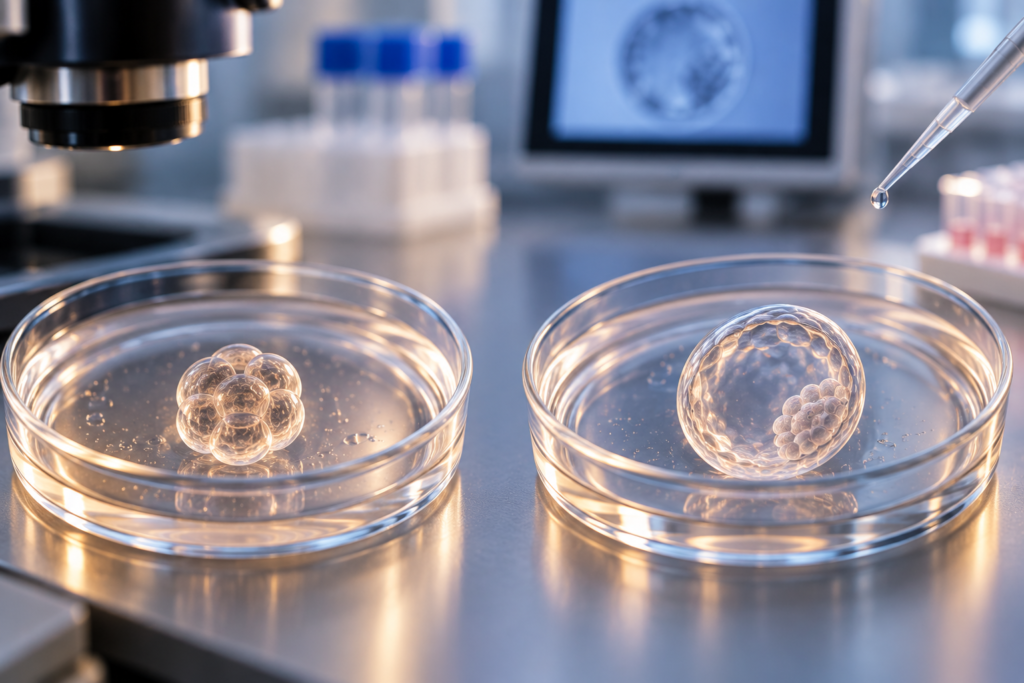
Day 3 vs Day 5 Embryo Transfer: Which Is Better for IVF?

day 3 vs day 5 embryo transfer

During IVF, embryos can be transferred at different stages of development. A day 3 embryo is usually at the cleavage stage, while a day 5 embryo has ideally progressed to the blastocyst stage. The question ‘day 3 vs day 5 embryo transfer’ sounds simple, but the best timing depends on embryo number, development, laboratory experience and the individual patient’s prognosis.

Blastocyst culture provides additional time to observe embryo development and may improve selection in good-prognosis patients. At the same time, extending culture can result in some patients having no embryo available for transfer. The decision should therefore be individualized rather than presented as day 5 always being better.

For a related clinical pathway, review IVF treatment.

You may also find IVF process useful when planning the next step.

What Happens on Day 3?

By day 3 after fertilisation, a normally developing embryo is typically in the cleavage stage and contains multiple cells. Embryologists assess cell number, symmetry, fragmentation and other features.

A day 3 embryo transfer may be considered when there are only a small number of embryos, when the laboratory or clinical team believes extended culture may not add useful selection, or for other individualized reasons.

What Happens on Day 5?

By day 5, an embryo that continues to develop may become a blastocyst with an inner cell mass and trophectoderm. Blastocyst transfer is more physiologically aligned with the stage at which the embryo normally reaches the uterus.

Day 5 embryo transfer can allow stronger selection among embryos that have continued to develop, which is one reason blastocyst transfer is widely used.

Related guide: IVF failure reasons.

Potential Advantages of Blastocyst Transfer

ASRM’s committee opinion notes that in good-prognosis patients, blastocyst transfer can be associated with higher live-birth rates when equal numbers of embryos are transferred. It also supports single-embryo transfer strategies because blastocysts may have higher implantation potential.

Another advantage is that embryos which stop developing before blastocyst stage are not selected for transfer. However, laboratory culture does not create embryo quality; it reveals developmental potential.

Potential Limitations of Waiting Until Day 5

Extended culture increases the chance that a patient with only a few embryos may have no embryo to transfer. Older studies found higher cancellation of transfer in unselected patients randomized to blastocyst culture.

The relevance of this risk depends on embryo number, prognosis, laboratory performance and cryopreservation strategy. A day 3 transfer is not automatically a ‘lower-quality’ choice.

For additional context, see frozen embryo transfer timeline.

Does Day 5 Always Have a Higher Success Rate?

Success-rate comparisons can be misleading if they ignore patient selection. Patients who reach blastocyst transfer often already have more embryos or a better prognosis. Cumulative outcome from all fresh and frozen embryos is also different from pregnancy per single transfer.

Day 3 vs blastocyst transfer should therefore be discussed using the patient’s embryo cohort and not only a clinic-wide percentage.

How Does the Clinic Decide?

The team may consider age, number of normally fertilised embryos, day 2-3 development, previous embryo history, whether PGT is planned and the laboratory’s blastocyst culture performance.

Sree Swapna’s IVF page describes embryo development from day 3 cleavage stage to day 5 blastocyst and notes that embryo quality and other factors guide the transfer decision. A personalised discussion is more useful than choosing a day before the embryos have developed.

Related Questions Patients Commonly Search

People researching this topic often use related phrases such as day 3 embryo transfer, day 5 embryo transfer, blastocyst transfer, cleavage stage embryo transfer, day 3 vs blastocyst transfer, and embryo transfer timing. These phrases describe overlapping questions, but diagnosis and treatment should be based on the individual clinical situation rather than on a search term.

When to Speak With a Fertility Specialist in Hyderabad

A specialist review is useful when symptoms, test results, age, previous treatment or the length of time trying to conceive make the next decision unclear. Bring previous reports and ask what finding is driving the recommendation, what alternatives are reasonable, and how success will be measured.

You can review fertility specialist for more context.

When you are ready for an individual review, book an appointment.

Practical Checklist Before Your Consultation

Before the appointment, use this checklist to turn online research into specific questions. It helps the clinician focus on findings that can change management and reduces the risk of ordering tests or procedures only because they are available.

  • How many normally fertilised embryos are available?
  • How are the embryos developing on day 2-3?
  • What is the laboratory’s experience with extended blastocyst culture?
  • Would waiting until day 5 create a meaningful risk of having no embryo to transfer?
  • Is single-embryo transfer appropriate based on prognosis?

Bring previous reports, medication lists and procedure records where relevant. Ask for the reasoning behind each recommendation, the alternatives, the expected benefit and the point at which the plan would be reconsidered.

Frequently Asked Questions

1. What is a day 3 embryo?

It is usually a cleavage-stage embryo that has undergone several cell divisions after fertilisation.

2. What is a day 5 embryo?

A normally developing day 5 embryo may reach the blastocyst stage.

3. Is day 5 embryo transfer always better?

No. It may be advantageous in good-prognosis patients, but the best stage depends on embryo number, development and clinical context.

4. Why would a clinic choose day 3 transfer?

It may be chosen when embryo numbers are limited or when extended culture is not expected to improve selection.

5. Can embryos stop growing between day 3 and day 5?

Yes. Not all cleavage-stage embryos develop into blastocysts.

6. Does waiting to day 5 damage embryos?

Modern culture systems are designed to support blastocyst development, but laboratory quality and embryo biology both matter.

7. Is pregnancy rate higher with blastocyst transfer?

Often higher per transfer in selected good-prognosis groups, but cumulative live birth and patient selection should also be considered.

8. Can a day 3 embryo become a healthy baby?

Yes. Day 3 embryos can result in healthy pregnancies and live births.

9. Is embryo grading the same on day 3 and day 5?

No. Cleavage-stage and blastocyst embryos are assessed using different developmental features.

10. Is PGT done on day 3 embryos?

Modern PGT commonly involves blastocyst-stage biopsy, though laboratory protocols vary.

11. Can a blastocyst be frozen?

Yes. Blastocysts are commonly vitrified for later frozen embryo transfer.

12. How many embryos should be transferred?

Current practice often favors single-embryo transfer in appropriate patients to reduce multiple pregnancy risk; the exact recommendation depends on age and prognosis.

Key Takeaway

The best use of information about day 3 vs day 5 embryo transfer is to improve the next clinical conversation. Use the article to understand the terminology and decision points, then confirm the diagnosis, evidence, risks and treatment options with the fertility team.

Category: Blog

Why Does IVF Fail? Common Reasons After an Unsuccessful IVF Cycle

An unsuccessful IVF cycle can feel as if the entire treatment failed for one hidden reason. In reality, IVF is a sequence of biological steps: ovarian response, egg retrieval, fertilisation, embryo development, implantation and early pregnancy. A problem can occur at any stage, and sometimes no single cause can be identified.

Understanding IVF failure reasons is most useful when the discussion is tied to the actual cycle data. The number of follicles, mature eggs, fertilisation pattern, embryo development, transfer details and pregnancy testing can show where the treatment pathway narrowed and what may be reasonable to change next.

For a related clinical pathway, review IVF treatment in Hyderabad.

You may also find fertility investigations useful when planning the next step.

IVF Failure Can Mean Different Things

Some cycles are cancelled before egg retrieval because ovarian response is poor or unsafe. Some reach retrieval but produce few or no mature eggs. Others have fertilisation failure, poor embryo development, no embryo suitable for transfer, a negative pregnancy test after transfer, or a pregnancy that later miscarries.

Searches for why IVF fails and failed IVF reasons should therefore begin by defining which stage did not progress. That prevents a generic answer from replacing a meaningful cycle review.

Egg Number and Egg Quality

Age and ovarian reserve influence the expected number of eggs and the chance that eggs are chromosomally competent. AMH helps estimate ovarian response to stimulation but is not a direct measure of egg quality.

A low egg yield may reflect ovarian reserve, stimulation response or cycle-specific variation. An apparently good response can still produce embryos that are chromosomally abnormal. Treatment planning should consider both quantity and age-related biology.

Related guide: recurrent implantation failure causes.

Sperm and Fertilisation Factors

Sperm concentration, motility, morphology and severe male-factor conditions can affect fertilisation. ICSI may be used when there is a clear indication, but it does not eliminate all sperm-related or genetic factors.

If fertilisation was unexpectedly low, the team should review egg maturity, sperm parameters, fertilisation method and laboratory observations before assuming that the next cycle simply needs ‘more ICSI’ or an unproven add-on.

Embryo Development and Transfer

Not every fertilised egg develops into a blastocyst. Embryo attrition is a normal part of IVF biology, though severe or repeated developmental problems may influence future planning.

Day 3 versus day 5 transfer decisions depend on embryo number, development, laboratory performance and the clinical plan. A negative test after a high-quality transfer may still occur because morphology cannot guarantee embryo competence.

For additional context, see low AMH vs egg quality.

Uterine and Endometrial Factors

Polyps, submucosal fibroids, adhesions, hydrosalpinx or other structural problems may affect implantation in selected patients. Endometrial preparation and progesterone timing are also important, especially in frozen embryo transfer cycles.

However, one failed transfer does not automatically justify an extensive implantation-failure work-up. The number and quality of embryos transferred and the patient’s age affect how unexpected the result really is.

What Should a Post-IVF Review Include?

A useful review asks: How many follicles developed? How many eggs were retrieved and mature? How many fertilised normally? How did embryos progress? Was transfer technically straightforward? Was the uterine cavity adequately assessed? Were medications and progesterone timed correctly? Was the pregnancy test performed at the recommended time?

Repeated IVF failure deserves a deeper review, but even then testing should be evidence-based. The objective is to identify modifiable factors rather than to add treatments simply because the previous cycle was unsuccessful.

IVF Failure Reasons Hyderabad: Planning the Next Step

For patients looking for IVF failure reasons Hyderabad guidance, bring the complete embryology and stimulation record to the review. A clinic cannot responsibly estimate the next step from age and AMH alone.

The next plan may involve adjusting stimulation, reviewing fertilisation strategy, treating a uterine finding, changing embryo-transfer timing, using donor gametes in selected cases, or repeating a similar approach when the previous result falls within expected biological variation.

Related Questions Patients Commonly Search

People researching this topic often use related phrases such as why IVF fails, failed IVF reasons, IVF failure after embryo transfer, repeated IVF failure, IVF implantation failure, and IVF failure reasons Hyderabad. These phrases describe overlapping questions, but diagnosis and treatment should be based on the individual clinical situation rather than on a search term.

When to Speak With a Fertility Specialist in Hyderabad

A specialist review is useful when symptoms, test results, age, previous treatment or the length of time trying to conceive make the next decision unclear. Bring previous reports and ask what finding is driving the recommendation, what alternatives are reasonable, and how success will be measured.

You can review day 3 vs day 5 embryo transfer for more context.

When you are ready for an individual review, thin endometrium IVF.

Practical Checklist Before Your Consultation

Before the appointment, use this checklist to turn online research into specific questions. It helps the clinician focus on findings that can change management and reduces the risk of ordering tests or procedures only because they are available.

  • At which stage did the IVF cycle narrow: response, egg maturity, fertilisation, embryo development or implantation?
  • Were sperm and egg factors reviewed together?
  • Was embryo-transfer timing and technique appropriate?
  • Is there evidence of a uterine-cavity issue?
  • What specific change is proposed for the next cycle, and why?

Bring previous reports, medication lists and procedure records where relevant. Ask for the reasoning behind each recommendation, the alternatives, the expected benefit and the point at which the plan would be reconsidered.

Frequently Asked Questions

1. Why does IVF fail even with good embryos?

Embryo appearance cannot reveal every chromosomal or biological factor, and implantation also depends on uterine, hormonal and transfer-related factors.

2. Is age the main IVF failure factor?

Age is a major predictor because it affects egg and embryo chromosomal competence, but it is not the only factor.

3. Does low AMH mean IVF will fail?

No. Low AMH mainly predicts lower ovarian response; it does not by itself determine egg quality or live birth.

4. Can poor sperm cause IVF failure?

Severe sperm problems can affect fertilisation and embryo development, although IVF-ICSI may overcome some fertilisation barriers.

5. Why do embryos stop growing?

Embryos may arrest because of chromosomal, egg, sperm or developmental factors. Some attrition is expected in every IVF cycle.

6. Does a negative test after embryo transfer mean implantation failure?

It means the transfer did not result in a detectable pregnancy. Whether it qualifies as recurrent implantation failure depends on the broader transfer history.

7. Should I do PGT-A after one failed IVF cycle?

Not automatically. The potential benefits and limitations depend on age, embryo number, previous history and treatment goals.

8. Can hysteroscopy help after IVF failure?

It may be useful when there is suspicion of uterine-cavity pathology, but it is not required after every failed cycle.

9. Does thin endometrium cause IVF failure?

A persistently thin lining may be clinically relevant, but treatment depends on the underlying cause and cycle context.

10. Should the IVF protocol always change after failure?

No. Sometimes the previous protocol was appropriate and the result reflected biological probability rather than a correctable mistake.

11. How soon can IVF be repeated?

Timing depends on physical recovery, ovarian response, emotional readiness, diagnosis and the clinician’s review.

12. Can stress alone cause IVF failure?

Stress is common during IVF, but it should not be blamed as the cause of an unsuccessful cycle.

13. What records are needed for a second opinion?

Bring stimulation sheets, hormone and scan data, egg maturity, fertilisation and embryo reports, transfer details, uterine evaluation and pregnancy results.

14. Can IVF work after multiple failures?

Yes. Future success depends on age, embryo availability, diagnosis and what the review identifies.

15. What is the first step after a failed IVF cycle?

Schedule a structured cycle review rather than immediately adding new tests or treatments.

Key Takeaway

The best use of information about IVF failure reasons is to improve the next clinical conversation. Use the article to understand the terminology and decision points, then confirm the diagnosis, evidence, risks and treatment options with the fertility team.

Category: Blog

Recurrent Implantation Failure: Causes, Tests & Treatment Options After Failed IVF

recurrent implantation failure causes

Recurrent implantation failure is one of the most difficult terms in fertility care because there has historically been no single universally accepted definition. A failed embryo transfer can occur for many reasons, and repeated unsuccessful transfers do not automatically prove that there is one hidden uterine or immune problem.

ASRM’s 2026 committee opinion recommends a probability-based approach to recurrent implantation failure, or RIF, and emphasizes careful review of embryo quality or ploidy, age, uterine factors, treatment details and previous transfers. Importantly, if a detailed review does not reveal a clear correctable cause, extensive testing and unproven treatment are not automatically beneficial.

For a related clinical pathway, review IVF treatment.

You may also find fertility investigations useful when planning the next step.

What Is Recurrent Implantation Failure?

Implantation begins when a blastocyst attaches to and penetrates the endometrium. Clinically, implantation may first be detected by hCG and later by ultrasound. Recurrent implantation failure refers to repeated failure of embryo transfer to achieve expected implantation.

ASRM now recommends defining RIF based on failure of the estimated number of good-quality blastocysts needed to reach a very high cumulative chance of a positive pregnancy test, rather than using a simple fixed number for every patient. Age, embryo testing and embryo quality influence that calculation.

Embryo Factors

Embryo chromosomal abnormality is a major reason for implantation failure, especially as maternal age increases. Even morphologically good embryos can be aneuploid. Embryo development, stage at transfer and laboratory factors also matter.

PGT-A may be discussed in selected patients, particularly when untested embryos are involved, but ASRM notes that it has not been shown to increase live birth for all patients with infertility or specifically for every patient with RIF. It should be a shared decision, not a universal add-on.

Related guide: IVF failure reasons.

Uterine and Endometrial Factors

Polyps, submucosal fibroids, intrauterine adhesions, hydrosalpinx, uterine anomalies and some other structural problems can interfere with implantation. Assessment may involve ultrasound, saline sonography, hysteroscopy or other imaging when indicated.

Thin endometrium or abnormal progesterone exposure may also be relevant in selected cycles, but evaluation should focus on findings that can realistically change management.

Male and Systemic Factors

Male factors can affect fertilisation and embryo development, while general health, smoking and certain medical conditions may influence reproductive outcomes. However, RIF should not become a reason to order every available blood, immune or sperm test.

The right evaluation starts with the details of the IVF cycle: number and stage of embryos transferred, embryo testing, endometrial preparation, transfer technique and previous outcomes.

For additional context, see thin endometrium and IVF.

Which Tests Are Not Routinely Supported?

Patients with repeated IVF failure are often offered immune panels, broad thrombophilia testing, endometrial receptivity tests and multiple add-on therapies. ASRM’s 2026 review concludes that evidence is insufficient for routine use of several such approaches, including routine ERA testing in RIF.

That does not mean no additional test is ever appropriate. It means each test should have a clear indication and a reasonable chance of changing a clinically meaningful decision.

Treatment After Repeated Implantation Failure

Treatment is directed at identified factors. A uterine lesion may be treated, embryo strategy may be reviewed, progesterone exposure may be optimized, and transfer technique can be assessed. If no correctable cause is found, proceeding with further embryo transfer may still be reasonable because many patients ultimately achieve pregnancy.

For recurrent implantation failure Hyderabad care, a second-look review of the complete IVF record is often more useful than immediately purchasing a package of add-ons.

Related Questions Patients Commonly Search

People researching this topic often use related phrases such as recurrent implantation failure, repeated IVF failure, embryo implantation failure causes, implantation failure tests, RIF treatment, and recurrent implantation failure Hyderabad. These phrases describe overlapping questions, but diagnosis and treatment should be based on the individual clinical situation rather than on a search term.

When to Speak With a Fertility Specialist in Hyderabad

A specialist review is useful when symptoms, test results, age, previous treatment or the length of time trying to conceive make the next decision unclear. Bring previous reports and ask what finding is driving the recommendation, what alternatives are reasonable, and how success will be measured.

You can review day 3 vs day 5 embryo transfer for more context.

When you are ready for an individual review, fertility specialist.

Practical Checklist Before Your Consultation

Before the appointment, use this checklist to turn online research into specific questions. It helps the clinician focus on findings that can change management and reduces the risk of ordering tests or procedures only because they are available.

  • How many embryos have been transferred and were they tested or untested?
  • Was the uterine cavity adequately evaluated?
  • Were progesterone exposure and transfer timing appropriate?
  • Is there a clear correctable factor, or are add-on tests being proposed without strong evidence?
  • What is the expected chance with another transfer based on age and embryo information?

Bring previous reports, medication lists and procedure records where relevant. Ask for the reasoning behind each recommendation, the alternatives, the expected benefit and the point at which the plan would be reconsidered.

Frequently Asked Questions

1. What is recurrent implantation failure?

It describes repeated failure of embryo transfer to achieve expected implantation, but the exact definition has varied historically.

2. How many failed transfers count as RIF?

There is no simple number for every patient. ASRM 2026 recommends considering embryo quality or ploidy, age and cumulative expected chance of implantation.

3. Is embryo aneuploidy a major cause?

Yes. Chromosomal abnormalities are an important cause of failed implantation, especially with increasing maternal age.

4. Does a good-looking embryo always implant?

No. Morphology cannot identify every chromosomal or biological factor that affects embryo competence.

5. Should everyone with failed IVF do PGT-A?

No. PGT-A may be discussed in selected cases, but it is not a universal solution and has not been shown to improve live birth for all patients.

6. Is ERA routinely recommended for RIF?

Current ASRM guidance states there is insufficient evidence to support routine ERA testing for RIF.

7. Can polyps or fibroids affect implantation?

Some intracavitary lesions can interfere with implantation and may warrant evaluation or treatment.

8. Does thin endometrium cause IVF failure?

Endometrial thickness is one factor. Its significance depends on the clinical situation, cycle preparation and underlying cause.

9. Are immune treatments proven for RIF?

Routine immunologic therapies are not supported by strong evidence for all patients with RIF.

10. Should sperm DNA fragmentation be checked after failed transfers?

Not automatically. It may be considered in selected male-factor or reproductive situations after specialist review.

11. Can pregnancy still happen after several failed transfers?

Yes. If no correctable cause is found, further embryo transfer may still result in pregnancy.

12. What records should I bring for a RIF review?

Bring stimulation records, embryo reports, PGT results if any, transfer notes, lining and progesterone information, hysteroscopy or imaging reports and prior pregnancy results.

13. Is RIF the same as recurrent miscarriage?

No. RIF refers to failure to establish implantation after embryo transfer, while recurrent pregnancy loss occurs after pregnancies have been established.

14. When should hysteroscopy be considered?

It may be useful when symptoms, imaging or treatment history raise concern about the uterine cavity.

15. What is the most useful first step after repeated failure?

A structured review of the diagnosis, embryos, uterine cavity, cycle preparation and transfer details before ordering broad add-on testing.

Key Takeaway

The best use of information about recurrent implantation failure causes is to improve the next clinical conversation. Use the article to understand the terminology and decision points, then confirm the diagnosis, evidence, risks and treatment options with the fertility team.

Scroll to Top

To Book an Appointment

+917670804424 📞 Call Now

Recent Posts