Best Fertility Centre – Dr. Swapna Naik

Author: Swapna

Painful bowel movements that flare up specifically around your period aren’t a typical digestive issue. If this pattern sounds familiar, bowel endometriosis may be the reason — even if you’ve already been told it’s IBS.

This condition is frequently misdiagnosed for years, simply because its symptoms overlap so closely with common gastrointestinal disorders. This guide explains what bowel endometriosis is, how it’s different from IBS, and what treatment looks like in Hyderabad.

What Is Bowel Endometriosis?

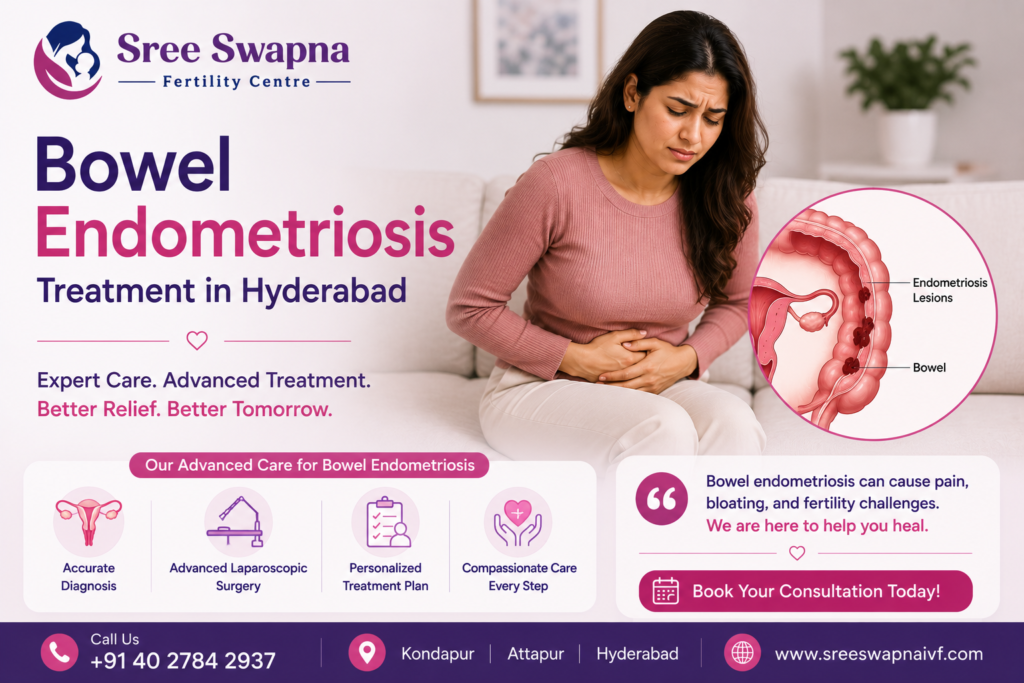
Bowel endometriosis happens when endometrial-like tissue — similar to the lining of the uterus — grows on the surface of, or sometimes into, the intestines. It most commonly affects the rectosigmoid colon (the lower part of the large intestine, closest to the rectum).

Like endometriosis elsewhere in the body, this misplaced tissue still responds to your monthly hormonal cycle, causing inflammation, pain, and sometimes bleeding tied specifically to your period.

Bowel Endometriosis vs. IBS: What’s the Difference?

This is the single most important distinction, since the two are frequently confused.

FeatureIBSBowel Endometriosis
Pain patternRandom, throughout the monthIntensifies specifically around your period
Bowel movement painVariableOften significantly worse during menstruation
Rectal bleedingUncommonCan occur, tied to cycle
Response to standard IBS treatmentUsually improvesOften doesn’t fully resolve

If your “IBS” symptoms have a clear monthly pattern tied to your cycle, it’s worth raising bowel endometriosis as a possibility with your doctor.

Common Symptoms of Bowel Endometriosis

  • Painful bowel movements (dyschezia), especially during your period
  • Constipation or diarrhoea, often worsening cyclically
  • Bloating and abdominal cramping
  • Rectal bleeding during menstruation
  • Nausea around your period
  • Deep pelvic pain, alongside typical endometriosis symptoms like painful periods

How Is Bowel Endometriosis Diagnosed?

Diagnosis can be genuinely challenging, and many women go through extensive gastrointestinal work-ups before the correct diagnosis is reached.

  • Pelvic Exam with Ultrasound: A rectovaginal exam combined with transvaginal ultrasound can help identify tenderness and suspicious areas
  • MRI: Provides a more detailed picture of deep infiltrating disease and helps guide surgical planning
  • Colonoscopy: Often has limited value here — since most bowel endometriosis lesions sit on the outside of the bowel wall, a colonoscopy (which examines the inside) frequently misses them entirely, unless the disease has progressed to involve the inner lining
  • Surgery: Remains the only definitive way to confirm a bowel endometriosis diagnosis with certainty, through direct visualisation and tissue sampling

This is exactly why a normal colonoscopy doesn’t rule out bowel endometriosis — a common source of diagnostic delay.

Treatment Options for Bowel Endometriosis

Medical (Hormonal) Treatment

  • Combined hormonal contraceptives (pills or patches), to reduce tissue growth and manage symptoms
  • Progestin-only therapy, including the hormonal IUD
  • GnRH agonists, to temporarily suppress hormone production and shrink the affected tissue

Medical management can meaningfully improve symptoms for many women. However, research shows a significant proportion of patients eventually move to surgery within about a year, due to persistent symptoms despite hormonal treatment.

Surgical Treatment

The right surgical approach depends on how deep and extensive the disease is:

  • Shave Excision: For superficial disease — the lesion is carefully shaved off the bowel surface without cutting into the bowel itself. Usually a same-day procedure.
  • Disc Resection: For a small, localised area of deeper involvement — a small portion of the bowel wall is removed and stitched closed.
  • Segmental Resection: For more extensive or deeply infiltrating disease — a larger section of bowel is removed, and the two ends are rejoined. In rare cases, a temporary colostomy may be needed during healing.

Surgery is typically performed laparoscopically, allowing for smaller incisions and generally faster recovery compared to open surgery.

Why an Accurate Diagnosis Matters Before Treatment

Because bowel endometriosis can closely mimic IBS, colitis, or other digestive conditions, getting the diagnosis right — rather than continuing to treat it as a purely gastrointestinal issue — is the most important step. A specialist experienced in deep infiltrating endometriosis will know to look beyond a normal colonoscopy result when your symptom pattern points toward a cyclic cause.

Bowel Endometriosis Treatment at Sree Swapna Fertility Centre

Bowel endometriosis requires a specialist comfortable with both gynaecological diagnosis and precise laparoscopic surgical technique.

Dr. Swapna Naik, Clinical Director at Sree Swapna Fertility Centre, is a trained laparoscopic surgeon with over 15 years of experience in reproductive medicine. Her approach starts with a thorough evaluation — including pelvic exam, transvaginal ultrasound, and further imaging where needed — to properly assess whether your symptoms point toward bowel involvement.

Both our Kondapur and Attapur clinics offer in-house diagnostic facilities, so if your digestive symptoms follow a clear monthly pattern and haven’t responded to standard IBS management, we can investigate the possibility of endometriosis properly, rather than continuing the same treatment cycle.

Frequently Asked Questions

1. What is bowel endometriosis? 

It’s a condition where endometrial-like tissue grows on or into the intestines, most commonly the rectosigmoid colon, causing cyclic digestive symptoms.

2. How is bowel endometriosis different from IBS? 

Bowel endometriosis symptoms typically intensify specifically around your period, while IBS symptoms tend to occur randomly throughout the month.

3. Can a colonoscopy diagnose bowel endometriosis? 

Often not — most lesions sit on the outside of the bowel wall, which a colonoscopy (examining the inside) may not detect.

4. What are the main symptoms of bowel endometriosis? 

Painful bowel movements, constipation or diarrhoea, bloating, and rectal bleeding, especially during menstruation.

5. Is surgery the only way to diagnose bowel endometriosis? 

Surgery with tissue sampling is currently the only definitive way to confirm the diagnosis, though imaging and exams can strongly suggest it beforehand.

6. Can bowel endometriosis be treated without surgery? 

Yes, hormonal treatment can improve symptoms for many women, though some eventually need surgery if symptoms persist.

7. What is shave excision surgery? 

A technique for superficial bowel endometriosis where the lesion is carefully removed from the bowel surface without cutting into the bowel itself.

8. What is segmental bowel resection? 

A surgical procedure for extensive disease where a portion of the bowel is removed and the remaining ends are rejoined.

9. Does bowel endometriosis surgery always require a colostomy? 

No, a temporary colostomy is only needed in rare, more extensive cases, not for most surgical procedures.

10. Can bowel endometriosis affect fertility? 

As a form of endometriosis, it’s often associated with broader pelvic disease, which can be linked to fertility challenges in some cases.

11. What imaging is used to diagnose bowel endometriosis? 

Transvaginal ultrasound and MRI are commonly used, alongside a detailed pelvic and rectovaginal exam.

12. How long can bowel endometriosis go undiagnosed? 

It’s not uncommon for women to go years without a correct diagnosis, since symptoms are frequently mistaken for IBS or other digestive conditions.

13. Is bowel endometriosis surgery performed laparoscopically? 

Yes, in most cases, allowing for smaller incisions and generally quicker recovery than open surgery.

14. Can hormonal treatment shrink bowel endometriosis lesions? 

Yes, in some cases, though it manages symptoms rather than permanently eliminating the tissue.

15. What percentage of patients eventually need surgery despite medical treatment? 

Research indicates a significant proportion of patients move to surgery within about a year due to persistent symptoms, though individual outcomes vary.

16. Can bowel endometriosis cause infertility? 

It can be part of broader endometriosis affecting fertility, though the specific impact varies by individual case.

17. Does bowel endometriosis always cause rectal bleeding? 

No, not all patients experience rectal bleeding — symptoms vary widely between individuals.

18. Is recovery from bowel resection surgery lengthy? 

Recovery varies by procedure type and extent of surgery; your surgeon will explain expected recovery time for your specific case.

19. Can bowel endometriosis come back after treatment? 

As with endometriosis elsewhere, recurrence is possible, and ongoing monitoring is generally recommended.

20. Should I see a gynaecologist or a gastroenterologist for suspected bowel endometriosis? 

Ideally a specialist experienced in both areas, or coordinated care between a gynaecologist and gastroenterologist.

21. What should I do if my “IBS” symptoms seem tied to my period? 

Raise this specific pattern with your doctor and ask about evaluation for bowel endometriosis, rather than continuing standard IBS treatment alone.

22. Where can I get bowel endometriosis evaluated in Hyderabad? 

Sree Swapna Fertility Centre offers diagnostic evaluation and laparoscopic surgical treatment for bowel endometriosis at both our Kondapur and Attapur clinics.

Conclusion

If your digestive symptoms follow your menstrual cycle rather than appearing randomly, it’s worth considering bowel endometriosis — even if you’ve been told it’s IBS before. With the right diagnostic approach and a specialist experienced in deep infiltrating endometriosis, both symptom relief and long-term treatment are genuinely achievable.

Get Your Symptoms Properly Evaluated

If your digestive symptoms seem to follow a monthly pattern, Dr. Swapna Naik and the team at Sree Swapna Fertility Centre can help identify what’s really going on.

📞 Call: +91 76708 04424 / +91 40 4995 3719 💬 WhatsApp: Message us directly 📧 Email: sreeswapna.fertility@gmail.com 📍 Visit us at: Kondapur (flagship centre) or Attapur, Hyderabad 🌐 Book an appointment: sreeswapnaivf.com/contact-us


Author: Swapna

Blocked fallopian tubes are one of the most common, yet least talked about, causes of female infertility.

Roughly 1 in 5 cases of female infertility trace back to a tubal problem. The good news: even when tubes are blocked, there are real, well-established treatment paths — including options that bypass the tubes entirely.

This guide explains what causes tubal blockage, how it’s diagnosed, and what treatment looks like in Hyderabad.

What Does “Blocked Fallopian Tubes” Actually Mean?

Fallopian tubes are the pathway where sperm meets the egg, and where a fertilised egg travels to the uterus. If a tube is blocked, sperm and egg can’t meet — or a fertilised egg can’t reach the uterus, increasing the risk of an ectopic (misplaced) pregnancy.

What Is Hydrosalpinx?

Hydrosalpinx is a specific type of tubal blockage, where the tube fills with fluid and becomes swollen, sometimes described as having a “sausage-like” shape on imaging.

This matters beyond just blocking the tube — the fluid inside a hydrosalpinx can leak back into the uterus, creating a toxic environment that can reduce the chances of successful implantation, even during IVF.

What Causes Blocked Fallopian Tubes?

  • Pelvic Inflammatory Disease (PID) — often caused by untreated sexually transmitted infections, particularly chlamydia
  • Endometriosis — which can cause scarring and adhesions around the tubes
  • Previous pelvic or abdominal surgery — leading to adhesions that distort or block the tubes
  • Prior tubal ligation — a deliberate sterilisation procedure, which can sometimes be reversed
  • Untreated infections following miscarriage, childbirth, or IUD-related complications in some cases

Symptoms of Blocked Fallopian Tubes

Many women have no symptoms at all — blocked tubes are often discovered only during a fertility investigation. When symptoms do occur, they may include:

  • Chronic pelvic pain
  • Unusual vaginal discharge
  • Pain during intercourse
  • A history of pelvic infections

How Are Blocked Fallopian Tubes Diagnosed?

  • Hysterosalpingogram (HSG): An X-ray procedure using contrast dye to check whether the tubes are open
  • Sonohysterography: An ultrasound-based alternative using fluid to assess tubal patency
  • Diagnostic Laparoscopy with Dye Test: A more direct, surgical method that also allows the doctor to see and treat certain issues at the same time

Your specialist will choose the right test based on your history and initial findings.

Treatment Options for Blocked Fallopian Tubes

1. Laparoscopic Tubal Surgery

For some cases — particularly mild blockages or adhesions — laparoscopic surgery can open or repair the tube. This works best when the damage is limited and the tube’s internal lining hasn’t been significantly affected.

2. Salpingectomy (Tube Removal)

When hydrosalpinx is present, removing the affected tube before IVF is a well-established recommendation, since it eliminates the harmful fluid that can interfere with implantation — significantly improving IVF success rates in these cases.

3. Proximal Tubal Occlusion

An alternative to full tube removal, this procedure blocks the tube near where it joins the uterus, preventing fluid from reaching the uterine cavity while leaving the tube itself in place.

4. IVF (Bypassing the Tubes Entirely)

For many women with blocked tubes — especially if both tubes are affected or severely damaged — IVF is often the most effective path to pregnancy, since it doesn’t rely on the fallopian tubes at all. Eggs are retrieved directly and fertilised in the lab, then transferred to the uterus.

Surgery vs. IVF: How Is the Decision Made?

FactorFavours SurgeryFavours IVF
Tube damageMild, limitedSevere, or hydrosalpinx present
Number of tubes affectedOne tubeBoth tubes
Age and ovarian reserveYounger, more time to try naturallyOlder, or lower ovarian reserve
Additional fertility factorsNoneMale factor or other issues also present

Your specialist will weigh these factors together — there’s no single “better” option, only the one that fits your specific diagnosis.

Blocked Fallopian Tube Treatment at Sree Swapna Fertility Centre

At Sree Swapna Fertility Centre, tubal factor infertility is evaluated thoroughly before recommending surgery, IVF, or both.

Dr. Swapna Naik, Clinical Director and a trained laparoscopic surgeon, brings over 15 years of experience in reproductive medicine and has guided more than 5,000 successful pregnancies, including many cases involving tubal factor infertility.

Both our Kondapur and Attapur clinics offer in-house diagnostic imaging and laparoscopic surgical facilities, along with a full IVF programme supported by our CLIA-certified embryology lab. If hydrosalpinx is identified, we’ll discuss whether tube removal before IVF is likely to improve your specific chances, based on your imaging findings — not a blanket recommendation applied to everyone.

Frequently Asked Questions

1. Can you get pregnant naturally with one blocked fallopian tube? 

Yes, it’s often still possible if the other tube is open and functioning normally.

2. What is hydrosalpinx? 

It’s a type of tubal blockage where the tube fills with fluid, which can also negatively affect IVF success if left untreated.

3. Do blocked fallopian tubes always cause symptoms? 

No, many women have no symptoms and only discover the blockage during a fertility evaluation.

4. What is an HSG test? 

A hysterosalpingogram is an X-ray procedure using contrast dye to check whether the fallopian tubes are open.

5. Can blocked fallopian tubes be unblocked? 

In some cases, laparoscopic surgery can open or repair mildly blocked tubes, though success depends on the extent of damage.

6. Why is hydrosalpinx removed before IVF? 

Because the fluid inside can leak into the uterus and reduce the chances of successful embryo implantation.

7. Is surgery always needed for blocked tubes? 

No, IVF is often recommended instead, especially for severe blockage or when both tubes are affected.

8. What causes fallopian tube blockage? 

Common causes include pelvic infections, endometriosis, prior surgery, and tubal ligation.

9. Can chlamydia cause tubal blockage? 

Yes, untreated chlamydia infection is a well-recognised cause of pelvic inflammatory disease, which can lead to tubal scarring and blockage.

10. Is laparoscopy used for both diagnosis and treatment? 

Yes, diagnostic laparoscopy can sometimes allow the doctor to treat certain issues, like adhesions, during the same procedure.

11. Does IVF work if both fallopian tubes are blocked? 

Yes, IVF bypasses the fallopian tubes entirely, making it an effective option even when both tubes are affected.

12. Can a tubal ligation be reversed? 

In some cases, yes, though success depends on the surgical method originally used and the length of remaining tube.

13. How long does it take to diagnose blocked tubes? 

This varies, but typically involves an initial consultation followed by imaging tests like HSG or sonohysterography.

14. Does removing a fallopian tube affect ovarian function? 

Generally no, since the ovary and its blood supply are usually separate from the tube itself, though this should be confirmed with your surgeon.

15. Can blocked tubes increase ectopic pregnancy risk? 

Yes, tubal damage is a recognised risk factor for ectopic pregnancy, since a fertilised egg may struggle to reach the uterus.

16. Is proximal tubal occlusion better than full tube removal? 

It’s an alternative that avoids removing the tube entirely while still preventing harmful fluid reflux — the right choice depends on individual anatomy and surgeon assessment.

17. Can tubal blockage be prevented? 

Prompt treatment of pelvic infections and STIs can reduce the risk of tubal scarring and blockage.

18. Does age affect the choice between surgery and IVF for tubal blockage? 

Yes, age and ovarian reserve are important factors, since IVF may be prioritised when time for natural conception is more limited.

19. Can I still get an ultrasound-based tubal test instead of an X-ray? 

Yes, sonohysterography is an ultrasound-based alternative to the traditional HSG test.

20. What happens if surgery doesn’t successfully open the tube? 

Your specialist will typically recommend moving to IVF as the next step.

21. Is tubal factor infertility common? 

Yes, it’s estimated to account for around 20% of female infertility cases.

22. Where can I get blocked fallopian tubes treated in Hyderabad? 

Sree Swapna Fertility Centre offers diagnosis, laparoscopic surgery, and IVF for tubal factor infertility at both our Kondapur and Attapur clinics.

Conclusion

Blocked fallopian tubes don’t have to mean the end of your path to pregnancy. Whether the right approach is surgical repair, tube removal before IVF, or moving straight to IVF, an accurate diagnosis is the foundation for choosing the treatment most likely to work for your specific situation.

Get Your Tubal Health Evaluated in Hyderabad

Dr. Swapna Naik and the team at Sree Swapna Fertility Centre can help determine whether surgery, IVF, or a combined approach is right for you.

📞 Call: +91 76708 04424 / +91 40 4995 3719 💬 WhatsApp: Message us directly 📧 Email: sreeswapna.fertility@gmail.com 📍 Visit us at: Kondapur (flagship centre) or Attapur, Hyderabad 🌐 Book an appointment: sreeswapnaivf.com/contact-us

Author: Swapna

Painful urination that gets worse around your period isn’t a typical UTI pattern. If it keeps happening, cycle after cycle, it’s worth asking whether something else is going on.

Bladder endometriosis is a rare but real cause of cyclic urinary pain — and it’s frequently mistaken for repeated urinary tract infections, delaying proper diagnosis for months or even years.

This guide explains what bladder endometriosis is, how to recognise it, and what treatment options are available in Hyderabad.

What Is Bladder Endometriosis?

Bladder endometriosis occurs when endometrial-like tissue — similar to the lining of your uterus — grows on or inside the wall of your bladder.

Like normal endometrial tissue, this misplaced tissue still responds to your monthly hormonal cycle. It thickens, breaks down, and bleeds each month — but because it’s on the bladder rather than inside the uterus, it has nowhere to go, leading to irritation, pain, and sometimes visible blood in the urine.

It’s a rare form of endometriosis. Among women with confirmed endometriosis, urinary tract involvement is uncommon, and the bladder is by far the most frequently affected urinary organ when it does occur.

Why Bladder Endometriosis Is Often Missed

The symptoms closely resemble a urinary tract infection (UTI) — burning urination, frequency, and pelvic discomfort. Many women are treated repeatedly for “recurrent UTIs” with antibiotics that don’t fully resolve the problem, simply because the underlying cause was never investigated.

The key clue that’s often overlooked: symptoms that follow a cyclic pattern, worsening around your period rather than appearing randomly.

Common Symptoms of Bladder Endometriosis

  • Painful urination (dysuria) that worsens around your period
  • Increased urinary frequency and urgency
  • Blood in urine (haematuria), especially during menstruation
  • Suprapubic (lower abdominal) pain or pressure
  • A feeling of incomplete bladder emptying
  • In some cases, urinary incontinence
  • Pelvic pain that overlaps with typical endometriosis symptoms, like painful periods

If you notice these symptoms specifically intensifying around your menstrual cycle, that pattern itself is a meaningful diagnostic clue.

How Is Bladder Endometriosis Diagnosed?

  • Transvaginal Ultrasound: Often the first step, and can detect bladder wall lesions with good accuracy in experienced hands
  • Cystoscopy: A procedure allowing direct visualisation inside the bladder, sometimes with biopsy to confirm diagnosis
  • MRI: Used for a more detailed picture, especially to assess how deep the lesion extends into the bladder wall
  • Urine Tests: To rule out an actual infection, since symptoms overlap significantly with UTIs

Because bladder endometriosis is rare, it’s often not the first thing considered — which is why persistent, cyclic urinary symptoms deserve a second look if standard UTI treatment isn’t resolving things.

Treatment Options for Bladder Endometriosis

Non-Surgical (Medical) Treatment

  • Hormonal therapy, including dienogest, has shown improvement in both urinary and pain symptoms in clinical case reports
  • GnRH agonists, to temporarily suppress hormone production and reduce lesion activity
  • Pain management, using NSAIDs for symptom control

Medical management can be effective, particularly for smaller, superficial lesions, and is often tried before considering surgery.

Surgical Treatment

  • Laparoscopic excision, removing the endometriosis tissue from the bladder wall while preserving bladder function
  • Cystoscopy-assisted laparoscopic techniques, allowing more precise removal while protecting healthy bladder tissue
  • Partial cystectomy, in more extensive cases where a larger portion of affected bladder tissue needs removal

Surgery is generally considered for larger lesions, deep infiltration into the bladder muscle, or when medical treatment hasn’t adequately controlled symptoms.

Why Untreated Bladder Endometriosis Shouldn’t Be Ignored

While rare, if left undiagnosed and untreated, deep infiltrating disease can occasionally extend toward the ureters — the tubes connecting the kidneys to the bladder — potentially affecting kidney function in severe, longstanding cases. This is uncommon, but it’s a genuine reason not to dismiss persistent, unexplained cyclic urinary symptoms.

Bladder Endometriosis Treatment at Sree Swapna Fertility Centre

Bladder endometriosis requires a specialist comfortable with both gynaecological diagnosis and surgical management — since misdiagnosis as a simple UTI is common, and proper treatment often involves precise laparoscopic technique.

Dr. Swapna Naik, Clinical Director at Sree Swapna Fertility Centre, brings over 15 years of experience in reproductive medicine and is a trained laparoscopic surgeon, allowing her to manage both the diagnostic and surgical aspects of conditions like bladder endometriosis directly.

Both our Kondapur and Attapur clinics offer in-house diagnostic ultrasound, so if your urinary symptoms follow a cyclic pattern that hasn’t responded to standard UTI treatment, we can properly investigate rather than repeating the same antibiotic course.

Frequently Asked Questions

1. What is bladder endometriosis? 

It’s a rare form of endometriosis where endometrial-like tissue grows on or inside the bladder wall, causing cyclic urinary symptoms.

2. How common is bladder endometriosis? 

It’s uncommon even among women with endometriosis, though the bladder is the most frequently affected urinary organ when urinary tract involvement occurs.

3. How is bladder endometriosis different from a UTI? 

Bladder endometriosis symptoms typically follow a cyclic pattern, worsening around your period, unlike a standard UTI.

4. Can bladder endometriosis cause blood in urine? 

Yes, cyclic haematuria (blood in urine during your period) is a recognised symptom of bladder endometriosis.

5. Is bladder endometriosis dangerous? 

While generally not immediately dangerous, deep or longstanding cases can occasionally affect nearby structures like the ureters if left untreated.

6. How is bladder endometriosis diagnosed? 

Typically through transvaginal ultrasound, and sometimes cystoscopy or MRI for more detailed evaluation.

7. Can bladder endometriosis be treated without surgery? 

Yes, hormonal treatment such as dienogest has shown improvement in both urinary and pain symptoms in some cases.

8. When is surgery needed for bladder endometriosis? 

Surgery is typically considered for larger lesions, deep infiltration into the bladder muscle, or when medical treatment hasn’t controlled symptoms.

9. What is cystoscopy-assisted laparoscopy? 

It’s a surgical technique combining bladder visualisation with laparoscopic surgery, allowing more precise removal of endometriosis tissue while preserving healthy bladder function.

10. Can bladder endometriosis affect fertility? 

As a form of endometriosis, it can be associated with broader pelvic endometriosis, which may affect fertility in some cases, though this varies individually.

11. Why is bladder endometriosis often misdiagnosed? 

Its symptoms closely resemble a urinary tract infection, so it’s frequently treated as recurrent UTIs before the underlying cause is properly investigated.

12. What is the main clue that distinguishes it from a UTI? 

A cyclic pattern of symptoms — worsening specifically around menstruation — is a key distinguishing feature.

13. Is dienogest effective for bladder endometriosis? 

Case reports have shown improvement in urinary and pain symptoms with dienogest, though treatment response varies by individual.

14. Can bladder endometriosis cause urinary incontinence? 

In rare cases, it has been associated with urinary incontinence, which resolved with appropriate treatment in documented cases.

15. Is a cystoscopy painful? 

It’s generally done under sedation or anaesthesia, and most women tolerate it well with manageable recovery.

16. Can bladder endometriosis come back after surgery? 

As with endometriosis elsewhere in the body, recurrence is possible, and ongoing monitoring is generally recommended.

17. Does bladder endometriosis always require a urologist? 

Ideally, a specialist experienced in both gynaecological and urological aspects should be involved, either directly or through coordinated care.

18. Can antibiotics treat bladder endometriosis? 

No, since it isn’t a bacterial infection, antibiotics won’t resolve the underlying tissue changes causing symptoms.

19. What tests rule out infection versus endometriosis? 

A urine culture can rule out an actual bacterial infection, helping distinguish it from endometriosis-related symptoms.

20. Is bladder endometriosis linked to other forms of endometriosis? 

Yes, it’s often associated with broader pelvic endometriosis, so a full pelvic evaluation is usually recommended alongside bladder-specific assessment.

21. How soon should I see a specialist if I suspect bladder endometriosis? 

If UTI-like symptoms keep recurring in a pattern tied to your period, it’s worth seeking a proper evaluation rather than repeating antibiotic courses.

22. Where can I get bladder endometriosis evaluated and treated in Hyderabad? 

Sree Swapna Fertility Centre offers diagnostic imaging and laparoscopic treatment for bladder endometriosis at both our Kondapur and Attapur clinics.

Conclusion

Recurring, cyclic urinary pain that doesn’t respond to standard UTI treatment deserves a closer look. Bladder endometriosis is rare, but recognisable once you know the pattern to watch for — and with the right diagnosis, both medical and surgical treatment options can bring real relief.

Get Your Urinary Symptoms Properly Evaluated

If your urinary pain seems to follow your menstrual cycle, Dr. Swapna Naik and the team at Sree Swapna Fertility Centre can help identify what’s really going on.

📞 Call: +91 76708 04424 / +91 40 4995 3719 💬 WhatsApp: Message us directly 📧 Email: sreeswapna.fertility@gmail.com 📍 Visit us at: Kondapur (flagship centre) or Attapur, Hyderabad 🌐 Book an appointment: sreeswapnaivf.com/contact-us
Author: Swapna

There’s no single “best” treatment for adenomyosis. The right answer depends entirely on your situation — your age, your symptoms, and whether you want to have children in the future.

What works well for one woman may be completely wrong for another. Instead of a generic list of options, this guide walks through common real-life scenarios, so you can see which treatment path is more likely to fit yours.

Scenario 1: “I’m in my 20s or early 30s, and I want children later.”

If future fertility is a priority, treatment usually focuses on controlling symptoms without removing the uterus or reducing fertility potential.

Typically recommended:

  • Hormonal treatment (birth control pills, hormonal IUD, or dienogest) to manage pain and bleeding
  • NSAIDs for period pain
  • If a localised adenomyoma is present, adenomyomectomy may be considered to remove it while preserving the uterus

Usually avoided at this stage: Hysterectomy, since it ends the possibility of future pregnancy.

Scenario 2: “I’m trying to conceive right now, and I’ve just been diagnosed.”

Here, treatment isn’t just about symptom relief — it’s about improving the uterine environment for conception.

Typically recommended:

  • A coordinated plan between your gynaecologist and a fertility specialist
  • If undergoing IVF, an extended GnRH agonist downregulation protocol before your cycle may be considered, based on current research
  • Frozen embryo transfer (FET), rather than fresh transfer, in some cases, allowing extra preparation time

Important: This scenario needs a specialist who handles both adenomyosis and fertility treatment together — not two separate doctors giving conflicting advice.

Scenario 3: “My periods are heavy and painful, but I’ve completed my family.”

If future pregnancy isn’t a priority, you have more treatment options available, including more permanent ones.

Typically recommended:

  • Hormonal IUD, often highly effective at reducing bleeding and pain
  • GnRH agonist therapy, for a defined treatment period
  • Uterine artery embolisation, for some cases
  • Hysterectomy, if symptoms are severe and you want a definitive, permanent solution

Scenario 4: “I’ve tried medication, but my symptoms haven’t improved.”

This is when specialists typically move toward more targeted options.

Typically recommended:

  • A repeat, more detailed ultrasound or MRI to reassess the extent of adenomyosis
  • Discussion of surgical options — adenomyomectomy for localised disease, or more definitive surgery for diffuse, severe cases
  • A second opinion, if you haven’t already gotten one, since ongoing symptoms may warrant a fresh diagnostic look

Scenario 5: “I have both adenomyosis and fibroids.”

This combination is common and needs a plan that addresses both conditions together, not just one in isolation.

Typically recommended:

  • Imaging that clearly distinguishes fibroid tissue from adenomyosis tissue, since treatment approaches differ
  • A combined treatment plan, since surgery for fibroids doesn’t automatically treat adenomyosis, and vice versa

Scenario 6: “My symptoms are mild, and I was just told I have adenomyosis on a scan.”

Not every case needs immediate, aggressive treatment.

Typically recommended:

  • Monitoring, with treatment introduced only if symptoms develop or worsen
  • Simple pain management for occasional discomfort
  • Regular follow-up imaging to track any changes over time

Why “Best” Really Means “Right for You”

Every treatment on this list is a legitimate, medically recognised option — the question is never which one is objectively superior, but which one fits your age, your symptoms, your fertility plans, and how you’ve responded to treatment so far.

This is exactly why a proper diagnostic evaluation should always come before a treatment recommendation, not the other way around.

How Sree Swapna Fertility Centre Approaches This Question

At Sree Swapna Fertility Centre, we don’t default to one treatment for every adenomyosis patient. Our clinical director, Dr. Swapna Naik (MBBS, MS in Obstetrics & Gynaecology, Fellowship in Reproductive Medicine & IVF), brings over 15 years of experience and has guided more than 5,000 successful pregnancies, giving her a broad, real-world view of how different treatment paths play out for different patients.

Every consultation starts with understanding your specific scenario — your symptoms, your age, your fertility goals — before any treatment is discussed. Both our Kondapur and Attapur clinics offer in-house diagnostic imaging, so your evaluation and treatment planning happen without unnecessary delays.

Frequently Asked Questions

1. Is there one universal best treatment for adenomyosis? 

No, the right treatment depends on your age, symptom severity, and fertility plans.

2. What’s the best option if I want children in the future? 

Hormonal management or adenomyomectomy (for localised cases) are generally preferred over hysterectomy.

3. Is hysterectomy always the best long-term solution? 

It’s the only treatment that removes adenomyosis completely, but it’s generally reserved for women who have completed childbearing.

4. What if medication doesn’t help my symptoms? 

Your specialist may recommend reassessing with more detailed imaging and discussing surgical options.

5. Can adenomyosis be treated without medication or surgery? 

In mild, asymptomatic cases, monitoring alone may be appropriate, with treatment introduced only if needed later.

6. Is a hormonal IUD effective for adenomyosis? 

Yes, it’s often effective at reducing bleeding and pain for many women.

7. What if I have adenomyosis and fibroids together? 

Both conditions need to be addressed as part of a combined treatment plan, since treating one doesn’t automatically treat the other.

8. Does age affect which treatment is recommended? 

Yes, age and fertility plans strongly influence whether conservative or more definitive treatment is suggested.

9. Can adenomyosis be treated while trying to conceive? 

Yes, but the approach is different — usually coordinated with a fertility specialist rather than treated purely for symptom relief.

10. Is surgery always necessary for adenomyosis? 

No, many women manage their symptoms successfully with medication alone.

11. What is the best treatment for severe, diffuse adenomyosis? 

This often requires more comprehensive management, potentially including extended hormonal therapy or, in some cases, hysterectomy if fertility isn’t a priority.

12. How do I know if my adenomyosis is mild or severe? 

This requires proper imaging — transvaginal ultrasound or MRI — reviewed by a specialist.

13. Can adenomyosis treatment change over time? 

Yes, treatment often evolves based on how your symptoms and fertility goals change over the years.

14. Should I get a second opinion if treatment isn’t working? 

Yes, especially if you’ve tried medication without improvement, a second opinion or repeat evaluation is a reasonable step.

15. Is GnRH agonist therapy a permanent treatment? 

No, it’s typically used for a limited period to manage symptoms or prepare for another treatment, such as an IVF cycle.

16. Can non-surgical treatment fail? 

Yes, for some women symptoms don’t respond adequately, which is when surgical options are usually discussed.

17. What if I’m unsure whether I want more children? 

It’s worth discussing this openly with your specialist, since it directly affects which treatment options make sense for you right now.

18. Does adenomyosis treatment differ between Kondapur and Attapur clinics? 

No, both clinics follow the same treatment approach and diagnostic standards under the same clinical team.

19. Can I switch treatment approaches if my situation changes? 

Yes, treatment plans can be revisited as your symptoms, age, or fertility goals evolve.

20. Is monitoring alone ever a valid treatment approach? 

Yes, for mild or asymptomatic cases, monitoring with periodic follow-up may be entirely appropriate.

21. What’s the first step in figuring out my best treatment option? 

A thorough consultation and imaging evaluation with a specialist experienced in both gynaecology and fertility care.

22. How do I book a consultation to discuss my adenomyosis treatment options? 

Call or WhatsApp Sree Swapna Fertility Centre, or book online through their website.

Conclusion

The best treatment for adenomyosis isn’t a fixed answer — it’s the one that matches your specific age, symptoms, and fertility goals. Working through your actual scenario with an experienced specialist is far more useful than searching for a single “best” option that applies to everyone.

Find the Right Treatment for Your Situation

Dr. Swapna Naik and the team at Sree Swapna Fertility Centre will help you understand which adenomyosis treatment genuinely fits your specific situation.

📞 Call: +91 76708 04424 / +91 40 4995 3719 💬 WhatsApp: Message us directly 📧 Email: sreeswapna.fertility@gmail.com 📍 Visit us at: Kondapur (flagship centre) or Attapur, Hyderabad 🌐 Book an appointment: sreeswapnaivf.com/contact-us

Author: Swapna

Timing matters more than most people realise when trying to conceive.

Out of your entire menstrual cycle, there are really only about 6 days when sex can actually lead to pregnancy. Miss this window, and even perfectly healthy sperm and eggs won’t meet.

This guide explains exactly when your fertile window happens, how to track it, and what to do if timing alone isn’t working.

What Is the Fertile Window?

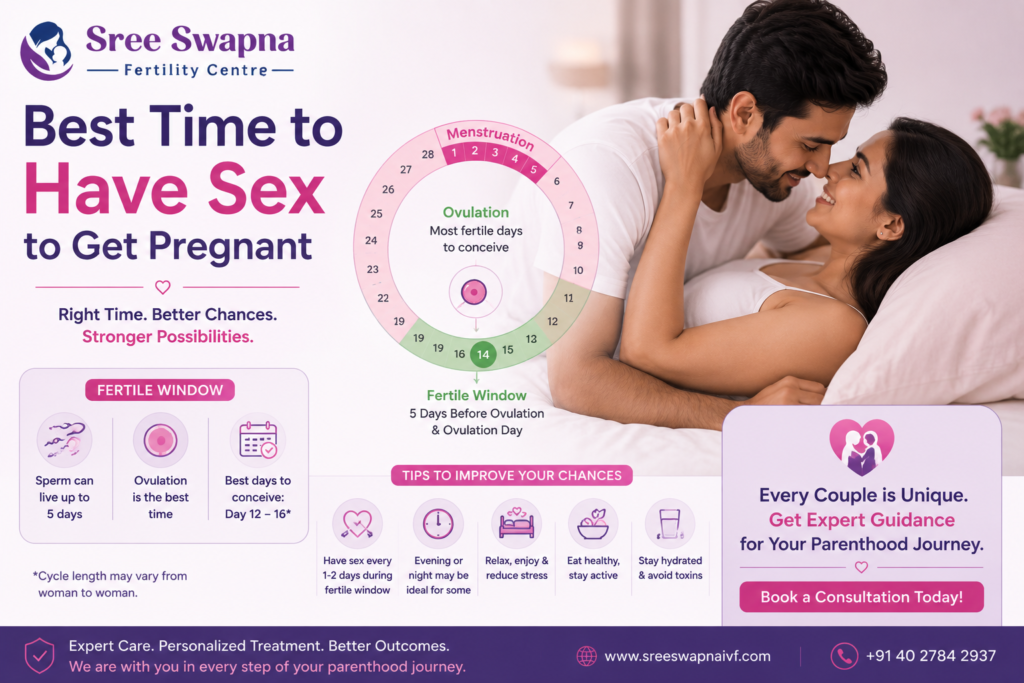
The fertile window is the span of days in your cycle when pregnancy is possible. It includes:

  • The 5 days before ovulation
  • The day of ovulation itself

This window exists because sperm can survive inside the female reproductive tract for up to 5 days, while an egg survives for only about 24 hours after release. Timing intercourse within this window gives sperm the best chance of being present when the egg is released.

When Does Ovulation Happen?

For a typical 28-day cycle, ovulation usually happens around day 14, counting from the first day of your period.

But here’s the catch: most women don’t have a perfectly regular 28-day cycle. Research shows real ovulation timing varies significantly between individuals — and even from month to month in the same woman.

This is why relying on a fixed “day 14” rule for everyone can lead you to miss your actual fertile window.

What’s the Single Best Day to Have Sex?

Research shows conception chances aren’t equal across the fertile window. They typically look like this:

  • 5–3 days before ovulation: Lower chance, around 5–10%
  • 2–1 days before ovulation: Highest chance, around 20–30%
  • Day of ovulation: Moderate chance, dropping off quickly
  • After ovulation: Chance drops close to zero

This means the 1–2 days right before ovulation are typically your best window — but predicting that exact day in advance is genuinely difficult, even with tracking tools.

How to Track Your Fertile Window

1. Calendar / Cycle Tracking

Track your cycle length over a few months to estimate your typical ovulation timing. This works best for women with regular cycles.

2. Ovulation Predictor Kits (OPKs)

These test urine for a surge in luteinising hormone (LH), which happens 24–36 hours before ovulation — giving you a short, more precise heads-up.

3. Basal Body Temperature (BBT)

Your body temperature rises slightly after ovulation. Tracking this daily can help confirm ovulation happened, though it tells you after the fact rather than predicting ahead.

4. Cervical Mucus Changes

Around ovulation, cervical mucus typically becomes clearer, stretchier, and more slippery — a natural sign your body is approaching peak fertility.

Do I Really Need to Time It Perfectly?

Not necessarily. Because predicting the exact day of ovulation is genuinely difficult — even with tracking — many fertility organisations recommend a simpler approach: having intercourse every 1–2 days throughout your cycle, rather than trying to hit one “perfect” day.

This approach naturally covers your fertile window without the stress of precise timing, and research supports it as an effective strategy for couples trying to conceive.

When Should You See a Fertility Specialist?

Timing intercourse correctly helps, but it isn’t the full picture. Consider seeing a specialist if:

  • You’re under 35 and haven’t conceived after 12 months of regular, unprotected intercourse
  • You’re 35 or older and haven’t conceived after 6 months
  • You have irregular or absent periods, making ovulation timing hard to predict
  • You have a known condition like PCOS, endometriosis, or a prior pelvic surgery
  • Your partner has a known or suspected sperm-related issue

Trying to time things perfectly for many months without success can be exhausting — and sometimes the issue isn’t timing at all, but something a specialist evaluation can identify.

Getting Support at Sree Swapna Fertility Centre

If you’ve been tracking your cycle carefully and timing intercourse correctly without success, it may be time for a proper fertility evaluation.

At Sree Swapna Fertility Centre, our clinical director, Dr. Swapna Naik (MBBS, MS in Obstetrics & Gynaecology, Fellowship in Reproductive Medicine & IVF), brings over 15 years of experience and has guided more than 5,000 successful pregnancies — including many couples who came to us after months of careful timing without results.

Both our Kondapur and Attapur clinics offer in-house diagnostic facilities, including ultrasound-based ovulation tracking and hormonal testing, to identify exactly what might be affecting your chances — rather than continuing to guess at timing alone.

Frequently Asked Questions

1. What is the fertile window? 

It’s the span of days in your cycle when pregnancy is possible — the 5 days before ovulation, plus the day of ovulation itself.

2. What day does ovulation usually happen? 

In a typical 28-day cycle, ovulation usually happens around day 14, though this varies significantly between individuals.

3. What is the single best day to have sex to get pregnant? 

Research suggests the 1–2 days right before ovulation offer the highest chance of conception.

4. How long does sperm survive inside the body? 

Sperm can survive in the female reproductive tract for up to 5 days.

5. How long does an egg survive after ovulation? 

An egg survives for approximately 24 hours after release.

6. Do I need to have sex every day to get pregnant? 

No, having intercourse every 1–2 days throughout your cycle is generally considered an effective, less stressful approach than trying to hit one exact day.

7. Can ovulation predictor kits help pinpoint the best day? 

Yes, OPKs detect a hormone surge that typically occurs 24–36 hours before ovulation, giving a useful advance signal.

8. Does basal body temperature tracking predict ovulation in advance? 

Not exactly — BBT confirms that ovulation has already happened, rather than predicting it beforehand.

9. Can irregular periods make timing harder? 

Yes, irregular cycles make ovulation timing much less predictable, and tracking tools may be less reliable.

10. Is day 14 always the day of ovulation? 

No, day 14 is a general average for a 28-day cycle, but actual ovulation timing varies widely between women and even cycle to cycle.

11. What does cervical mucus tell me about ovulation? 

Around ovulation, mucus typically becomes clearer, stretchier, and more slippery — a natural fertility sign.

12. How soon after sex can I take a pregnancy test? 

It’s generally recommended to wait until your missed period, about two weeks after ovulation, for an accurate result.

13. Can stress affect ovulation timing? 

Yes, significant stress can sometimes affect cycle regularity and ovulation timing in some women.

14. Does age affect the fertile window itself? 

Age doesn’t change the fertile window mechanics, but it can affect overall egg quality and quantity, which influences conception chances.

15. How many months of trying is considered “normal” before seeking help? 

Generally 12 months for women under 35, or 6 months for women 35 and older.

16. Can PCOS make ovulation timing unpredictable? 

Yes, PCOS often causes irregular or absent ovulation, making natural timing much harder to predict.

17. Is it possible to ovulate more than once in a cycle? 

It’s rare, but some women can release more than one egg around the same time, which is part of why multiple pregnancies sometimes occur.

18. Does having sex too often reduce sperm quality? 

Sperm quality can be slightly affected by very frequent ejaculation, but daily or every-other-day intercourse during the fertile window is generally not a concern for most men.

19. Can a fertility app accurately predict my ovulation day? 

Apps can help estimate a general range, but research shows even the most refined tracking methods have real limitations, especially for irregular cycles.

20. What tests can a fertility specialist do to check ovulation? 

Blood hormone tests and ultrasound-based follicle tracking can directly confirm whether and when ovulation is occurring.

21. Should both partners get evaluated if conception isn’t happening? 

Yes, fertility evaluation typically involves both partners, since male factors contribute to roughly half of infertility cases.

22. Where can I get a fertility evaluation in Hyderabad? 

Sree Swapna Fertility Centre offers comprehensive fertility evaluations, including ovulation tracking, at both our Kondapur and Attapur clinics.

Conclusion

Understanding your fertile window can meaningfully improve your chances of conceiving naturally — but perfect timing isn’t always the missing piece. If you’ve been trying for several months without success, a proper fertility evaluation can identify what timing alone can’t fix.

Ready for a Fertility Evaluation?

If timing hasn’t worked after several months of trying, Dr. Swapna Naik and the team at Sree Swapna Fertility Centre are here to help identify what’s really going on.

📞 Call: +91 76708 04424 / +91 40 4995 3719 💬 WhatsApp: Message us directly 📧 Email: sreeswapna.fertility@gmail.com 📍 Visit us at: Kondapur (flagship centre) or Attapur, Hyderabad 🌐 Book an appointment: sreeswapnaivf.com/contact-us

Author: Swapna

If you’ve searched for “best sex positions to get pregnant,” you’ve probably found long lists claiming certain positions work better than others.

Here’s the honest, science-based answer: no sex position has been proven to increase your chances of conceiving. The American Society for Reproductive Medicine states plainly that there’s no evidence linking coital position to conception rates.

That doesn’t mean nothing you do matters. It just means the things that actually move the needle are different from what most lists focus on. This guide explains what the research really says, and what genuinely helps.

What Does the Research Actually Say?

Multiple reviews, including a well-cited 2019 analysis in a Brazilian gynaecology journal, found no confirmed association between sexual position and pregnancy rates. Sperm are efficient swimmers, and transport through the reproductive tract happens largely through natural uterine contractions — not gravity or specific positioning.

Some MRI-based studies have confirmed that certain positions, like missionary or rear-entry, allow deeper penetration, placing semen closer to the cervix. This sounds like it should matter — but studies haven’t shown this translates into meaningfully higher pregnancy rates in couples without fertility issues.

Why the “Deep Penetration” Theory Doesn’t Hold Up in Practice

The idea makes intuitive sense: closer to the cervix should mean an easier journey for sperm. In reality, healthy sperm are designed to travel through the reproductive tract regardless of where they start. Once ejaculation occurs, sperm move toward the egg using their own motility and the help of natural uterine contractions — not by relying on where exactly they were deposited.

This is why couples conceive successfully using all sorts of positions, and why no single position has ever been shown, in properly designed studies, to reliably outperform others.

Does Lying Down After Sex Help?

This is a genuinely useful question, and the evidence here is a little more interesting.

A study looking at intrauterine insemination (IUI) found that women who rested lying down for about 15 minutes afterward had somewhat higher pregnancy rates. It’s reasonable to think a similar principle might apply to natural conception — resting briefly may help keep semen near the cervix rather than draining away.

That said, this evidence comes from an IUI context, not natural conception directly, so it should be seen as a small, low-effort thing that might help — not a guaranteed fix.

Does Female Orgasm Affect Conception?

Some research has explored whether female orgasm helps sperm transport, through uterine contractions. The evidence remains inconclusive and based on small studies. What’s clear is that arousal and comfort during sex support natural lubrication, which makes the whole experience easier — valuable in its own right, even if it isn’t a proven fertility booster.

What Actually Matters More Than Position

If you’re trying to conceive, research consistently points to these factors as far more important:

1. Timing Within Your Fertile Window

Having intercourse during the 5–6 days leading up to and including ovulation matters more than anything else on this list.

2. Frequency

Having sex every 1–2 days throughout your fertile window is a well-supported strategy, since it doesn’t rely on predicting the exact day of ovulation.

3. Sperm and Egg Health

Lifestyle factors like avoiding smoking, moderating alcohol, managing weight, and reducing stress support healthier sperm and egg quality over time.

4. Reducing Pressure Around Sex

Turning sex into a scheduled “task” can add stress, which isn’t helpful for either partner. Keeping intimacy relaxed and enjoyable matters for your wellbeing during what can already be an emotionally demanding process.

When Timing and Lifestyle Aren’t Enough

If you’ve been tracking ovulation, having regular intercourse, and taking care of your health — but still haven’t conceived after 12 months (or 6 months if you’re 35 or older) — it’s a good time to see a fertility specialist. Sometimes the missing piece isn’t timing or technique at all, but an underlying issue that needs a proper evaluation.

Getting Support at Sree Swapna Fertility Centre

If you’ve been doing everything “right” and still aren’t seeing results, it’s worth getting checked rather than continuing to guess.

At Sree Swapna Fertility Centre, our clinical director, Dr. Swapna Naik (MBBS, MS in Obstetrics & Gynaecology, Fellowship in Reproductive Medicine & IVF), brings over 15 years of experience and has guided more than 5,000 successful pregnancies — including many couples who came to us after months of careful, well-timed effort without success.

Both our Kondapur and Attapur clinics offer in-house diagnostic facilities, including ovulation tracking and hormonal testing, to identify what timing and lifestyle changes alone sometimes can’t.

Frequently Asked Questions

1. Does sex position affect the chances of getting pregnant? 

No, research consistently shows no confirmed link between sexual position and pregnancy rates.

2. What does the American Society for Reproductive Medicine say about sex positions?

ASRM states there’s no evidence that coital position affects fecundability (the chance of conceiving).

3. Does missionary position increase pregnancy chances? 

MRI studies show it allows deeper penetration, but this hasn’t been shown to meaningfully improve pregnancy rates.

4. Should I lie down after sex to help conception? 

Some evidence from IUI studies suggests brief resting afterward may help, though this isn’t proven for natural conception specifically. It’s a low-effort thing that may help.

5. Does female orgasm help you get pregnant? 

Evidence is inconclusive. Some studies suggest a possible link through uterine contractions, but it’s not considered a proven fertility factor.

6. What actually matters most for getting pregnant naturally? 

Timing intercourse within your fertile window and having regular intercourse throughout that window matter far more than position.

7. How long is the fertile window? 

Typically the 5–6 days leading up to and including ovulation.

8. How often should we have sex when trying to conceive? 

Every 1–2 days throughout your fertile window is a commonly recommended approach.

9. Can lifestyle factors affect fertility? 

Yes, smoking, excessive alcohol, and significant stress can all affect sperm and egg quality over time.

10. Is there a sex position that helps conceive a boy or girl? 

No, there’s no scientific evidence that any position or timing method can determine your baby’s sex.

11. Does gravity help sperm reach the egg? 

Not significantly — sperm are motile swimmers, and transport relies mainly on their own movement and natural uterine contractions.

12. Can too much stress about conceiving affect our chances? 

While the direct fertility impact is debated, ongoing stress can affect overall wellbeing and the experience of trying to conceive, so managing it matters.

13. Is doggy style or rear-entry better for deep penetration? 

Some studies confirm it allows very deep penetration, but this hasn’t been shown to translate into higher pregnancy rates.

14. How soon after ovulation does the fertile window close? 

The egg survives for about 24 hours after ovulation, after which conception becomes very unlikely until the next cycle.

15. Should we avoid certain positions if trying to conceive? 

No specific position needs to be avoided — any position that results in ejaculation within the vagina can lead to pregnancy.

16. Is there scientific proof that any position works better than others? 

No, current research does not support any position being definitively superior for conception.

17. Does an ovulation predictor kit help time intercourse better than counting days? 

Yes, research suggests using ovulation predictor kits improves timing accuracy compared to calendar counting alone.

18. How many months of trying is considered normal before seeking help? 

Generally 12 months for women under 35, or 6 months for women 35 and older.

19. Can both partners’ health affect how quickly we conceive? 

Yes, both male and female fertility factors contribute, so overall health matters for both partners.

20. Should we see a specialist even if we’ve only been trying for a few months? 

If you have known risk factors (irregular cycles, prior surgery, or age above 35), earlier evaluation is often reasonable — discuss timing with your doctor.

21. What tests can confirm if timing is really the issue? 

Hormonal blood tests and ultrasound-based ovulation tracking can help confirm whether ovulation is occurring as expected.

22. Where can I get a fertility evaluation in Hyderabad? 

Sree Swapna Fertility Centre offers comprehensive fertility evaluations at both our Kondapur and Attapur clinics.

Conclusion

Sex position simply isn’t the lever most couples think it is. What genuinely improves your chances of conceiving naturally is timing intercourse within your fertile window, having regular intercourse throughout it, and supporting overall reproductive health. If you’ve been doing all of this without success, a proper fertility evaluation — not a different position — is usually the more useful next step.

Ready for a Fertility Evaluation?

If timing and lifestyle changes haven’t worked after several months, Dr. Swapna Naik and the team at Sree Swapna Fertility Centre can help identify what’s really going on.

📞 Call: +91 76708 04424 / +91 40 4995 3719 💬 WhatsApp: Message us directly 📧 Email: sreeswapna.fertility@gmail.com 📍 Visit us at: Kondapur (flagship centre) or Attapur, Hyderabad 🌐 Book an appointment: sreeswapnaivf.com/contact-us

Author: Swapna

Searching for “the best gynaecologist in Hyderabad” usually turns up dozens of names, ads, and star ratings. It’s genuinely hard to tell who actually has the right expertise for your specific situation — especially when you need both IVF experience and laparoscopic surgery skill in the same doctor.

This isn’t a common combination. Many gynaecologists focus on one or the other. This guide explains what to actually look for, and why that combination matters for your treatment outcomes.

Why IVF and Laparoscopy Expertise Together Matters

Many fertility issues aren’t purely about IVF protocols — they involve underlying structural problems like fibroids, endometriosis, or blocked tubes, which sometimes need surgical correction before or alongside fertility treatment.

A gynaecologist who is only an IVF specialist may refer you elsewhere for surgery, adding time, cost, and a disconnect in your care. A gynaecologist who is only a surgeon may not have deep, current expertise in IVF protocols and embryology.

Finding a specialist skilled in both means one consistent doctor manages your full treatment journey — diagnosis, any needed surgery, and your IVF cycle — rather than juggling multiple specialists with different opinions.

What to Look for in a Top IVF Doctor in Hyderabad

1. Formal Qualifications and Fellowship Training

Look for a doctor with recognised qualifications in Obstetrics & Gynaecology, plus specific fellowship training in Reproductive Medicine and IVF — not just general gynaecology experience.

2. Years of Hands-On Experience

Experience matters, especially in complex cases. A doctor who has managed thousands of IVF cycles has likely seen a much wider range of patient scenarios than one earlier in their career.

3. Laparoscopic Surgical Skill

Since many fertility issues involve structural causes, a doctor trained in minimally invasive laparoscopic surgery can address these without referring you elsewhere.

4. In-House Diagnostic and Lab Facilities

A specialist backed by an in-house, well-equipped embryology lab and diagnostic imaging means fewer delays and more coordinated care.

5. Transparent, Personalised Communication

The best specialists explain your diagnosis and options clearly, set realistic expectations, and don’t push a one-size-fits-all treatment plan.

Meet Dr. Swapna Naik: Fertility & Laparoscopic Specialist in Hyderabad

Dr. Swapna Naik is the Clinical Director and Chief IVF Consultant at Sree Swapna Fertility Centre, with qualifications in Obstetrics & Gynaecology and a Fellowship in Reproductive Medicine & IVF.

With over 15 years of experience in reproductive medicine, she has personally guided more than 5,000 successful pregnancies — spanning IVF, ICSI, and complex cases involving both male and female factor infertility.

Dr. Naik combines her fertility expertise with hands-on laparoscopic surgical skill, allowing her to manage conditions like endometriosis, fibroids, PCOS, and tubal blockages directly — without needing to refer patients to a separate surgeon for related procedures.

What Patients Say

Across independent review platforms, Dr. Naik is consistently described by patients as attentive, patient in explaining treatment options, and reassuring during a difficult and emotional journey. Many patients specifically mention feeling heard and supported, rather than rushed through appointments — a quality that matters as much as clinical skill during fertility treatment.

Where to Consult Dr. Swapna Naik in Hyderabad

Dr. Naik consults at both Sree Swapna Fertility Centre locations:

  • Kondapur — 2nd Floor, GT/5, 1-51/192, Masjid Banda Rd, above Ratnadeep Building, Kondapur, Hyderabad – 500084. Easily accessible from Gachibowli, Madhapur, HITEC City, Miyapur, and Kukatpally.
  • Attapur — 3rd Floor, Naredi Square Building, Pillar No. 181, 304, Attapur, Upperpally, Hyderabad – 500039. Easily accessible from Rajendranagar, Mehdipatnam, and Tolichowki.

Both clinics are open Monday to Saturday, 9:00 AM to 7:00 PM, with Sunday consultations available by appointment.

What Makes Sree Swapna Fertility Centre Different

  • Combined IVF and surgical expertise under one specialist, reducing the need for multiple referrals
  • In-house CLIA-certified embryology lab with vitrification and time-lapse imaging technology
  • Full diagnostic and surgical facilities on-site, including ultrasound, OT, and andrology lab
  • Two convenient locations across Hyderabad, both led by the same clinical team
  • Personalised treatment plans, rather than a standard protocol applied to every patient

Frequently Asked Questions

1. What qualifications should I look for in an IVF specialist? 

Look for formal qualifications in Obstetrics & Gynaecology, along with specific fellowship training in Reproductive Medicine and IVF.

2. Why does laparoscopic skill matter for a fertility specialist? 

Many fertility issues involve structural problems like fibroids or endometriosis, which sometimes require surgical correction alongside fertility treatment.

3. Who is Dr. Swapna Naik? 

Dr. Swapna Naik is the Clinical Director and Chief IVF Consultant at Sree Swapna Fertility Centre, with over 15 years of experience in reproductive medicine.

4. Where does Dr. Swapna Naik consult in Hyderabad? 

She consults at both the Kondapur (flagship) and Attapur clinics of Sree Swapna Fertility Centre.

5. How many years of experience does Dr. Naik have? 

Over 15 years of experience in reproductive medicine and fertility care.

6. How many pregnancies has Dr. Naik guided? 

She has guided more than 5,000 successful pregnancies over her career.

7. Does Dr. Naik treat both male and female infertility? 

Yes, her practice covers comprehensive fertility care for both partners, including male factor infertility.

8. Can Dr. Naik perform laparoscopic surgery for fibroids or endometriosis? 

Yes, she combines fertility expertise with laparoscopic surgical skill to manage these conditions directly.

9. What treatments does Dr. Naik specialise in? 

IVF, ICSI, IUI, ovulation induction, fertility preservation, donor treatments, and minimally invasive laparoscopic surgery.

10. Is Dr. Naik available at both Sree Swapna clinics? 

Yes, she practices at both the Kondapur and Attapur centres.

11. What are the clinic timings? 

Monday to Saturday, 9:00 AM to 7:00 PM, with Sunday consultations available by appointment.

12. How do I book a consultation with Dr. Naik? 

You can call, WhatsApp, or book online through the Sree Swapna Fertility Centre website.

13. Does the clinic have an in-house embryology lab? 

Yes, both clinics are supported by a CLIA-certified embryology lab with advanced vitrification and time-lapse imaging technology.

14. What should I bring to my first consultation? 

Any previous test reports, semen analysis results, or treatment history, if available, though these aren’t mandatory for a first visit.

15. Is a single doctor better than seeing multiple specialists for fertility and surgery? 

It can offer more coordinated care, since one specialist manages diagnosis, any needed surgery, and IVF treatment without conflicting opinions between separate doctors.

16. Does Dr. Naik treat PCOS and PCOD? 

Yes, PCOS/PCOD management is part of her comprehensive fertility care offering.

17. Can I get a second opinion from Dr. Naik if I’ve had failed IVF cycles elsewhere? 

Yes, reviewing prior treatment history and getting a fresh diagnostic evaluation is a common and reasonable step.

18. Are both Sree Swapna clinics equally equipped? 

Yes, both the Kondapur and Attapur clinics follow the same clinical standards and diagnostic capabilities.

19. What is the first step to start treatment with Dr. Naik? 

Book a consultation, where your specific case and history will be reviewed before recommending a treatment plan.

20. Does Dr. Naik offer donor egg or donor sperm treatments? 

Yes, donor treatment programmes are part of the comprehensive fertility services offered.

21. Is Sree Swapna Fertility Centre accessible from HITEC City or Gachibowli? 

Yes, the Kondapur clinic is easily accessible from HITEC City, Gachibowli, Madhapur, and nearby areas.

22. How do I know if I need IVF or a simpler treatment first? 

This depends on your specific diagnosis. A thorough consultation will help determine whether IUI, surgery, or IVF is the right starting point for you.

Conclusion

Choosing the right gynaecologist for IVF and laparoscopy isn’t just about finding a well-reviewed name — it’s about finding a specialist with the right combination of fertility expertise, surgical skill, and honest, personalised communication. Dr. Swapna Naik brings all three, backed by over 15 years of experience and a track record of guiding thousands of families through their fertility journey.

Book a Consultation With Dr. Swapna Naik

Whether you need IVF, laparoscopic surgery, or both, Dr. Swapna Naik and the team at Sree Swapna Fertility Centre are here to guide you with clarity and compassion.

📞 Call: +91 76708 04424 / +91 40 4995 3719 💬 WhatsApp: Message us directly 📧 Email: sreeswapna.fertility@gmail.com 📍 Visit us at: Kondapur (flagship centre) or Attapur, Hyderabad 🌐 Book an appointment: sreeswapnaivf.com/contact-us
Author: Swapna

Hearing “zero sperm count” for the first time is genuinely frightening. Many men assume it means biological fatherhood is impossible.

That’s usually not true. Azoospermia — the medical term for zero sperm in the ejaculate — has multiple possible causes, and many of them are treatable.

This guide explains what causes azoospermia, how it’s diagnosed, what treatment options exist, and what affects the cost of treatment in Hyderabad.

What Is Azoospermia?

Azoospermia means no sperm is found in a man’s semen sample during a standard semen analysis. It affects a small percentage of men, and is one of the more serious findings in a male fertility work-up.

There are two main types, and the distinction matters a lot for treatment:

Obstructive Azoospermia

Sperm is being produced normally in the testes, but a blockage somewhere in the reproductive tract prevents it from reaching the ejaculate.

Non-Obstructive Azoospermia

The testes themselves are producing little to no sperm, due to a problem with sperm production itself — not a blockage.

What Causes Azoospermia?

Causes of Obstructive Azoospermia

  • Previous vasectomy
  • Congenital absence of the vas deferens (sometimes linked to genetic conditions)
  • Infections causing scarring and blockage
  • Prior surgery in the pelvic or groin area

Causes of Non-Obstructive Azoospermia

  • Hormonal imbalances affecting sperm production
  • Genetic conditions, such as Klinefelter syndrome or Y-chromosome microdeletions
  • Varicocele, in some cases
  • Prior chemotherapy or radiation exposure
  • Undescended testicles in childhood, if untreated
  • In some cases, no identifiable cause is found

How Is Azoospermia Diagnosed?

  • Repeat semen analysis — a single sample isn’t enough; at least two separate tests are typically needed to confirm azoospermia
  • Hormonal blood tests — checking FSH, LH, and testosterone levels helps distinguish obstructive from non-obstructive causes
  • Scrotal ultrasound — to check testicular structure and rule out obstruction
  • Genetic testing — recommended in cases of suspected non-obstructive azoospermia, to check for chromosomal or genetic causes
  • Testicular biopsy — sometimes needed to directly assess sperm production

Getting the type of azoospermia right is the single most important diagnostic step, since obstructive and non-obstructive cases are treated very differently.

Treatment Options for Azoospermia

For Obstructive Azoospermia

  • Surgical correction of the blockage (such as vasectomy reversal, if that’s the cause), which may restore natural sperm flow
  • Surgical sperm retrieval — since sperm production is normal, retrieval techniques like PESA or TESA generally have a high success rate in these cases

For Non-Obstructive Azoospermia

  • Hormonal treatment, if an imbalance is identified as the underlying cause
  • Varicocele repair, if a varicocele is contributing to poor sperm production
  • Surgical sperm retrieval (typically TESE or micro-TESE), which directly samples testicular tissue to search for any sperm present, even in small amounts

Surgical Sperm Retrieval Techniques Explained

TechniqueBest Suited ForGeneral Approach
PESA (Percutaneous Epididymal Sperm Aspiration)Obstructive azoospermiaNeedle aspiration from the epididymis
TESA (Testicular Sperm Aspiration)Both typesNeedle aspiration directly from testicular tissue
TESE (Testicular Sperm Extraction)Non-obstructive azoospermiaSmall tissue biopsy from the testes
Micro-TESESevere non-obstructive azoospermiaMicroscope-guided extraction targeting areas more likely to contain sperm

Retrieval success rates are generally higher for obstructive azoospermia (often reported around 90% in clinical literature) compared to non-obstructive azoospermia (typically in the 40–60% range, depending on the underlying cause). Any sperm retrieved is generally used with ICSI during an IVF cycle, since the very low sperm numbers involved usually require this technique for fertilisation.

What Affects the Cost of Azoospermia Treatment?

  • Diagnostic work-up — hormonal tests, ultrasound, and genetic testing all add to the initial cost
  • Type of retrieval procedure — micro-TESE is generally more involved than PESA or TESA, which can affect pricing
  • Anaesthesia used — local anaesthesia procedures are typically less costly than those requiring general anaesthesia
  • Combined ICSI/IVF cycle — since retrieved sperm is usually used immediately with ICSI, the total cost often includes the IVF cycle itself, not just the retrieval procedure
  • Need for repeat attempts — in some non-obstructive cases, more than one retrieval attempt may be needed

For an accurate cost estimate, this should be discussed after your diagnostic work-up, once your specific treatment pathway is clear — since obstructive and non-obstructive cases involve very different cost structures.

Setting Realistic Expectations

Not every case of non-obstructive azoospermia will result in successfully retrieved sperm, even with advanced techniques like micro-TESE. This is an important, honest conversation to have with your specialist before proceeding, so you understand the range of possible outcomes — including next steps like donor sperm, if retrieval is unsuccessful.

Azoospermia Treatment at Sree Swapna Fertility Centre

At Sree Swapna Fertility Centre, azoospermia is evaluated thoroughly before any treatment path is recommended. Our clinical director, Dr. Swapna Naik (MBBS, MS in Obstetrics & Gynaecology, Fellowship in Reproductive Medicine & IVF), brings over 15 years of experience and has guided more than 5,000 successful pregnancies, including cases involving significant male factor infertility.

Both our Kondapur and Attapur clinics offer in-house andrology testing and surgical sperm retrieval techniques (TESA/PESA), allowing diagnosis and treatment planning to happen without unnecessary delays or external referrals. Where retrieval is successful, our CLIA-certified embryology lab handles ICSI directly, keeping the entire process coordinated under one team.

We take time to explain whether your case is obstructive or non-obstructive, what that means for your treatment options, and what realistic outcomes look like — before any procedure is scheduled.

Frequently Asked Questions

1. Can a man with azoospermia still have biological children? 

In many cases, yes — through surgical sperm retrieval combined with ICSI, though outcomes depend on the underlying cause and type of azoospermia.

2. What is the difference between obstructive and non-obstructive azoospermia? 

Obstructive azoospermia involves normal sperm production blocked from reaching the ejaculate, while non-obstructive azoospermia involves a problem with sperm production itself.

3. Is azoospermia always permanent? 

Not always — some causes, like certain blockages or hormonal imbalances, are treatable and may restore sperm presence.

4. How is azoospermia diagnosed? 

Through repeat semen analysis, hormonal blood tests, scrotal ultrasound, and sometimes genetic testing or testicular biopsy.

5. What is PESA? 

Percutaneous Epididymal Sperm Aspiration — a needle-based technique to retrieve sperm from the epididymis, mainly used for obstructive azoospermia.

6. What is TESE? 

Testicular Sperm Extraction — a small tissue biopsy from the testes to search for sperm, typically used for non-obstructive azoospermia.

7. What is micro-TESE? 

A more precise, microscope-guided version of TESE, generally used in more severe non-obstructive cases to improve the chance of finding sperm.

8. Does surgical sperm retrieval always find sperm? 

No, especially in non-obstructive azoospermia, there’s a chance no viable sperm are found even with advanced techniques.

9. What happens if no sperm is found during retrieval? 

Your specialist will discuss further options, which may include donor sperm for IVF/ICSI.

10. Is surgical sperm retrieval painful? 

Most procedures are done under local or general anaesthesia, with manageable discomfort during recovery.

11. Can retrieved sperm be frozen for future use? 

Yes, if enough sperm is retrieved, it can typically be cryopreserved for future IVF/ICSI cycles.

12. Does azoospermia affect testosterone levels? 

Not always — azoospermia relates specifically to sperm production or transport, though some underlying causes can also affect hormone levels.

13. Can varicocele cause azoospermia? 

Yes, in some cases of non-obstructive azoospermia, varicocele is a contributing factor, and repair may help.

14. Is genetic testing necessary for all azoospermia cases? 

It’s generally recommended for non-obstructive azoospermia to check for genetic causes, though not always necessary for clear obstructive cases.

15. How successful is sperm retrieval in obstructive azoospermia? 

Clinical literature often reports success rates around 90%, since sperm production itself is normal in these cases.

16. How successful is sperm retrieval in non-obstructive azoospermia? 

Success rates are generally lower, often reported in the 40-60% range, depending on the underlying cause.

17. Does retrieved sperm require ICSI? 

Yes, since retrieval typically yields very limited sperm numbers, ICSI is generally used to achieve fertilisation during IVF.

18. Can vasectomy reversal treat obstructive azoospermia? 

Yes, if vasectomy is the cause, reversal surgery may restore natural sperm flow in some cases.

19. Is azoospermia treatment covered by insurance in India? 

Coverage varies by insurer and policy. Confirm directly with your provider regarding your specific treatment plan.

20. How long does the diagnostic process take? 

This varies, but typically involves multiple visits for semen analysis, hormonal testing, and imaging before a treatment plan is finalised.

21. Can lifestyle factors cause azoospermia? 

Some non-obstructive cases have been linked to factors like heat exposure or toxin exposure, though many cases have hormonal, genetic, or unidentified causes.

22. Where can I get azoospermia treatment in Hyderabad? 

Sree Swapna Fertility Centre offers diagnosis, surgical sperm retrieval, and ICSI treatment for azoospermia at both our Kondapur and Attapur clinics.

Conclusion

An azoospermia diagnosis isn’t the end of the road toward biological fatherhood. With the right diagnostic work-up to distinguish obstructive from non-obstructive causes, many men have real, evidence-based treatment options — from surgical correction to sperm retrieval combined with ICSI. The key is getting an accurate diagnosis first, before deciding on a treatment path.

Get Your Azoospermia Evaluated in Hyderabad

Dr. Swapna Naik and the team at Sree Swapna Fertility Centre can help you understand your specific diagnosis and the treatment options available to you.

📞 Call: +91 76708 04424 / +91 40 4995 3719 💬 WhatsApp: Message us directly 📧 Email: sreeswapna.fertility@gmail.com 📍 Visit us at: Kondapur (flagship centre) or Attapur, Hyderabad 🌐 Book an appointment: sreeswapnaivf.com/contact-us

Author: Swapna

If standard fertility treatments haven’t worked for you — particularly with very low ovarian reserve or premature ovarian insufficiency — you may have come across autologous stem cell therapy in your search for options.

Before anything else, here’s the most important thing to know: this is an investigational treatment in India, not an established, routine therapy. Any clinic offering it should say this clearly, upfront, before you consider it.

This article explains what autologous stem cell therapy actually is, what the current evidence says, and what to expect if you’re exploring it under a research protocol.

What Is Autologous Stem Cell Therapy for Infertility?

“Autologous” means the stem cells come from your own body — not a donor. In the context of fertility, this typically involves collecting stem cells (often from bone marrow) and introducing them into the ovaries, with the theoretical goal of supporting ovarian tissue function in women with very diminished ovarian reserve.

The idea is still being actively researched. It is not a guaranteed way to restore fertility, and it doesn’t work the same way for everyone it’s tried on.

Important: This Is Classified as Investigational in India

The Indian Council of Medical Research (ICMR) explicitly classifies stem cell use for infertility as investigational. This means:

  • It should only be offered as part of a registered clinical research protocol, not as a routine, guaranteed clinical service
  • Patients must give informed consent that clearly acknowledges the experimental nature of the treatment
  • Any clinic promising “guaranteed pregnancy” or similarly certain outcomes from this treatment should be treated as a serious red flag

A recent Supreme Court judgment (January 2026) further reinforced that stem cell interventions lacking sufficient scientific evidence cannot be offered as routine clinical services in India. This isn’t a technicality — it reflects the genuine, current state of scientific evidence.

Who Might Be Considered for This Approach?

Given its investigational status, this approach is typically discussed only for a narrow group of patients — generally those with:

  • Premature ovarian insufficiency (POI) or very significantly diminished ovarian reserve
  • Repeated failed IVF cycles due to poor ovarian response, where conventional options have been exhausted
  • A clear understanding that this is a research-based approach, not a standard treatment path

It’s generally not considered appropriate for women with completely atrophied ovaries or those well past menopause, given very limited likelihood of any meaningful response in these cases.

What Does the Process Generally Involve?

While specific protocols vary between research programmes, the general process typically includes:

  1. Thorough diagnostic evaluation to confirm eligibility and rule out other treatable causes
  2. Detailed counselling and informed consent, explaining the experimental nature, potential risks, and realistic expectations
  3. Stem cell collection, typically from bone marrow
  4. Processing and introduction of the prepared cells into the ovaries
  5. Monitoring, to assess any changes in ovarian markers and response over subsequent cycles

Every step should be documented as part of a research protocol, with the patient’s full understanding that outcomes are not predictable or guaranteed.

What Does the Current Evidence Say?

Research in this area is still early-stage. Some studies have reported changes in hormonal markers or occasional pregnancies in small patient groups, but the overall body of evidence remains limited, with small sample sizes and inconsistent results across studies globally.

This means:

  • It cannot be presented as a proven fertility solution
  • It should not be positioned as a replacement for established treatments like IVF, donor egg options, or other conventional approaches, when those remain viable
  • Anyone considering it should treat it as a research participation decision, not a standard treatment choice

Questions to Ask Before Considering This Treatment

  • Is this being offered under a registered research protocol?
  • What does the informed consent document say about expected outcomes?
  • What are the known risks of the collection and introduction procedure?
  • What happens if there’s no response — what are the next steps?
  • Has the clinic been transparent about the limited, evolving evidence base?

A reputable specialist will welcome these questions and answer them directly, without pressure to proceed.

Cost Considerations

Because this is a research-based, investigational approach rather than a standardised treatment, cost structures can vary significantly between institutions and depend on the specific protocol, monitoring required, and any associated diagnostic work-up.

We’d strongly encourage discussing cost transparently as part of the informed consent conversation, alongside the discussion of expected outcomes and risks.

Our Approach at Sree Swapna Fertility Centre

At Sree Swapna Fertility Centre, we take the investigational nature of autologous stem cell therapy seriously. Our clinical director, Dr. Swapna Naik (MBBS, MS in Obstetrics & Gynaecology, Fellowship in Reproductive Medicine & IVF), brings over 15 years of experience in reproductive medicine and has guided more than 5,000 successful pregnancies through established fertility treatments.

For patients who have exhausted conventional options and are exploring this research-based approach, we ensure full, honest counselling before any decision is made — including a clear explanation of the current evidence, realistic expectations, and the informed consent process required under applicable research guidelines.

We will never present this treatment as a guaranteed path to pregnancy. If conventional treatment — including IVF, donor egg options, or other approaches — remains a realistic and better-evidenced path for you, we’ll say so first.

Frequently Asked Questions

1. Is autologous stem cell therapy for infertility approved in India? 

No, it’s classified as investigational by ICMR, meaning it can only be offered under registered research protocols, not as a routine approved treatment.

2. Does stem cell therapy guarantee pregnancy? 

No. There’s no guarantee of pregnancy, and any clinic claiming otherwise should be treated with caution.

3. What does “autologous” mean in this context? 

It means the stem cells come from the patient’s own body, typically from bone marrow, rather than from a donor.

4. Who might this treatment be considered for? 

Generally women with premature ovarian insufficiency or very diminished ovarian reserve who have exhausted conventional fertility treatment options.

5. Is this the same as IVF? 

No, it’s a separate, investigational approach sometimes explored alongside or before IVF in specific cases, not a replacement for it.

6. What are the risks of the procedure? 

Risks are generally associated with the bone marrow collection procedure and cell introduction, similar to other minimally invasive procedures. Discuss specific risks with your specialist.

7. How is this different from egg freezing or donor eggs? 

Egg freezing and donor egg treatments are established, well-evidenced options. Stem cell therapy remains investigational with a much smaller evidence base.

8. Can this help women who are already in menopause? 

Its likelihood of meaningful response is considered very low in women with completely atrophied ovaries or well past menopause.

9. Is informed consent required for this treatment? 

Yes, and it should explicitly acknowledge the experimental nature of the treatment, as required by research ethics guidelines.

10. How long does the process take? 

This varies by protocol and individual response, and should be discussed in detail during your consultation.

11. Is this treatment available at every fertility clinic in India? 

No, it’s only appropriately offered by clinics operating within a registered research framework, with proper ethical oversight.

12. What happens if the treatment doesn’t produce a response? 

Your specialist should discuss alternative options, including established treatments, as part of your overall care plan.

13. Are there published success rate statistics for this treatment? 

Evidence remains limited and inconsistent globally, so reliable, generalisable success rate statistics aren’t currently well established.

14. Should I get a second opinion before considering this treatment? 

Yes, given its investigational status, a second opinion is a reasonable and encouraged step.

15. Does Sree Swapna Fertility Centre offer this treatment to everyone? 

No, it’s considered only for a narrow group of patients who meet specific criteria and have exhausted conventional treatment options, following thorough counselling.

16. Is this treatment reversible or does it carry long-term risks? 

Long-term data is still limited. This should be discussed thoroughly as part of the informed consent process before proceeding.

17. Can I ask to see the research protocol before agreeing to treatment? 

Yes, and a transparent clinic should be willing to explain the framework under which the treatment is being offered.

18. Is this treatment recommended as a first option for infertility? 

No, it’s generally considered only after conventional, well-evidenced treatments haven’t been successful.

19. How is eligibility for this treatment determined? 

Through a thorough diagnostic evaluation, including hormonal testing and ovarian reserve assessment, along with a review of prior treatment history.

20. What should I look out for if a clinic seems to oversell this treatment? 

Be cautious of clinics that promise guaranteed results, downplay the experimental nature, or don’t provide clear informed consent documentation.

Conclusion

Autologous stem cell therapy for infertility represents a genuinely researched area of reproductive medicine, but it remains investigational in India — not an established, guaranteed solution. If you’re exploring this option, the most important step is finding a clinic that’s transparent about the evidence, the risks, and the honest likelihood of success, rather than one that overstates what’s currently known.

Discuss Your Options With Our Team

If conventional fertility treatments haven’t worked for you, Dr. Swapna Naik and the team at Sree Swapna Fertility Centre can walk you through all available options — including honest counselling on investigational approaches — so you can make a fully informed decision.

📞 Call: +91 76708 04424 / +91 40 4995 3719 💬 WhatsApp: Message us directly 📧 Email: sreeswapna.fertility@gmail.com 📍 Visit us at: Kondapur (flagship centre) or Attapur, Hyderabad 🌐 Book an appointment: sreeswapnaivf.com/contact-us

Author: Swapna

If you’ve been trying to conceive without success, IUI is often the first fertility treatment your doctor will suggest — before anything more advanced.

It’s simpler than IVF, less invasive, and often the right starting point for many couples. But it’s not right for everyone, and understanding how it actually works helps set the right expectations.

This guide covers what IUI is, how the procedure works, who it’s suitable for, what affects success rates, and what drives the cost in Hyderabad.

What Is Artificial Insemination (IUI)?

Intrauterine Insemination (IUI), also called artificial insemination, is a fertility treatment where specially prepared sperm is placed directly into the uterus around the time of ovulation.

In natural conception, sperm has to travel from the vagina, through the cervix, into the uterus, and finally to the fallopian tube to meet the egg. IUI shortens this journey. It places sperm closer to the egg, giving it a head start.

The egg still needs to be fertilised naturally inside the body — IUI doesn’t fertilise the egg in a lab, which is what makes it different from IVF.

How Does IUI Work? Step by Step

1. Cycle Monitoring

Your doctor tracks your cycle using ultrasound and sometimes blood tests to pinpoint ovulation. Some cycles use fertility medication to stimulate egg development; others use your natural cycle.

2. Sperm Preparation

On the day of the procedure, a semen sample is “washed” in the lab. This process separates healthy, motile sperm from seminal fluid and other cells, concentrating the strongest sperm for use.

3. Timing the Procedure

Insemination is timed carefully — usually within 24 to 36 hours of ovulation, sometimes using a trigger injection to control exact timing.

4. The Insemination Itself

A thin catheter delivers the prepared sperm directly into the uterus. The procedure is quick, similar to a pap smear, and typically doesn’t require anaesthesia.

5. After the Procedure

Most women can resume normal activities immediately. A pregnancy test is usually done about two weeks later.

Who Is a Good Candidate for IUI?

IUI tends to work best for:

  • Mild male factor infertility — such as slightly low sperm count or reduced motility
  • Unexplained infertility — when no clear cause is found after testing
  • Ovulatory issues — such as PCOS, when combined with ovulation-inducing medication
  • Cervical factor infertility — where cervical mucus makes it harder for sperm to travel naturally
  • Single women or same-sex couples using donor sperm

When IUI Is Usually Not Recommended

  • Both fallopian tubes are blocked
  • Severe male factor infertility (very low sperm count or motility)
  • Advanced endometriosis
  • Significantly reduced egg quality or ovarian reserve

In these cases, your specialist will likely recommend moving directly to IVF, since IUI is unlikely to be effective.

What Affects IUI Success Rates?

Success isn’t the same for every patient. Several factors matter:

  • Female age — younger women generally see higher success rates per cycle
  • Underlying diagnosis — IUI works best for ovulatory issues and mild male factor infertility, less well for tubal or severe male factor issues
  • Number of cycles attempted — many specialists recommend trying 3 to 4 cycles before considering a different approach
  • Sperm quality after preparation — higher motile sperm counts after washing generally support better outcomes

It’s important to have realistic expectations. IUI doesn’t guarantee pregnancy in any individual case, and success rates are best discussed in the context of your specific diagnosis with your specialist — not as a single, universal number.

What Does IUI Cost in Hyderabad?

IUI is generally less expensive than IVF, since it doesn’t involve lab fertilisation or embryo culture. That said, several factors affect the actual cost:

  • Natural cycle vs. medicated cycle — using fertility medication to stimulate ovulation adds to the cost
  • Monitoring requirements — the number of ultrasound and blood test visits needed to track your cycle
  • Donor sperm, if required, adds an additional cost component
  • Number of cycles — since IUI often needs multiple attempts, total cost should be considered across cycles, not just one

For an exact cost, it’s best to get a personalised estimate after your initial consultation and diagnostic work-up, since your specific protocol will determine the final price.

IUI vs. IVF: How Do You Know Which One You Need?

FactorIUIIVF
InvasivenessLowModerate
Where fertilisation happensInside the bodyIn a lab
Best suited forMild male factor, unexplained infertility, ovulatory issuesTubal blockage, severe male factor, advanced endometriosis, failed IUI cycles
Relative costLowerHigher
Typical next step if unsuccessfulIVF, after 3–4 cyclesRepeat cycle or additional techniques (ICSI, PGT)

Your specialist will recommend one or the other based on your diagnostic results — not personal preference alone.

IUI Treatment at Sree Swapna Fertility Centre

Dr. Swapna Naik, Clinical Director at Sree Swapna Fertility Centre, has over 15 years of experience in reproductive medicine and has guided more than 5,000 successful pregnancies across the full range of fertility treatments, including IUI.

Every IUI cycle at our Kondapur and Attapur clinics starts with a proper diagnostic evaluation — for both partners — since IUI’s effectiveness depends heavily on choosing the right candidates. Our in-house andrology lab handles sperm preparation on-site, and our in-house ultrasound facilities allow close cycle monitoring without external referrals.

If IUI isn’t the right fit for your specific situation, we’ll say so — and explain why IVF or another approach may serve you better, rather than recommending a treatment that’s unlikely to succeed.

Frequently Asked Questions

1. What is the difference between IUI and IVF? 

IUI places prepared sperm into the uterus for natural fertilisation inside the body, while IVF fertilises eggs with sperm in a lab before transferring an embryo.

2. Is IUI painful? 

Most women experience mild discomfort, similar to a pap smear, rather than significant pain.

3. How many IUI cycles are usually recommended before switching to IVF? 

Most specialists recommend 3 to 4 cycles before considering a different treatment approach.

4. Can IUI be done with donor sperm? 

Yes, IUI can use partner sperm or donor sperm, depending on individual circumstances.

5. Does IUI require anaesthesia? 

No, the procedure typically doesn’t require anaesthesia.

6. How long does the IUI procedure take? 

The insemination itself usually takes only a few minutes, though the full appointment including monitoring may take longer.

7. What is sperm washing? 

It’s a lab process that separates healthy, motile sperm from seminal fluid, concentrating the strongest sperm for insemination.

8. Is IUI suitable for unexplained infertility? 

Yes, it’s commonly recommended for couples with unexplained infertility as an initial treatment approach.

9. Can IUI help with PCOS-related infertility? 

Yes, especially when combined with ovulation-inducing medication to regulate egg release.

10. Is IUI effective for severe male infertility? 

Generally no — severe male factor infertility usually responds better to IVF with ICSI.

11. How soon can I take a pregnancy test after IUI? 

Most specialists recommend waiting about two weeks before testing for accurate results.

12. Does age affect IUI success? 

Yes, younger women generally have higher success rates per cycle compared to older women.

13. Can IUI be done without fertility medication? 

Yes, a natural cycle IUI is possible, though a medicated cycle may improve outcomes for some patients.

14. What tests are needed before starting IUI? 

Typically, a semen analysis, ovulation assessment, and a check of fallopian tube patency are recommended beforehand.

15. Is IUI covered by insurance in India? 

Coverage varies by insurer and policy. Confirm directly with your insurance provider.

16. Can single women or same-sex couples opt for IUI? 

Yes, IUI with donor sperm is a common option for single women and same-sex couples.

17. What happens if IUI doesn’t work after several cycles? 

Your specialist will usually recommend a full re-evaluation and discuss moving to IVF or other treatment options.

18. Does IUI increase the chance of twins? 

If fertility medication is used to stimulate multiple egg development, there’s a higher chance of multiple pregnancy compared to a natural cycle.

19. Is bed rest needed after IUI? 

No, most women can resume normal activities immediately after the procedure.

20. How is IUI different from natural conception? 

IUI simply places prepared sperm closer to the egg — fertilisation itself still happens naturally inside the body.

21. Can blocked fallopian tubes affect IUI success? 

Yes, IUI is generally not recommended if both fallopian tubes are blocked, since the sperm and egg need functioning tubes to meet.

22. Where can I get IUI treatment in Hyderabad? 

Sree Swapna Fertility Centre offers IUI treatment with in-house sperm preparation and cycle monitoring at both our Kondapur and Attapur clinics.

Conclusion

IUI is often a sensible first step for many couples facing fertility challenges — simple, less invasive, and more affordable than IVF. But it isn’t right for every diagnosis. Getting a proper evaluation first ensures you’re choosing the treatment most likely to help, rather than starting with the wrong approach.

Book an IUI Consultation in Hyderabad

Dr. Swapna Naik and the team at Sree Swapna Fertility Centre will assess your specific case and recommend the right treatment path — honestly and clearly.

📞 Call: +91 76708 04424 / +91 40 4995 3719 💬 WhatsApp: Message us directly 📧 Email: sreeswapna.fertility@gmail.com 📍 Visit us at: Kondapur (flagship centre) or Attapur, Hyderabad 🌐 Book an appointment: sreeswapnaivf.com/contact-us

Scroll to Top

To Book an Appointment

+917670804424 📞 Call Now

Recent Posts