Best Fertility Centre – Dr. Swapna Naik

Author: Swapna

Choosing a fertility specialist is one of the more personal medical decisions you’ll make — you’re not just looking for qualifications on paper, but someone who will guide you through what can be an emotionally demanding journey with genuine skill and care.

Dr. Swapna Naik is the Clinical Director and Chief IVF Consultant at Sree Swapna Fertility Centre, recognised as one of the best fertility centers in Hyderabad, with over 15 years of experience in reproductive medicine and laparoscopic surgery.

Qualifications & Training

Dr. Naik’s training reflects a genuinely comprehensive foundation in both gynaecology and specialised reproductive medicine:

  • MBBS — foundational medical degree
  • DGO (Diploma in Gynaecology & Obstetrics)
  • DRM (Diploma in Reproductive Medicine)
  • DFM (Diploma in Fertility Medicine)
  • Diploma in Reproductive Medicine, Germany — advanced international training in assisted reproduction
  • Fellowship in Advanced ART (Assisted Reproductive Technology)
  • Trained Laparoscopic Surgeon

This combination — international training alongside hands-on surgical qualification — is genuinely uncommon, and it shapes how she approaches patient care: not treating fertility and surgical needs as separate problems requiring separate doctors, but as one connected picture.

Areas of Expertise

Dr. Naik’s practice spans the full range of fertility and reproductive care:

  • IVF (In Vitro Fertilisation) and ICSI (Intracytoplasmic Sperm Injection)
  • IUI (Intrauterine Insemination)
  • Ovulation induction for conditions like PCOS
  • Fertility preservation, including egg and embryo freezing
  • Donor treatments, including donor egg IVF
  • Laparoscopic and hysteroscopic surgery, for conditions like endometriosis, fibroids, and adenomyosis
  • Male factor infertility management, including surgical sperm retrieval (TESA/PESA)
  • PCOD/PCOS management

Her Approach to Patient Care

Fertility treatment involves more than a treatment protocol — it involves real people navigating uncertainty, hope, and sometimes repeated setbacks. Dr. Naik’s approach centres on:

  • Thorough, individualised diagnosis before recommending any treatment path
  • Clear, honest communication about realistic expectations, rather than overpromising outcomes
  • Treating both partners’ fertility factors as equally important, rather than focusing solely on the female partner
  • Combining medical and surgical expertise, so patients aren’t shuffled between multiple specialists for related issues

What Patients Say

Across independent review platforms, patients consistently describe Dr. Naik as attentive, patient in explaining treatment options, and reassuring during what is often an emotionally difficult journey. Many specifically mention feeling genuinely heard during consultations, rather than rushed through appointments — a quality that matters as much as clinical expertise during fertility treatment.

Where to Consult Dr. Swapna Naik

Dr. Naik practices at both Sree Swapna Fertility Centre locations in Hyderabad:

Kondapur (Flagship Centre)

📍 2nd Floor, GT/5, 1-51/192, Masjid Banda Rd, above Ratnadeep Building, Kondapur, Hyderabad – 500084 🗺️ Easily accessible from HITEC City, Gachibowli, Madhapur, Miyapur, and Kukatpally

Attapur

📍 3rd Floor, Naredi Square Building, Pillar No. 181, 304, Attapur, Upperpally, Hyderabad – 500039 🗺️ Easily accessible from Rajendranagar, Mehdipatnam, and Tolichowki

Clinic Timings: Monday – Saturday, 9:00 AM – 7:00 PM | Sunday: By appointment

Why Patients Choose Sree Swapna Fertility Centre

  • A specialist combining fertility medicine and surgical skill, reducing the need for multiple referrals
  • In-house CLIA-certified embryology lab, with vitrification and time-lapse imaging
  • Full diagnostic and surgical facilities on-site, including ultrasound, OT, and andrology lab
  • Two convenient locations across Hyderabad, both led by the same experienced clinical team
  • Personalised treatment plans, built around each patient’s specific diagnosis and goals

Frequently Asked Questions

1. What are Dr. Swapna Naik’s qualifications?

MBBS, DGO, DRM, DFM, a Diploma in Reproductive Medicine from Germany, and a Fellowship in Advanced ART, alongside training as a laparoscopic surgeon.

2. How many years of experience does Dr. Naik have?

Over 15 years of experience in reproductive medicine and laparoscopic surgery.

3. Where does Dr. Swapna Naik practice in Hyderabad?

She consults at both the Kondapur (flagship) and Attapur clinics of Sree Swapna Fertility Centre.

4. Does Dr. Naik treat male infertility as well?

Yes, her practice includes comprehensive male factor infertility management, including surgical sperm retrieval techniques.

5. What is Dr. Naik’s international training background?

She holds a Diploma in Reproductive Medicine from Germany, in addition to her Indian qualifications and fellowship training.

6. Can Dr. Naik perform laparoscopic surgery for endometriosis or fibroids?

Yes, she is a trained laparoscopic surgeon who manages conditions like endometriosis, fibroids, and adenomyosis directly.

7. What treatments does Dr. Naik specialise in?

IVF, ICSI, IUI, ovulation induction, fertility preservation, donor treatments, and laparoscopic/hysteroscopic surgery.

8. Is Dr. Naik available at both Sree Swapna clinics?

Yes, she practices at both the Kondapur and Attapur centres.

9. What are the clinic timings?

Monday to Saturday, 9:00 AM to 7:00 PM, with Sunday consultations available by appointment.

10. How do I book a consultation with Dr. Naik?

You can call, WhatsApp, or book online through the Sree Swapna Fertility Centre website.

11. Does Dr. Naik treat PCOS and PCOD?

Yes, PCOS/PCOD management is part of her comprehensive fertility care offering.

12. Does Sree Swapna Fertility Centre have an in-house embryology lab?

Yes, both clinics are supported by a CLIA-certified embryology lab with vitrification and time-lapse imaging technology.

13. What should I bring to my first consultation with Dr. Naik?

Any previous test reports, semen analysis results, or treatment history, if available — though these aren’t required for a first visit.

14. Can I get a second opinion from Dr. Naik after failed IVF cycles elsewhere?

Yes, reviewing prior treatment history and a fresh diagnostic evaluation is a common and reasonable step.

15. Does Dr. Naik offer donor egg or donor sperm treatments?

Yes, donor treatment programmes, including donor egg IVF, are part of her practice.

16. Is the Kondapur clinic accessible from HITEC City or Gachibowli?

Yes, the Kondapur clinic is easily accessible from HITEC City, Gachibowli, Madhapur, and nearby areas.

17. What makes Dr. Naik’s approach to fertility care different?

Her combination of advanced reproductive medicine training and hands-on surgical qualification allows her to manage both fertility and related surgical needs directly.

18. Are both Sree Swapna clinics equally equipped?

Yes, both the Kondapur and Attapur clinics follow the same clinical standards and diagnostic capabilities under Dr. Naik’s guidance.

19. What is the first step to start treatment with Dr. Naik?

Book a consultation, where your specific case and history will be reviewed before recommending a personalised treatment plan.

20. Does Dr. Naik perform surgical sperm retrieval procedures?

Yes, procedures like TESA and PESA for male factor infertility are part of her practice.

21. How experienced is Dr. Naik with complex fertility cases?

With over 15 years of experience and a track record of guiding thousands of patients through fertility treatment, she has managed a wide range of straightforward and complex cases.

22. Where can I find the best fertility doctor in Hyderabad for a combined medical and surgical approach?

Dr. Swapna Naik at Sree Swapna Fertility Centre offers this combined expertise at both the Kondapur and Attapur clinics.

Conclusion

Choosing a fertility specialist means looking for genuine expertise, honest communication, and a treatment philosophy that puts your specific situation first — not a generic protocol. Dr. Swapna Naik brings comprehensive qualifications, international training, and over 15 years of hands-on experience to every patient she sees at Sree Swapna Fertility Centre, a trusted best fertility center in Hyderabad.

Book a Consultation With Dr. Swapna Naik

Whether you need IVF, laparoscopic surgery, or a comprehensive fertility evaluation, Dr. Swapna Naik and the team at Sree Swapna Fertility Centre are here to guide you with clarity and compassion.

📞 Call: +91 76708 04424 / +91 40 4995 3719 💬 WhatsApp: Message us directly 📧 Email: sreeswapna.fertility@gmail.com 📍 Visit us at: Kondapur (flagship centre) or Attapur, Hyderabad 🌐 Book an appointment: sreeswapnaivf.com/contact-us


Author: Swapna

Being told donor eggs might be the right path forward can feel like a lot to process at once — emotionally and practically. It’s worth knowing upfront: this is a well-established, legally regulated, and often highly effective option, not a last resort.

This guide walks through how donor egg IVF actually works, India’s legal framework around it, what affects cost, and what current research says about success rates.

When Is Donor Egg IVF Recommended?

Donor eggs are typically recommended when:

  • Age-related decline in egg quantity or quality makes conception with your own eggs unlikely to succeed
  • Premature ovarian insufficiency or very low ovarian reserve is present
  • Repeated IVF failures using your own eggs, despite good embryo transfer conditions
  • Genetic conditions that could be passed on through your own eggs
  • Certain medical conditions, such as Turner syndrome, where ovarian function is absent or severely reduced

How Does Donor Egg IVF Actually Work?

  1. Donor selection: A donor is matched from an ICMR-registered ART bank, based on physical characteristics and medical screening — not chosen directly by you, since Indian law requires anonymous donation
  2. Donor screening: Donors undergo thorough medical, genetic, and infectious disease testing (including HIV, hepatitis B and C, and syphilis) before being accepted into an ART bank
  3. Cycle synchronisation: Your uterine lining is prepared with hormonal medication to align with the donor’s egg retrieval and fertilisation timeline
  4. Fertilisation: Donor eggs are fertilised with sperm (your partner’s or donor sperm, depending on your situation) in the lab
  5. Embryo transfer: The resulting embryo is transferred into your uterus
  6. Pregnancy support: Hormonal support continues in early pregnancy to support implantation

You carry the pregnancy and are the legal mother of the child — the egg donor has no legal parental rights under Indian law.

The Legal Framework: India’s ART Act, 2021

Egg donation in India is governed by the Assisted Reproductive Technology (Regulation) Act, 2021, which came into effect in January 2023, along with subsequent ART Rules. Key protections built into this framework include:

  • Mandatory registration: Egg donation must go through an ICMR-registered ART bank — informal or independent arrangements are illegal
  • Anonymity: Neither the recipient nor the donor learns the other’s identity; you receive relevant medical and physical characteristics, but not identifying details
  • Donor eligibility criteria: Donors must fall within a specific age range and undergo thorough health screening
  • Donation limits: Current regulations restrict how often and to how many recipients a single donor can donate, to protect donor health and limit genetic overlap between offspring
  • Mandatory donor insurance: The treating clinic or commissioning couple must provide insurance coverage for the donor, protecting her against health risks related to the donation process
  • Altruistic donation only: Commercial sale of eggs is not permitted; donation must be voluntary, within the compensation framework set by law

Because this legal framework is genuinely detailed, it’s worth directly asking any clinic you’re considering whether their donor eggs are sourced through a registered ART bank — this protects you, the donor, and any child born from the treatment.

What Does Current Research Say About Success Rates?

Donor egg IVF is generally associated with meaningfully higher success rates than IVF using a patient’s own eggs, particularly for women facing age-related decline in egg quality or diminished ovarian reserve. This makes sense biologically: since donors are young and thoroughly screened, embryo quality and chromosomal normality rates tend to be significantly better than with eggs affected by age-related decline.

Reported clinical pregnancy and success rates for donor egg IVF vary across published sources, generally falling in a notably higher range than typical self-cycle IVF success rates for older patients or those with diminished ovarian reserve. It’s worth asking any clinic directly for their own reported live birth rate specifically for donor egg cycles, rather than relying on a single generic industry figure, since individual clinic outcomes can vary based on lab quality, protocol, and patient population.

What Affects the Cost of Donor Egg IVF?

  • Donor matching and screening costs, which form part of the overall ART bank process
  • Your own cycle preparation, including hormonal medication to prepare the uterine lining
  • Fertilisation method used (conventional IVF vs. ICSI, depending on sperm quality)
  • Number of embryo transfer attempts needed
  • Additional testing, such as genetic screening of embryos, if opted for

Reported costs for donor egg IVF in India vary meaningfully depending on the clinic, city, and specific protocol used. For an accurate, personalised estimate, it’s best to discuss your specific situation directly with your treating clinic rather than relying on a generic published range.

Emotional Considerations Worth Acknowledging

Choosing donor eggs is not just a medical decision — many recipients experience complex feelings around genetic connection, and this is a completely normal part of the process. Counselling support, before and during treatment, is strongly recommended, and a good clinic will make space for this conversation rather than rushing past it.

It’s also worth knowing that during pregnancy, your body’s hormonal, physical, and emotional environment plays a genuine role in your baby’s development — the connection you build with your child begins well before birth and isn’t limited to genetics alone.

Donor Egg IVF at Sree Swapna Fertility Centre

As a best fertility center in Hyderabad for comprehensive fertility care, we source donor eggs exclusively through ICMR-registered ART banks, in full compliance with the ART Act, 2021.

Dr. Swapna Naik, Clinical Director at Sree Swapna Fertility Centre, brings over 15 years of experience in reproductive medicine and has guided more than 5,000 successful pregnancies, including patients who conceived through donor egg treatment. Our team provides thorough donor matching support, transparent legal guidance, and counselling support throughout the process — at both our Kondapur and Attapur clinics.

For an accurate, personalised cost estimate and realistic success rate discussion based on your specific medical profile, we recommend a detailed consultation rather than relying on generic published figures.

Frequently Asked Questions

1. When is donor egg IVF recommended?

It’s typically recommended for age-related decline in egg quality, premature ovarian insufficiency, repeated IVF failures with your own eggs, or certain genetic or medical conditions.

2. Is egg donation legal in India?

Yes, it’s legal and regulated under the Assisted Reproductive Technology (Regulation) Act, 2021, and must be conducted through ICMR-registered ART banks.

3. Can I choose my own egg donor directly?

No, Indian law requires anonymous donation through a registered ART bank — you receive relevant medical and physical characteristics, but not the donor’s identity.

4. Who is the legal mother of a child born through donor egg IVF?

You are — the recipient carries the pregnancy and is the legal mother, with the egg donor having no parental rights under Indian law.

5. Are donor eggs in India properly screened?

Yes, donors undergo thorough medical, genetic, and infectious disease screening before being accepted by a registered ART bank.

6. Is donor egg IVF more successful than IVF with my own eggs?

Generally, yes, particularly for women with age-related decline in egg quality or diminished ovarian reserve, since donor eggs come from young, screened donors.

7. How much does donor egg IVF cost in India?

Costs vary depending on the clinic, city, and specific protocol used — it’s best to get a personalised estimate directly from your treating clinic.

8. Does my partner’s sperm get used with donor eggs?

Yes, typically your partner’s sperm is used to fertilise the donor eggs, unless donor sperm is also needed for your specific situation.

9. Is counselling recommended before donor egg IVF?

Yes, given the emotional considerations around genetic connection, counselling support is strongly recommended and should be offered by your clinic.

10. Can a donor donate eggs more than once?

Current regulations place specific limits on donation frequency and the number of recipients per donor, to protect donor health and limit genetic overlap.

11. Is donor egg IVF the same process as regular IVF?

It’s similar, with the key difference being that donor eggs, rather than your own, are fertilised and transferred, requiring cycle synchronisation between donor and recipient.

12. How is the donor matched to me?

Matching is generally based on physical characteristics and medical history, coordinated through the registered ART bank rather than direct selection.

13. Is commercial sale of eggs allowed in India?

No, only altruistic, voluntary donation is permitted under the ART Act, within the legally defined compensation framework.

14. Does the child have any legal right to donor information later in life?

Non-identifying medical and health information may be accessible under specific circumstances defined by law, though full donor identity remains protected.

15. Can international or NRI patients access donor egg IVF in India?

Yes, many clinics in India treat international and NRI patients for donor egg IVF, subject to applicable legal and documentation requirements.

16. Is insurance provided for egg donors in India?

Yes, mandatory insurance coverage for the donor is a legal requirement under the ART Act, 2021.

17. How many embryo transfer attempts are typically needed?

This varies by individual case — some patients conceive on the first transfer, while others may need more than one attempt.

18. Does age of the recipient affect donor egg IVF success?

The donor’s age is generally considered the primary factor for egg quality, though the recipient’s uterine health also plays an important role in implantation success.

19. What tests are done on the recipient before donor egg IVF?

Uterine evaluation, hormonal assessment, and overall health screening are typically part of preparing for donor egg IVF.

20. Can genetic testing be done on embryos from donor eggs?

Yes, genetic screening (PGT) can be added to donor egg IVF cycles if desired, as an additional step.

21. Is donor egg IVF a good option after multiple failed IVF cycles?

It can be, particularly if repeated failures are linked to egg quality issues — this is worth discussing in detail with your specialist based on your specific history.

22. Where can I access donor egg IVF through a registered ART bank in Hyderabad?

Sree Swapna Fertility Centre, recognised as a best fertility center in Hyderabad, sources donor eggs exclusively through ICMR-registered ART banks at both our Kondapur and Attapur clinics.

Conclusion

Donor egg IVF is a well-established, legally protected, and often highly effective path to parenthood — not a fallback option, but a genuinely strong choice for the right clinical situation. Understanding the legal framework, realistic success rates, and what genuinely affects cost can help you approach this decision with clarity rather than uncertainty.

Discuss Donor Egg IVF With Our Team

Dr. Swapna Naik and the team at Sree Swapna Fertility Centre, a trusted best fertility center in Hyderabad, are here to guide you through the process with honesty and care.

📞 Call: +91 76708 04424 / +91 40 4995 3719 💬 WhatsApp: Message us directly 📧 Email: sreeswapna.fertility@gmail.com 📍 Visit us at: Kondapur (flagship centre) or Attapur, Hyderabad 🌐 Book an appointment: sreeswapnaivf.com/contact-us

Author: Swapna

PCOS affects pregnancy in two distinct ways — first, by making it harder to conceive in the first place, and second, by increasing certain risks once pregnancy happens. Understanding both halves of this picture helps you prepare properly, rather than worrying about the wrong thing at the wrong time.

How PCOS Affects Getting Pregnant

The main barrier PCOS creates is irregular or absent ovulation. Without regular ovulation, there’s no egg released each month for sperm to fertilise — which is why irregular periods are often the first clue pointing toward PCOS during a fertility evaluation.

The encouraging part: this is also the most treatable part of PCOS-related infertility.

Ovulation Induction: What’s Changed

For years, clomiphene citrate was the standard first medication used to trigger ovulation in PCOS. That’s changed. Current international guidelines now recommend letrozole as the preferred first-line treatment for PCOS-related anovulatory infertility.

The evidence behind this shift is fairly striking. A major clinical trial found letrozole led to higher ovulation rates (61.7% vs. 48.3%) and higher clinical pregnancy rates (41.9% vs. 28.2%) compared to clomiphene. If you’ve read older information suggesting clomiphene is still the standard, it’s worth knowing this has genuinely moved on.

What About IVF for PCOS?

Here’s something many women with PCOS don’t expect to hear: they often respond very well to IVF stimulation, since PCOS is associated with a higher number of follicles. Some studies show non-obese women with PCOS reaching cumulative IVF live birth rates around 74%, compared to roughly 62% in women without PCOS.

How PCOS Affects Pregnancy Once It Happens

This is the part that deserves equally serious attention. Research consistently shows PCOS is associated with a genuinely higher risk of several pregnancy complications:

  • Miscarriage: Often estimated at around 20–30%, roughly double the risk compared to women without PCOS
  • Gestational diabetes: Occurring in roughly 15–30% of PCOS pregnancies, also about double the typical risk
  • Gestational hypertension and preeclampsia: Consistently shown to occur more frequently in PCOS pregnancies
  • Preterm birth: Also occurring at a somewhat higher rate

This is why PCOS is generally treated as a higher-risk pregnancy category, warranting closer monitoring rather than a “wait and see” approach.

An Important Nuance: PCOS Risk vs. Fertility Treatment Risk

It’s worth separating two different questions: does having PCOS itself increase pregnancy risk, and does treating PCOS infertility with IVF add further risk on top of that? Current guidance suggests assisted reproductive technology itself doesn’t appear to meaningfully add additional miscarriage, preterm birth, or growth restriction risk beyond what’s already associated with the underlying PCOS diagnosis. In other words — the increased risk largely comes from PCOS itself, not from the treatment used to help you conceive.

Does Metformin Prevent These Complications?

This is a common assumption worth correcting. Despite metformin’s popularity in PCOS management, current evidence has not shown it prevents gestational diabetes, late miscarriage, hypertension, preeclampsia, or larger-than-average babies in pregnant women with PCOS. It may still have a role in specific situations, but it isn’t a guaranteed shield against these pregnancy complications, and shouldn’t be relied on as one.

What Can Genuinely Help Reduce These Risks?

  • Preconception weight management, where relevant, since higher BMI is independently linked to greater complication risk
  • Early and repeated screening for gestational diabetes, often starting at the first prenatal visit rather than waiting for the standard mid-pregnancy window
  • Closer blood pressure monitoring throughout pregnancy
  • Regular fetal growth monitoring
  • A coordinated care plan between your fertility specialist and obstetric team, rather than treating these as separate, disconnected phases of your journey

The Reassuring Bottom Line

Having PCOS doesn’t mean complications are inevitable — it means your pregnancy benefits genuinely from closer attention and proactive screening. Many women with PCOS go on to have healthy pregnancies and healthy babies, particularly when risks are anticipated and monitored rather than discovered late.

PCOS Pregnancy Care at Sree Swapna Fertility Centre

As one of the best fertility center in Hyderabad for comprehensive PCOS management, we approach PCOS as a condition requiring attention both before and during pregnancy — not just at the point of conception.

Dr. Swapna Naik, Clinical Director at Sree Swapna Fertility Centre, brings over 15 years of experience in reproductive medicine and has guided more than 5,000 successful pregnancies, including many women with PCOS. Our approach includes evidence-based ovulation induction using letrozole where appropriate, IVF planning tailored to PCOS-specific response patterns, and close coordination around pregnancy monitoring for gestational diabetes and hypertension risk.

Both our Kondapur and Attapur clinics offer in-house diagnostic and monitoring facilities, so your PCOS-related fertility treatment and pregnancy risk management stay properly coordinated under one experienced team.

Frequently Asked Questions

1. Does PCOS affect my chances of getting pregnant?

Yes, PCOS commonly causes irregular or absent ovulation, which is the main reason it affects fertility, though it’s often effectively treatable.

2. Is clomiphene still the first choice for PCOS ovulation induction?

No, current guidelines now recommend letrozole as the preferred first-line treatment, since research shows better ovulation and pregnancy rates compared to clomiphene.

3. Does PCOS increase miscarriage risk?

Yes, research suggests roughly double the miscarriage risk compared to women without PCOS, often estimated around 20–30%.

4. Does PCOS increase the risk of gestational diabetes?

Yes, gestational diabetes occurs in roughly 15–30% of PCOS pregnancies, about twice the typical risk.

5. Is preeclampsia more common in PCOS pregnancies?

Yes, research consistently shows a higher rate of preeclampsia and gestational hypertension in women with PCOS.

6. Does IVF add extra risk on top of PCOS itself?

Current guidance suggests assisted reproductive technology doesn’t meaningfully add additional risk beyond what’s already associated with the underlying PCOS diagnosis.

7. Does metformin prevent gestational diabetes in PCOS pregnancies?

No, current evidence hasn’t shown metformin prevents gestational diabetes or other major PCOS-related pregnancy complications.

8. Do women with PCOS respond well to IVF?

Yes, many women with PCOS respond strongly to IVF stimulation due to a higher number of follicles, with some studies showing notably high cumulative live birth rates.

9. Is PCOS considered a high-risk pregnancy?

Yes, PCOS pregnancies are generally treated as higher-risk, warranting closer monitoring for gestational diabetes, hypertension, and preterm birth.

10. Can weight management before pregnancy reduce PCOS-related risks?

Yes, preconception weight management, where relevant, is associated with reduced complication risk in PCOS pregnancies.

11. Does PCOS increase the risk of a larger-than-average baby?

Evidence on this is mixed, with some research not showing an increased risk over the general population once other factors are accounted for.

12. When should gestational diabetes screening start for women with PCOS?

Many providers recommend screening at the first prenatal visit, in addition to the standard later screening window.

13. Does PCOS increase preterm birth risk?

Yes, research shows a somewhat higher rate of preterm birth in PCOS pregnancies compared to the general population.

14. Can healthy PCOS pregnancies happen without complications?

Yes, many women with PCOS have healthy pregnancies, especially with proactive monitoring and management from early on.

15. Is letrozole safe to use for ovulation induction?

Current large trials and meta-analyses haven’t shown an increase in congenital anomalies or adverse outcomes with letrozole-induced pregnancies.

16. Should I see a specialist before trying to conceive if I have PCOS?

Yes, a preconception consultation can help address weight, ovulation induction options, and risk factors before you start trying.

17. Does PCOS affect pregnancy differently depending on severity?

Yes, factors like BMI, insulin resistance, and specific PCOS phenotype can all influence individual risk levels.

18. Can PCOS-related pregnancy risks be caught early with proper monitoring?

Yes, early and regular screening significantly improves the chances of catching and managing complications before they become serious.

19. Does having PCOS mean I’ll definitely need IVF to conceive?

No, many women with PCOS conceive with lifestyle changes and ovulation induction medication alone, without needing IVF.

20. Is blood pressure monitoring more important in PCOS pregnancies?

Yes, given the higher risk of gestational hypertension and preeclampsia, closer blood pressure monitoring is generally recommended throughout pregnancy.

21. Can PCOS affect pregnancy even if my periods are somewhat regular?

Yes, PCOS-related pregnancy risks like gestational diabetes and hypertension can still apply even with relatively regular cycles, since these relate to underlying metabolic factors.

22. Where can I find the best fertility center in Hyderabad for PCOS pregnancy planning?

Sree Swapna Fertility Centre offers comprehensive PCOS fertility and pregnancy risk management at both our Kondapur and Attapur clinics.

Conclusion

PCOS genuinely affects both your chances of conceiving and your pregnancy once it happens — but neither part of this story needs to be alarming. With current, evidence-based treatment for ovulation induction, and proactive monitoring for pregnancy-specific risks, many women with PCOS go on to have healthy pregnancies and healthy babies.

Plan Your PCOS Pregnancy Journey With Us

Dr. Swapna Naik and the team at Sree Swapna Fertility Centre — recognised as a leading, best fertility center in Hyderabad — are here to guide you through both conception and a well-monitored pregnancy.

📞 Call: +91 76708 04424 / +91 40 4995 3719 💬 WhatsApp: Message us directly 📧 Email: sreeswapna.fertility@gmail.com 📍 Visit us at: Kondapur (flagship centre) or Attapur, Hyderabad 🌐 Book an appointment: sreeswapnaivf.com/contact-us
Author: Swapna

Many couples starting IVF assume ICSI is simply the “upgraded,” more advanced version — so naturally, better. It’s a reasonable assumption, but current research tells a more specific, more useful story.

For most patients without male factor infertility, ICSI does not improve success rates — and some large studies suggest it may even slightly lower them. Here’s what the evidence actually shows, and when ICSI genuinely does make a meaningful difference.

What Is ICSI, and Why Was It Developed?

ICSI (Intracytoplasmic Sperm Injection) involves injecting a single sperm directly into an egg, rather than placing sperm and egg together and allowing fertilisation to happen naturally, as in conventional IVF.

It was developed specifically to help couples facing severe male factor infertility — very low sperm count, poor motility, or abnormal morphology — where conventional IVF’s natural fertilisation process was unlikely to succeed on its own.

What Does Current Research Actually Show?

This is where the picture becomes genuinely important to understand.

For Non-Male-Factor Infertility: No Benefit, Sometimes Slightly Worse Outcomes

A large Canadian registry study analysing over 140,000 IVF cycles found conventional IVF actually had a higher cumulative live birth rate than ICSI (38.5% vs. 36.3%) — despite ICSI being used in three-quarters of all cycles studied.

Separately, a 2025 randomised clinical trial published in Nature Medicine found ICSI does not improve cumulative live birth rates compared to conventional IVF in couples without severe male factor infertility, supporting conventional IVF as the preferred first-line approach in these cases.

A U.S. registry analysis found a similar pattern specifically in women with diminished ovarian reserve: live birth rates were actually lower with ICSI (20.4%) compared to conventional IVF (21.9%) in this group.

For Unexplained Infertility: The Evidence Is More Mixed, and Limited

One meta-analysis found a higher fertilisation rate with ICSI in couples with unexplained infertility — but with an important caveat: the failed fertilisation rate in the conventional IVF group in that analysis was notably higher than expected for a genuinely unexplained infertility population, suggesting some of those “unexplained” cases may have had an undiagnosed sperm-egg interaction issue all along. The American Society for Reproductive Medicine has explicitly stated that overall evidence for routine ICSI benefit in unexplained infertility remains limited.

So Why Is ICSI Used So Often, Even Without Male Factor Infertility?

The honest answer, according to a detailed clinical review: many clinics use ICSI to avoid the risk of total fertilisation failure — a genuinely distressing outcome for patients. But research shows this trade-off doesn’t hold up well under scrutiny: an estimated 33 couples would need to undergo unnecessary ICSI to prevent just one case of total fertilisation failure. That’s a significant amount of added cost and procedural complexity for a fairly small, avoidable risk in appropriately selected patients.

When Does ICSI Genuinely Help?

ICSI remains the right, evidence-supported choice in several specific situations:

  • Severe male factor infertility — very low sperm count, poor motility, or abnormal morphology
  • Previous total fertilisation failure with conventional IVF in an earlier cycle
  • Surgically retrieved sperm (from procedures like TESA, PESA, or TESE), since the limited sperm numbers involved make direct injection necessary
  • Certain PGT (genetic testing) cycles, in some protocols, to avoid extra sperm DNA potentially interfering with genetic analysis — though even here, recent research suggests ICSI doesn’t necessarily improve overall live birth rates compared to conventional IVF when PGT-A is used

What About Using ICSI for Frozen Sperm?

Some clinics apply ICSI by default whenever frozen (cryopreserved) sperm is used, regardless of sperm quality. Current research doesn’t support this practice either — there’s no solid evidence that frozen sperm alone is a valid reason to skip conventional IVF, if sperm parameters are otherwise normal.

Are There Any Downsides to Unnecessary ICSI?

Beyond added cost and embryology workload, there’s an important, honestly unresolved question in the research: some studies have raised concerns about a possible, modestly increased risk of certain birth defects or imprinting disorders associated with ICSI. The data here remains genuinely debated, and it isn’t clear whether this reflects the ICSI procedure itself or underlying factors related to why ICSI was needed in the first place (such as the male infertility factor itself). It’s a reasonable factor to weigh, though not something to be alarmed about — simply another reason routine, unnecessary ICSI isn’t the automatic “safer bet” it’s often assumed to be.

What This Means for Your IVF Decision

If you’re starting IVF, it’s worth directly asking your specialist: is ICSI being recommended because of a specific male factor finding, or as a routine default? Based on current evidence, conventional IVF is the preferred first-line approach for couples without a male factor indication — and ICSI should be reserved for cases where the evidence genuinely supports it.

Our Approach to ICSI at Sree Swapna Fertility Centre

Dr. Swapna Naik, Clinical Director at Sree Swapna Fertility Centre, brings over 15 years of experience and has guided more than 5,000 successful pregnancies, and our approach follows current evidence-based guidance rather than defaulting to ICSI for every cycle.

At both our Kondapur and Attapur clinics, ICSI is recommended specifically when male factor infertility, previous fertilisation failure, or surgically retrieved sperm make it the appropriate choice — not as a routine upsell. We believe an honest conversation about what the evidence actually supports serves you better than assuming “more advanced” automatically means “more effective” for your specific situation.

Frequently Asked Questions

1. Does ICSI improve IVF success rates for everyone?

No, current large studies show no improvement — and in some cases, slightly lower live birth rates — for couples without male factor infertility.

2. When was ICSI originally developed to be used?

It was developed specifically to help couples facing severe male factor infertility, where conventional IVF fertilisation was unlikely to succeed.

3. Is ICSI necessary if sperm parameters are normal?

Generally no — current evidence doesn’t support routine ICSI use when sperm parameters are within normal ranges and no other male factor indication is present.

4. Does ICSI help with unexplained infertility?

Evidence here is limited and somewhat mixed; overall research doesn’t strongly support routine ICSI benefit for unexplained infertility specifically.

5. Why do so many clinics use ICSI even without male factor infertility?

Largely to avoid the risk of total fertilisation failure, though research shows this trade-off requires treating many couples unnecessarily to prevent one such case.

6. Is ICSI ever the right choice?

Yes, for severe male factor infertility, previous fertilisation failure, and surgically retrieved sperm, ICSI remains the appropriate, evidence-supported approach.

7. Does using frozen sperm automatically require ICSI?

No, current research doesn’t support automatically using ICSI just because frozen sperm is being used, if sperm quality is otherwise normal.

8. Is ICSI more expensive than conventional IVF?

Yes, ICSI generally adds cost due to the additional procedure and embryologist time involved.

9. Are there safety concerns associated with ICSI?

Some studies have raised questions about a possible, modestly increased risk of certain birth defects or imprinting disorders, though the data remains debated and isn’t fully resolved.

10. Does ICSI help with PGT (genetic testing) cycles?

It’s used in some protocols to avoid sperm DNA interference during testing, though recent research suggests it doesn’t necessarily improve overall live birth rates compared to conventional IVF in these cycles.

11. What did the 2025 Nature Medicine study find about ICSI?

It found ICSI does not improve cumulative live birth rates compared to conventional IVF in couples without severe male factor infertility.

12. What did the Canadian registry study find?

Among over 140,000 cycles, conventional IVF had a higher cumulative live birth rate than ICSI, despite ICSI being used in the majority of cycles studied.

13. Does ICSI affect women with diminished ovarian reserve differently?

One U.S. registry analysis found live birth rates were actually lower with ICSI compared to conventional IVF in this specific group.

14. Should I ask my doctor why ICSI is being recommended?

Yes, it’s a reasonable question — ask whether it’s due to a specific male factor finding or being used as a routine default.

15. Does total fertilisation failure happen with conventional IVF?

It can, though research shows a large number of couples would need unnecessary ICSI to prevent just one such case, making routine use a questionable trade-off.

16. Is ICSI required when using surgically retrieved sperm?

Yes, since procedures like TESA or TESE typically yield very limited sperm numbers, ICSI is generally necessary in these cases.

17. What does ASRM currently recommend about ICSI use?

The ASRM’s committee opinion states that routine use of ICSI without a male factor indication is not supported by current evidence.

18. Can ICSI be added later if conventional IVF fertilisation doesn’t work?

Yes, in some clinics, “rescue ICSI” can be performed if conventional insemination shows no signs of fertilisation, though timing and protocols vary.

19. Does ICSI use vary a lot between clinics globally?

Yes, ICSI has been used far more broadly than its evidence-based indications would suggest, a pattern noted across multiple international studies.

20. Is conventional IVF less advanced than ICSI?

Not in terms of effectiveness for appropriate cases — conventional IVF is simply a different fertilisation approach, and current evidence supports it as the preferred first-line method for non-male-factor infertility.

21. Does choosing conventional IVF over ICSI reduce my chances unnecessarily?

Based on current evidence, no — for couples without male factor infertility, conventional IVF is generally associated with equal or better outcomes than ICSI.

22. Where can I get an honest, evidence-based recommendation on ICSI vs conventional IVF in Hyderabad?

Sree Swapna Fertility Centre bases ICSI recommendations on current clinical evidence and your specific diagnosis at both our Kondapur and Attapur clinics.

Conclusion

ICSI is a genuinely valuable tool — for the specific situations it was designed for. But current, robust research is clear that it isn’t automatically “better” than conventional IVF, and for many couples without male factor infertility, it offers no advantage and, in some studies, a slightly lower success rate. The most useful question to ask your specialist isn’t “should I get the more advanced option,” but “does the evidence actually support ICSI for my specific situation?”

Get an Evidence-Based IVF Recommendation

Dr. Swapna Naik and the team at Sree Swapna Fertility Centre will recommend ICSI only when your specific diagnosis genuinely supports it.

📞 Call: +91 76708 04424 / +91 40 4995 3719 💬 WhatsApp: Message us directly 📧 Email: sreeswapna.fertility@gmail.com 📍 Visit us at: Kondapur (flagship centre) or Attapur, Hyderabad 🌐 Book an appointment: sreeswapnaivf.com/contact-us

Author: Swapna

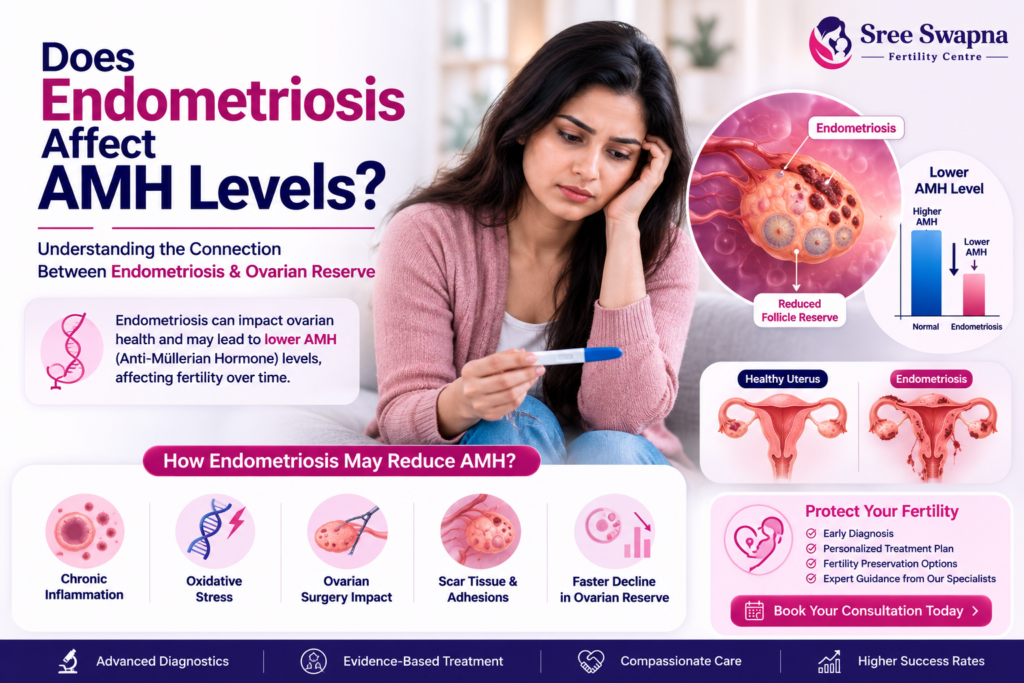
If you have endometriosis — particularly an ovarian endometrioma (chocolate cyst) — and you’ve had your AMH tested, you might be looking at a number lower than expected for your age. This is a genuinely well-documented pattern, and understanding why can help you make more informed decisions about treatment timing.

Yes, Endometriosis Is Linked to Lower AMH — Even Before Surgery

Multiple studies have found that women with ovarian endometriomas have measurably lower AMH levels compared to women of similar age without the condition. One notable study tracking AMH over six months found it declined by a median of 26.4% in women with untreated endometriomas, compared to just 7.4% in women without the condition — suggesting the endometrioma itself accelerates the natural decline in ovarian reserve, independent of any surgery.

This appears to happen through a combination of local inflammation, oxidative stress, and gradual damage to the surrounding healthy ovarian tissue that houses your egg-containing follicles.

Then Surgery Adds Another Layer

This is the part that surprises many patients: cystectomy (surgical removal of an endometrioma) typically causes an additional, often substantial drop in AMH — on top of whatever decline the endometrioma itself has already caused.

Research findings vary somewhat by study, but the pattern is consistent:

  • Unilateral cystectomy: Roughly a 30% additional decline in AMH is commonly reported
  • Bilateral cystectomy: Declines of up to 44% or more have been reported, with some studies showing even steeper initial drops that partially recover over the following months

One study following patients for a full year found AMH declining from a median of 3.77 ng/mL before surgery to around 1.60–1.72 ng/mL afterward — a sustained decline of over 40%, even a year later.

Why Does Surgery Cause This?

It’s not because surgeons are careless — it’s an unavoidable trade-off of the procedure itself:

  • Removing the cyst wall inevitably takes some healthy ovarian cortex with it, since endometrioma tissue is often intimately attached to surrounding normal tissue
  • Thermal coagulation (cautery) used to control bleeding during surgery can damage nearby healthy follicles
  • Disrupted blood supply, particularly when the mesosalpinx (tissue connecting the ovary to the fallopian tube) is involved or adhesions need to be released, can further affect ovarian tissue health

What Makes the Decline Worse?

Research has identified several factors associated with a steeper AMH drop after surgery:

  • Bilateral endometriomas (both ovaries affected) consistently show a larger decline than unilateral cases
  • Larger cyst size — declines are notably steeper for cysts over 7cm
  • Lower AMH levels before surgery — women who already have reduced ovarian reserve tend to see a larger proportional impact
  • Involved mesosalpinx or significant adhesions, which can compromise the ovary’s blood supply during and after surgery

Does Surgical Technique Make a Difference?

Yes, genuinely. Research comparing different surgical approaches has found:

  • Cystectomy (complete excision) has the lowest recurrence rate, but causes the greatest AMH decline
  • Ablation (vaporisation) of the cyst lining tends to preserve more ovarian reserve, but is associated with a higher recurrence rate
  • Combined techniques (partial cystectomy plus ablation of the remaining cyst wall) have shown a middle-ground effect — less AMH decline than full cystectomy, without the recurrence rates seen with ablation alone

This is a genuine trade-off, not an easy choice, and it’s worth discussing directly with your surgeon: are you prioritising the lowest recurrence risk, or preserving as much ovarian reserve as possible? The right answer depends on your age, fertility timeline, and how symptomatic the cyst is.

Can AMH Recover After Surgery?

Some studies show partial recovery over the following months, particularly in women with intact blood supply to the ovary and smaller, unilateral cysts. However, in many cases — particularly bilateral surgery, larger cysts, or when the mesosalpinx was involved — the decline tends to persist rather than fully reverse.

What This Means for Your Fertility Planning

If you have an endometrioma and are considering both your symptoms and future fertility, this research points to a few practical takeaways:

  • Surgery isn’t automatically the first or only option — if the cyst is small, causing minimal symptoms, and you’re not in urgent need of treatment, monitoring or hormonal management may be reasonable, particularly if preserving ovarian reserve is a priority
  • If surgery is needed, discuss technique with your surgeon — cystectomy, ablation, or a combined approach each carry different trade-offs
  • If fertility is a near-term goal, some specialists may discuss egg freezing before surgery, particularly for bilateral endometriomas or larger cysts, to preserve options regardless of how surgery affects your ovarian reserve afterward

Endometriosis and AMH Care at Sree Swapna Fertility Centre

Dr. Swapna Naik, Clinical Director at Sree Swapna Fertility Centre, is a trained laparoscopic surgeon with over 15 years of experience, and factors ovarian reserve preservation directly into surgical planning for endometriomas — not treating every cyst with the same default technique.

Both our Kondapur and Attapur clinics offer AMH testing and detailed ultrasound evaluation, allowing us to have an honest, informed conversation about your specific situation — cyst size, laterality, symptoms, and fertility timeline — before recommending a surgical approach, or discussing whether surgery is the right next step at all.

Frequently Asked Questions

1. Does having an endometrioma lower AMH even without surgery?

Yes, research shows AMH tends to decline faster in women with untreated endometriomas compared to women without the condition.

2. How much does cystectomy typically lower AMH?

Studies commonly report roughly a 30% additional decline after unilateral cystectomy, and up to 44% or more after bilateral cystectomy.

3. Why does removing an endometrioma affect healthy ovarian tissue?

The cyst wall is often closely attached to surrounding healthy tissue, so some normal ovarian cortex containing follicles is inevitably removed or affected during surgery.

4. Does AMH recover after endometrioma surgery?

Some recovery is possible, particularly with smaller, unilateral cysts and intact blood supply, but the decline often persists, especially after bilateral surgery.

5. Is bilateral endometrioma surgery worse for ovarian reserve than unilateral?

Yes, bilateral cystectomy is consistently associated with a larger AMH decline than unilateral surgery in research studies.

6. Does cyst size affect how much AMH drops after surgery?

Yes, larger cysts, particularly over 7cm, are associated with a steeper decline in AMH after surgery.

7. Is ablation better than cystectomy for preserving ovarian reserve?

Ablation is generally associated with less AMH decline than cystectomy, but comes with a higher risk of cyst recurrence — a genuine trade-off to discuss with your surgeon.

8. What is a combined surgical technique for endometriomas?

It involves partial cystectomy along with ablation of the remaining cyst wall, aiming to balance lower recurrence risk with less impact on ovarian reserve.

9. Should I get my AMH tested before endometrioma surgery?

Yes, baseline AMH testing can help inform surgical planning and give you and your doctor a clearer picture of your starting ovarian reserve.

10. Does every woman with endometriosis have low AMH?

Not necessarily — the association is more consistently shown with ovarian endometriomas specifically, rather than all forms or severities of endometriosis.

11. Can I avoid surgery to protect my ovarian reserve?

In some cases, if the cyst is small and symptoms are manageable, monitoring or hormonal treatment may be a reasonable alternative to surgery — this is worth discussing with your specialist.

12. Does the surgeon’s experience affect how much AMH declines after surgery?

Surgical technique and care in preserving healthy tissue can influence outcomes, so experience with endometrioma-specific surgery is a reasonable factor to consider.

13. Should I consider egg freezing before endometrioma surgery?

This is worth discussing with your specialist, particularly for bilateral endometriomas, larger cysts, or if you’re not planning pregnancy in the near term but want to preserve options.

14. Does a lower AMH after surgery mean I can’t get pregnant?

No, AMH reflects ovarian reserve (egg quantity), not a guarantee of infertility — many women with lower AMH after surgery still conceive naturally or with fertility treatment.

15. How soon after surgery should AMH be retested?

This varies by clinical protocol, but testing at intervals like 1, 3, 6, and 12 months has been used in research to track recovery patterns.

16. Does having a smaller endometrioma mean surgery will have less impact on AMH?

Generally, smaller cysts are associated with a less significant AMH decline compared to larger ones, though individual factors still matter.

17. Can adhesions affect AMH decline after surgery?

Yes, involvement of the mesosalpinx or significant adhesions, which can affect the ovary’s blood supply, has been linked to a greater and more persistent AMH decline.

18. Is AMH the only factor in deciding on endometrioma surgery?

No, symptoms, cyst size, risk of malignancy, and personal fertility goals all factor into this decision alongside AMH considerations.

19. Does repeat endometrioma surgery cause more ovarian reserve damage?

Yes, repeated surgery on the same ovary is generally associated with a cumulative additional impact on ovarian reserve, which is an important consideration for recurrent cases.

20. Can hormonal treatment help avoid the need for repeat surgery?

In some cases, postoperative hormonal treatment may help reduce recurrence risk, potentially avoiding the need for repeat surgery and its additional impact on ovarian reserve.

21. Should I discuss surgical technique options with my surgeon beforehand?

Yes, it’s a reasonable and important conversation — ask about cystectomy versus ablation versus combined techniques and how each might apply to your specific case.

22. Where can I get AMH testing and endometrioma evaluation in Hyderabad?

Sree Swapna Fertility Centre offers AMH testing and detailed ultrasound evaluation for endometriomas at both our Kondapur and Attapur clinics.

Conclusion

Endometriosis, and particularly ovarian endometriomas, genuinely can lower AMH — both from the condition itself and, further, from the surgery often used to treat it. This isn’t a reason to avoid necessary treatment, but it is a reason to have an honest, detailed conversation with your specialist about surgical technique, timing, and whether fertility preservation should be part of your plan.

Discuss Your Ovarian Reserve and Treatment Options

Dr. Swapna Naik and the team at Sree Swapna Fertility Centre can help you weigh symptom relief against ovarian reserve preservation for your specific situation.

📞 Call: +91 76708 04424 / +91 40 4995 3719 💬 WhatsApp: Message us directly 📧 Email: sreeswapna.fertility@gmail.com 📍 Visit us at: Kondapur (flagship centre) or Attapur, Hyderabad 🌐 Book an appointment: sreeswapnaivf.com/contact-us
Author: Swapna

If you or someone you love has just heard the words “endometrial cancer,” the first question is almost always the same: how fast is this moving?

The honest, direct answer: it depends — on the type of endometrial cancer, its grade, and increasingly, its molecular profile. This isn’t a dodge; it’s genuinely the most accurate answer current medicine can give. Let’s break down what actually determines the answer for a specific diagnosis.

The Reassuring Part First

Endometrial cancer is one of the more frequently caught-early cancers, largely because it tends to announce itself. Abnormal bleeding — especially bleeding after menopause — is the most common early symptom, and it typically prompts women to see a doctor relatively quickly. Because of this, a large majority of endometrial cancer cases are diagnosed at an early stage, when the disease is still confined to the uterus.

Early-stage, low-grade endometrioid endometrial cancer (the most common type) is generally considered a comparatively slower-growing cancer, and outcomes at this stage are often favourable, with published survival rates in the high 80s to high 90s percentage range at 3 and 5 years for early-stage, lower-grade disease.

But Not All Endometrial Cancer Behaves the Same Way

This is where “it depends” becomes genuinely important, not just a hedge.

Type and Grade Matter

  • Low-grade, endometrioid tumours (the most common type) tend to grow and spread more slowly
  • High-grade, aggressive histological subtypes — including serous carcinoma, clear cell carcinoma, and carcinosarcoma — behave much more aggressively, and can spread more quickly, even when caught at a similar stage

Molecular Classification Now Changes the Picture Significantly

Since 2023, the official staging system for endometrial cancer has started incorporating molecular subtyping — genetic characteristics of the tumour — because it turns out to predict behaviour more precisely than the older, purely anatomical staging system:

  • POLE-mutated tumours carry an excellent prognosis — close to 100% survival in some studies, even when found at a more advanced stage
  • p53-abnormal tumours carry the least favourable prognosis among the molecular subtypes, and are associated with more aggressive behaviour
  • Mismatch repair-deficient (MMRd) and “no specific molecular profile” (NSMP) tumours generally fall in between

This is a genuinely significant shift: two women with the “same stage” diagnosis under older classification systems can now be understood to have meaningfully different outlooks, once their tumour’s molecular profile is known.

How Does Endometrial Cancer Actually Spread?

When it does spread, endometrial cancer typically follows a fairly predictable path:

  1. Direct extension — growing deeper into the muscular wall of the uterus (myometrium), and potentially into the cervix
  2. Lymphatic spread — travelling to nearby lymph nodes in the pelvis, and later, nodes near the aorta
  3. Peritoneal spread — in some cases, particularly aggressive types, spreading across the lining of the abdominal cavity
  4. Distant spread — in more advanced disease, reaching further organs such as the lungs, liver, or bone

The depth of invasion into the myometrium, and the presence of cancer cells within lymphatic or blood vessels (called lymphovascular space invasion, or LVSI), are both important factors your pathology report will note, since they influence both staging and prognosis.

Why Early Symptoms Matter So Much Here

Because abnormal uterine bleeding — particularly any bleeding after menopause — is often the very first sign, taking it seriously and getting it evaluated promptly is one of the most meaningful things a woman can do for her own outcome. This isn’t about causing alarm over every irregular period; it’s about not dismissing a genuinely important warning sign, especially postmenopausally, when any bleeding is considered abnormal until proven otherwise.

What Determines Your Actual Prognosis

If you or a loved one has received a diagnosis, prognosis is generally shaped by:

  • Stage at diagnosis (how far it has spread)
  • Grade (how abnormal the cells look, and how quickly they’re likely to grow)
  • Histological subtype (endometrioid vs. more aggressive types like serous or clear cell)
  • Molecular subtype, where available
  • Lymphovascular space invasion, noted on pathology review
  • Depth of myometrial invasion

A gynaecologic oncologist will interpret all of these factors together to determine both staging and the recommended treatment plan.

Where This Fits Into Our Care

We want to be transparent about our role here. Diagnosis, staging surgery, and treatment (including chemotherapy and radiation) for confirmed endometrial cancer require a gynaecologic oncologist and a specialised cancer care team — this is standard, appropriate care, not a referral we make reluctantly.

What general gynaecology, including our practice, contributes is often the first step: recognising abnormal bleeding as a symptom worth investigating, performing initial evaluation through transvaginal ultrasound (checking endometrial thickness) and endometrial biopsy, and coordinating a prompt referral to gynaecologic oncology when findings raise concern.

Endometrial Health Evaluation at Sree Swapna Fertility Centre

Dr. Swapna Naik, Clinical Director at Sree Swapna Fertility Centre, brings over 15 years of experience in gynaecology, and takes abnormal uterine bleeding seriously as a symptom warranting prompt evaluation — particularly in postmenopausal women, or in the presence of known risk factors like obesity, PCOS, or a family history of Lynch syndrome.

Both our Kondapur and Attapur clinics offer in-house transvaginal ultrasound and endometrial biopsy, allowing timely initial evaluation, with rapid referral coordination to gynaecologic oncology whenever findings suggest malignancy.

Frequently Asked Questions

1. Does endometrial cancer spread quickly?

It depends on the type, grade, and molecular subtype — low-grade endometrioid tumours tend to grow more slowly, while aggressive histological or molecular subtypes can spread more quickly.

2. What is the most common early symptom of endometrial cancer?

Abnormal uterine bleeding, especially bleeding after menopause, is the most common early symptom.

3. Is endometrial cancer usually caught early?

Yes, a large majority of cases are diagnosed at an early stage, largely because abnormal bleeding prompts relatively quick evaluation.

4. What does “molecular subtype” mean for endometrial cancer prognosis?

It refers to specific genetic characteristics of the tumour that have been shown to predict behaviour and outcomes more precisely than older staging methods alone.

5. Which molecular subtype has the best prognosis?

POLE-mutated tumours generally carry an excellent prognosis, even at more advanced stages.

6. Which molecular subtype has the worst prognosis?

p53-abnormal tumours are generally associated with the least favourable prognosis among the molecular subtypes.

7. How does endometrial cancer typically spread if untreated?

It can extend directly into the uterine muscle wall and cervix, spread through lymphatic channels to nearby lymph nodes, and in more advanced cases, reach distant organs.

8. What is lymphovascular space invasion (LVSI)?

It refers to cancer cells found within lymphatic or blood vessels on pathology review, an important factor in staging and prognosis.

9. Does Sree Swapna Fertility Centre treat endometrial cancer directly?

No, diagnosis confirmation and treatment require a gynaecologic oncologist. We provide initial evaluation, including ultrasound and biopsy, and coordinate referral when needed.

10. What are the risk factors for endometrial cancer?

Risk factors include obesity, PCOS, unopposed oestrogen exposure, diabetes, and a family history of Lynch syndrome, among others.

11. Is postmenopausal bleeding always a sign of cancer?

No, but it’s considered abnormal until proven otherwise and should always be evaluated promptly by a doctor.

12. How is endometrial cancer initially diagnosed?

Typically through transvaginal ultrasound to assess endometrial thickness, followed by an endometrial biopsy if findings raise concern.

13. What is the difference between endometrioid and non-endometrioid endometrial cancer?

Endometrioid is the more common, generally slower-growing type, while non-endometrioid subtypes like serous or clear cell carcinoma tend to behave more aggressively.

14. Can endometrial cancer be treated while preserving the uterus?

In very select, early-stage, low-grade cases in women who strongly wish to preserve fertility, this may be discussed with a gynaecologic oncologist, though it’s not appropriate for every case.

15. Does grade affect how quickly endometrial cancer spreads?

Yes, higher-grade tumours generally show more aggressive behaviour and a greater tendency to spread compared to lower-grade tumours.

16. What changed in the 2023 FIGO staging update for endometrial cancer?

It incorporated molecular classification alongside traditional anatomical staging, improving the accuracy of prognosis prediction.

17. Is endometrial cancer more common in postmenopausal women?

Yes, it’s more frequently diagnosed in postmenopausal women, though it can occur in younger women as well.

18. Can endometrial cancer spread to the ovaries?

Yes, in some cases, particularly with more advanced or aggressive disease, spread to the ovaries can occur.

19. What survival rates are associated with early-stage endometrial cancer?

Published studies report survival rates in the high 80s to high 90s percentage range at 3 and 5 years for early-stage, lower-grade endometrioid disease, though individual outcomes vary.

20. Should every case of abnormal bleeding be evaluated for endometrial cancer?

Any abnormal or postmenopausal bleeding should be evaluated by a doctor, though most cases have benign causes — evaluation is about ruling out serious causes, not assuming the worst.

21. Can family history affect endometrial cancer risk?

Yes, a family history of Lynch syndrome significantly increases endometrial cancer risk and may warrant additional screening discussions with your doctor.

22. Where can I get initial evaluation for abnormal uterine bleeding in Hyderabad?

Sree Swapna Fertility Centre offers transvaginal ultrasound and endometrial biopsy evaluation at both our Kondapur and Attapur clinics, with prompt referral to gynaecologic oncology when needed.

Conclusion

Whether endometrial cancer spreads quickly genuinely depends on its type, grade, and increasingly, its molecular profile — not a single universal answer. What matters most practically is taking abnormal bleeding seriously and getting it evaluated promptly, since early detection remains one of the most meaningful factors in a favourable outcome.

Concerned About Abnormal Bleeding?

Dr. Swapna Naik and the team at Sree Swapna Fertility Centre can provide prompt evaluation and coordinate specialist care when needed.

📞 Call: +91 76708 04424 / +91 40 4995 3719 💬 WhatsApp: Message us directly 📧 Email: sreeswapna.fertility@gmail.com 📍 Visit us at: Kondapur (flagship centre) or Attapur, Hyderabad 🌐 Book an appointment: sreeswapnaivf.com/contact-us

Author: Swapna

Here’s a question most men are too embarrassed to ask out loud, but think about constantly before sperm retrieval surgery: “Will this change me? Down there, and everywhere else?”

It’s a completely fair thing to wonder. Someone’s about to put a needle, or a small instrument, into one of the most sensitive parts of your body. Of course you want to know what happens next — not just for your fertility, but for your sex life.

Here’s the twist: the real answer isn’t really about the surgery at all. It’s about something researchers didn’t expect to find.

The Surprising Study Everyone Should Know About

A group of researchers followed 66 men with non-obstructive azoospermia through TESE (testicular sperm extraction), then checked back in six months later. They measured erectile function using a standard clinical scale, and split the men into two groups: those where sperm was successfully found, and those where it wasn’t.

Here’s what they found. Men whose sperm retrieval succeeded actually showed a slight improvement in erectile function scores afterward. But men whose retrieval failed showed a real decline — and it wasn’t just in their heads, or entirely in their heads, depending on how you look at it. Their FSH and LH hormone levels rose, testosterone dropped, and — critically — this same group scored notably higher on anxiety and depression measures.

Read that again: the surgery itself, for most men, wasn’t the problem. The emotional weight of the outcome was.

So What Does This Actually Mean for You?

It means the story you’ve probably been telling yourself — “the procedure is going to damage something” — likely isn’t the most useful thing to worry about. The nerves responsible for erections travel through a completely different pathway than the tissue being sampled during these procedures. A needle in the epididymis or a small testicular biopsy doesn’t sever the wiring for your sex life.

What genuinely affects how men feel afterward is a mix of:

  • The emotional charge of the result — finding sperm, or not
  • Hormonal shifts, particularly with more extensive procedures
  • Anxiety and depression, which often show up quietly before anyone names them out loud

Does the Type of Procedure Matter?

Yes, somewhat. Not all sperm retrieval procedures are created equal:

PESA (Percutaneous Epididymal Sperm Aspiration)

A needle draws sperm from the epididymis — a structure separate from the testicle itself. This is the least invasive option, and testosterone-producing tissue is essentially untouched.

TESA (Testicular Sperm Aspiration)

A needle samples testicular tissue directly, but in small amounts. Minor, temporary hormonal fluctuation is possible, though most men see no lasting change.

TESE and Micro-TESE

These involve a small surgical biopsy of testicular tissue, and — in the case of micro-TESE, which searches more extensively for sperm-producing areas — can cause more noticeable, though usually temporary, disruption to testosterone production. This is the procedure most closely linked to the hormonal changes seen in the research above.

The pattern here makes sense: the more tissue involved, the more your hormonal system might notice — but “notice” usually means “temporarily adjust,” not “permanently change.”

What About the Physical Recovery Itself?

Let’s talk about the part everyone actually wants to know: what happens to your sex life in the days and weeks right after surgery.

  • Mild swelling, bruising, or tenderness in the treated area is common for several days
  • Abstaining from sexual activity for about 1–2 weeks is typically recommended, mainly to allow proper healing and reduce infection risk — not because of any lasting damage
  • Testosterone, in the majority of cases, returns to baseline over the following weeks to months, even after more extensive procedures
  • Erectile function, for most men, remains completely intact once initial healing is complete

The Part Nobody Talks About: Talking to Your Partner

If there’s one thing this research quietly points to, it’s this: the emotional experience of infertility treatment is a shared one, even when the procedure itself only happens to one partner’s body. Anxiety doesn’t stay contained to “his side” of the relationship — it shapes both partners’ experience of intimacy during this time.

Talking openly, before and after the procedure, about how you’re both feeling — not just about the physical recovery, but the emotional weight of waiting for results — tends to matter more for your relationship and your sex life than the surgery itself ever will.

What If You’re Struggling Emotionally After a Failed Retrieval?

If sperm wasn’t found and you’re noticing changes in mood, confidence, or intimacy afterward, that’s a real, recognised response — not a sign of weakness, and not something you have to quietly manage alone. Speaking with your fertility specialist about this, and being open to additional support if needed, is a legitimate and important part of your care.

Sperm Retrieval Care at Sree Swapna Fertility Centre

Dr. Swapna Naik, Clinical Director at Sree Swapna Fertility Centre, brings over 15 years of experience in reproductive medicine, and our approach to sperm retrieval procedures includes honest, upfront conversations about what to expect — physically and emotionally — not just the mechanics of the procedure itself.

Both our Kondapur and Attapur clinics offer PESA, TESA, and related sperm retrieval techniques, with our team supporting you through the full experience, including what comes after the result — whatever that result turns out to be.

Frequently Asked Questions

1. Does sperm retrieval surgery cause erectile dysfunction?

Not typically due to physical damage — research shows successful retrieval is associated with stable or even slightly improved erectile function, while failed retrieval is more closely linked to emotional and hormonal factors.

2. Which sperm retrieval procedure has the least impact on hormones?

PESA generally has the least hormonal impact, since it doesn’t sample testicular tissue directly, unlike TESA, TESE, or micro-TESE.

3. Can micro-TESE affect testosterone levels?

Yes, it can cause more noticeable, usually temporary, hormonal fluctuation compared to less invasive procedures, since it involves more extensive testicular tissue sampling.

4. How long should I abstain from sex after sperm retrieval surgery?

Typically around 1–2 weeks, mainly to allow proper healing, though your specific timeline should be confirmed with your surgeon.

5. Does the nerve pathway for erections get affected during these procedures?

No, the nerves responsible for erectile function travel through a different pathway than the tissue sampled during sperm retrieval procedures.

6. Is it normal to feel anxious before and after sperm retrieval surgery?

Yes, this is a genuinely common and recognised experience, and it’s worth discussing openly with your care team rather than managing alone.

7. Why did men with failed sperm retrieval show worse erectile function in research?

The study found this was linked to both hormonal changes and notably higher anxiety and depression scores in that group, rather than physical damage from the procedure.

8. Does testosterone return to normal after TESE or micro-TESE?

In most cases, yes, testosterone levels recover over the following weeks to months, though this varies by individual and procedure extent.

9. Can PESA affect fertility treatment differently than TESA?

Both are used to retrieve sperm for ICSI, with the choice depending on whether azoospermia is obstructive or non-obstructive, rather than one being generally superior.

10. Should my partner be involved in conversations about this procedure?

Yes, since the emotional experience affects both partners, open communication tends to support both the relationship and individual wellbeing during this process.

11. Is swelling or bruising after the procedure normal?

Yes, mild swelling, bruising, or tenderness in the treated area is common and typically resolves within a week or two.

12. Can hormonal changes after surgery affect mood?

Yes, hormonal fluctuations, particularly after more extensive procedures, can contribute to mood changes alongside the emotional weight of the process itself.

13. Does a successful sperm retrieval mean better sexual function afterward?

Research found a slight improvement in erectile function scores among men with successful retrieval, likely reflecting reduced anxiety alongside stable hormonal status.

14. Is it common for men to avoid talking about these concerns with their doctor?

Yes, very common — but doctors experienced in fertility care expect and welcome these questions, so it’s worth raising them directly.

15. Can anxiety alone lower erectile function scores, separate from any physical cause?

Yes, anxiety and depression are well-recognised contributors to erectile function difficulties, independent of any physical or hormonal cause.

16. Does age affect recovery after sperm retrieval surgery?

Recovery time can vary somewhat by individual health and age, though the general recovery pattern remains similar across most adult age groups.

17. Is professional emotional support available for men going through this process?

Yes, and it’s a reasonable, valuable option if you’re struggling with mood, confidence, or intimacy concerns during or after treatment.

18. Can sperm retrieval surgery be repeated if needed?

Yes, in some cases, repeat procedures are possible, and your specialist can discuss this based on your specific situation and prior results.

19. Does the type of azoospermia (obstructive vs non-obstructive) affect which procedure is used?

Yes, obstructive azoospermia typically uses PESA or TESA, while non-obstructive azoospermia more often requires TESE or micro-TESE.

20. How soon can I expect physical healing after these procedures?

Most men experience meaningful improvement in physical discomfort within about a week, though full healing timelines vary by procedure and individual.

21. Should couples expect changes to their relationship during this process?

Some emotional strain is common during fertility treatment generally, and being aware of this in advance can help couples navigate it together more supportively.

22. Where can I get sperm retrieval procedures with supportive, honest guidance in Hyderabad?

Sree Swapna Fertility Centre offers PESA, TESA, and related procedures at both our Kondapur and Attapur clinics, with open conversations about what to expect throughout.

Conclusion

The needle isn’t the villain here. What actually shapes how men feel about their sex life after sperm retrieval surgery is a far more human story — hope, waiting, hormones doing their quiet background work, and the simple relief or disappointment of a result. Understanding that can take some of the fear out of the process, and make space for the conversations that actually matter.

Talk to Us Before Your Procedure

Dr. Swapna Naik and the team at Sree Swapna Fertility Centre are here to walk you through what to genuinely expect — physically and emotionally.

📞 Call: +91 76708 04424 / +91 40 4995 3719 💬 WhatsApp: Message us directly 📧 Email: sreeswapna.fertility@gmail.com 📍 Visit us at: Kondapur (flagship centre) or Attapur, Hyderabad 🌐 Book an appointment: sreeswapnaivf.com/contact-us

Author: Swapna

Chest pain or a collapsed lung might be the last thing you’d connect to your menstrual cycle — but for a small number of women, that’s exactly what’s happening. Diaphragmatic (thoracic) endometriosis is a rare but genuinely important condition to recognise, since it’s frequently missed for years.

This guide explains what it is, how it presents, and — importantly — how care is coordinated between gynaecology and thoracic surgery, since treating this condition properly requires both.

What Is Diaphragmatic or Thoracic Endometriosis?

Thoracic endometriosis occurs when endometrial-like tissue implants on the diaphragm, pleura (the lining around the lungs), or occasionally within the lung tissue itself. Like endometriosis elsewhere in the body, this tissue responds to your monthly hormonal cycle — which is exactly why symptoms tend to appear in a clear, cyclical pattern.

Collectively, the range of symptoms this can cause is referred to as Thoracic Endometriosis Syndrome (TES).

What Symptoms Does It Cause?

  • Catamenial pneumothorax — a collapsed lung occurring within about 72 hours of your period starting; this is the most common presentation, accounting for roughly 73% of reported cases
  • Catamenial haemothorax — bleeding into the space around the lung, tied to your cycle
  • Catamenial haemoptysis — coughing up blood, occurring cyclically
  • Pulmonary nodules — endometriosis deposits within lung tissue itself
  • Cyclical chest pain, sometimes without any of the above complications

A striking pattern in this condition: around 90–95% of cases occur on the right side of the chest — a detail that’s helped researchers understand more about how this condition develops, though a fully agreed explanation still doesn’t exist.

Who Should Suspect This Condition?

Thoracic endometriosis should be genuinely suspected in a woman of reproductive age who experiences recurrent, right-sided chest pain or a pneumothorax that consistently occurs around the time of her period. This pattern is the single most important clue, and it’s frequently the detail that gets missed in a general emergency or pulmonology setting if the connection to menstruation isn’t specifically asked about.

How Is It Diagnosed?

  • CT or MRI imaging: Can sometimes show diaphragmatic defects or suspicious findings, though imaging alone has real limitations and can miss subtle lesions
  • Video-Assisted Thoracic Surgery (VATS): Considered the gold standard for both diagnosis and treatment — it allows direct visualisation of the diaphragm and pleura, along with tissue biopsy for definitive histological confirmation

Because thoracic endometriosis is rare and its symptoms overlap with other lung conditions, diagnostic delay is common — which is exactly why recognising the cyclical pattern matters so much.

How Is Diaphragmatic Endometriosis Treated?

This is genuinely a two-part treatment process, involving both thoracic surgery and gynaecological hormonal management.

Surgical Treatment (Thoracic Surgery)

VATS allows a thoracic surgeon to directly address the problem:

  • Resection of diaphragmatic lesions or fenestrations (small holes or defects)
  • Pleurodesis — a procedure that helps the lung stick to the chest wall, reducing the chance of another pneumothorax
  • Diaphragm repair, sometimes requiring mesh reinforcement for larger defects

Hormonal Treatment (Gynaecological Management)

After surgery, hormonal therapy — typically GnRH agonists or progestins — is generally recommended to suppress ovarian hormone production and reduce the risk of recurrence. Research suggests hormonal therapy alone, without surgery, is associated with a significant recurrence rate, which is why the combined approach — surgery plus ongoing hormonal management — is generally considered the more effective path.

Why This Requires a Coordinated, Multidisciplinary Approach

We want to be transparent about this: the surgical component of thoracic endometriosis treatment (VATS) requires a thoracic surgeon, not a gynaecologist. This isn’t a limitation we work around quietly — it’s simply the appropriate standard of care, recognised by leading gynaecological endoscopy societies who have specifically called for better awareness and coordinated management of this condition.

What gynaecology contributes is recognising the pattern, coordinating the hormonal treatment before and after thoracic surgery, and managing any associated pelvic endometriosis at the same time — since thoracic endometriosis is associated with pelvic endometriosis in a substantial proportion of cases.

Diaphragmatic Endometriosis Care at Sree Swapna Fertility Centre

If your history suggests thoracic endometriosis — recurrent, cycle-linked chest symptoms — Dr. Swapna Naik, Clinical Director at Sree Swapna Fertility Centre, brings over 15 years of experience in gynaecology and endometriosis management, and can help recognise this pattern, evaluate for associated pelvic endometriosis, and coordinate a referral to an appropriate thoracic surgery team.

Following any thoracic surgical treatment, we can manage the ongoing hormonal suppression therapy and monitor for pelvic endometriosis, ensuring both sides of your treatment are properly coordinated rather than managed in isolation.

Frequently Asked Questions

1. What is diaphragmatic or thoracic endometriosis?

It’s a rare condition where endometrial-like tissue implants on the diaphragm, pleura, or lung tissue, causing symptoms that follow your menstrual cycle.

2. What is catamenial pneumothorax?

A collapsed lung occurring within about 72 hours of your period starting, and the most common presentation of thoracic endometriosis.

3. Why does thoracic endometriosis mostly affect the right side?

Around 90–95% of cases occur on the right side, though a fully agreed explanation for this pattern doesn’t yet exist in the medical literature.

4. Who should suspect this condition?

Women of reproductive age with recurrent, right-sided chest pain or pneumothorax that consistently coincides with their period.

5. How is thoracic endometriosis diagnosed?

CT or MRI imaging can suggest it, but VATS (Video-Assisted Thoracic Surgery) is the gold standard for definitive diagnosis through direct visualisation and biopsy.

6. Does Sree Swapna Fertility Centre perform the thoracic surgery for this condition?

No, the surgical component requires a thoracic surgeon. We help recognise the condition, coordinate referral, and manage hormonal treatment and any associated pelvic endometriosis.

7. What is pleurodesis?

A procedure performed during thoracic surgery that helps the lung adhere to the chest wall, reducing the risk of another pneumothorax.

8. Is hormonal treatment alone enough for thoracic endometriosis?

Research suggests hormonal treatment alone is associated with a significant recurrence rate, which is why combined surgical and hormonal treatment is generally preferred.

9. What hormonal treatments are used after thoracic surgery?

GnRH agonists or progestins are commonly used, with no clear evidence that one is definitively superior to the other.

10. Is thoracic endometriosis linked to pelvic endometriosis?

Yes, it’s associated with pelvic endometriosis in a substantial proportion of cases, which is why gynaecological evaluation matters alongside thoracic treatment.

11. How common is thoracic endometriosis?

It’s considered rare, and awareness of the condition has historically been limited, contributing to diagnostic delays.

12. Can thoracic endometriosis cause coughing up blood?

Yes, catamenial haemoptysis (cyclical coughing up blood) is one recognised presentation, though less common than pneumothorax.

13. Can imaging alone rule out thoracic endometriosis?

Not reliably — imaging has real limitations in detecting subtle lesions, which is why VATS remains the diagnostic gold standard when this condition is suspected.

14. What should I do if I have recurrent chest pain tied to my period?

Raise this specific cyclical pattern with your doctor, and ask about evaluation for thoracic endometriosis, since this connection is easy to miss without specifically asking about it.

15. Can thoracic endometriosis come back after surgery?

Yes, recurrence is possible, which is why postoperative hormonal therapy is generally recommended to reduce this risk.

16. Is thoracic endometriosis a life-threatening condition?

A pneumothorax can be a serious, acute medical event requiring prompt treatment, though with appropriate diagnosis and coordinated care, it’s manageable long-term.

17. What society has raised awareness about this condition?

The British Society for Gynaecological Endoscopy, along with the Royal College of Obstetricians and Gynaecologists, has released statements aimed at improving awareness and standardising care for this condition.

18. Does thoracic endometriosis affect fertility?

As a form of endometriosis, it may be associated with pelvic disease that can affect fertility, though this varies by individual case.

19. Can diaphragmatic hernia be related to endometriosis?

Yes, endometriosis-related diaphragmatic hernia is one of the recognised, less common presentations within thoracic endometriosis syndrome.

20. How soon after symptoms start should thoracic endometriosis be evaluated?

Given the risk of a serious pneumothorax event, any recurrent, cycle-linked chest symptoms should be evaluated promptly rather than delayed.

21. Can a gynaecologist help even if the surgery itself is done by a thoracic surgeon?

Yes, gynaecological evaluation, hormonal management, and coordination with your thoracic surgery team are all valuable parts of comprehensive care for this condition.

22. Where can I get gynaecological evaluation and coordinated care for suspected thoracic endometriosis in Hyderabad?

Sree Swapna Fertility Centre can evaluate for associated pelvic endometriosis, manage hormonal treatment, and coordinate referral to thoracic surgery at both our Kondapur and Attapur clinics.

Conclusion

Diaphragmatic endometriosis is rare, but recognising its distinctive cyclical pattern — chest symptoms tied closely to your period — can meaningfully shorten the path to proper diagnosis. Treating it well requires genuine coordination between thoracic surgery and gynaecological hormonal management, not one specialty working in isolation.

Get Coordinated Care for Suspected Thoracic Endometriosis

Dr. Swapna Naik and the team at Sree Swapna Fertility Centre can help evaluate your symptoms and coordinate the right multidisciplinary care.

📞 Call: +91 76708 04424 / +91 40 4995 3719 💬 WhatsApp: Message us directly 📧 Email: sreeswapna.fertility@gmail.com 📍 Visit us at: Kondapur or Attapur, Hyderabad 🌐 Book an appointment: sreeswapnaivf.com/contact-us

Author: Swapna

If you’ve been prescribed dienogest for endometriosis, you might be wondering how a single daily tablet is meant to manage a condition as complex as endometriosis. It’s a fair question, and the answer lies in how specifically this medication targets the biology of endometriosis tissue.

This guide explains how dienogest works, what results you can realistically expect, and the side effects worth knowing about.

What Is Dienogest?

Dienogest is a fourth-generation progestin, specifically studied and approved for the treatment of endometriosis-associated pain. Unlike combined hormonal contraceptives (which contain both oestrogen and progestin), dienogest is a progestin-only medication, typically taken as a 2mg tablet once daily.

How Does Dienogest Work?

Dienogest works through several mechanisms that specifically target endometriosis tissue:

  • Reduces hormonal stimulation: It mildly suppresses FSH and LH (reproductive hormones), reducing ovarian activity without fully shutting down hormone production
  • Shrinks endometrial tissue: It induces a process where endometrial-like tissue first changes (decidualises) and then gradually atrophies (shrinks)
  • Reduces inflammation: It inhibits several inflammatory pathways involved in endometriosis-related pain
  • Limits blood supply to lesions: It reduces angiogenesis (new blood vessel formation) that endometriosis tissue depends on to grow
  • Promotes cell death in lesions: It increases apoptosis (programmed cell death) specifically in endometriotic tissue

This multi-pronged action is why dienogest can meaningfully reduce both pain and, over time, the size of certain endometriosis-related growths like ovarian endometriomas.

What Results Can You Expect?

Research on dienogest shows consistent, meaningful improvement across multiple endometriosis symptoms:

  • Significant reduction in period pain (dysmenorrhoea)
  • Reduced pain during intercourse (dyspareunia)
  • Improvement in painful bowel movements and chronic pelvic pain, including in deep infiltrating endometriosis
  • Gradual shrinkage of ovarian endometriomas over 6–12 months of treatment in some studies, with continued reduction over longer-term use
  • High treatment continuation rates — around 80% of patients continuing treatment at 12 months in some studies, with many continuing well beyond that

Importantly, these benefits tend to build over time rather than appearing immediately, so dienogest is generally considered a longer-term management strategy rather than a quick fix.

How Does Dienogest Compare to Other Hormonal Options?

  • Compared to GnRH agonists (another common endometriosis treatment): research has found dienogest similarly effective for pain relief, but without the more significant hypoestrogenic side effects (like bone density loss) that limit GnRH agonists to short-term use
  • Compared to combined hormonal contraceptives: dienogest doesn’t carry the same thrombosis (blood clot) risk associated with oestrogen-containing options, making it a suitable choice even for women over 40

This is one of dienogest’s genuine advantages — it’s generally considered appropriate for longer-term, continuous use, sometimes until menopause, without the same restrictions seen with other hormonal treatments.

Common Side Effects

  • Irregular or abnormal uterine bleeding — the most commonly reported side effect, which tends to decrease as treatment continues
  • Headache
  • Weight gain
  • Reduced libido
  • Mood changes, in some patients
  • Decreased bone mineral density, reported in a subset of patients with longer-term use, which is why some doctors monitor bone density periodically during extended treatment

Most side effects that lead to discontinuation tend to occur during the first year of treatment, with better tolerability generally seen in those who continue beyond that point.

Does Dienogest Affect Future Fertility?

Ovulation typically resumes fairly quickly after stopping dienogest, which is relevant if you’re using it for symptom management now but planning pregnancy later. That said, dienogest itself isn’t a fertility treatment — it manages symptoms and disease activity, and a separate conversation about fertility timing is worth having with your doctor if pregnancy is part of your plans.

Who Might Not Be a Good Candidate for Dienogest?

Your doctor will consider your full medical history before prescribing dienogest, including any history of blood clotting disorders, liver conditions, or other contraindications specific to progestin-only medications. This is a decision made individually with your specialist, not a one-size-fits-all recommendation.

Dienogest Treatment at Sree Swapna Fertility Centre

Dr. Swapna Naik, Clinical Director at Sree Swapna Fertility Centre, brings over 15 years of experience in gynaecology and reproductive medicine, and considers dienogest as one option within a broader endometriosis management plan — alongside other hormonal options, and surgical treatment when medication alone isn’t sufficient.

At both our Kondapur and Attapur clinics, treatment decisions are individualised based on your specific symptoms, endometriosis type, and fertility plans, with regular follow-up to monitor how you’re responding and adjust the approach if needed.

Frequently Asked Questions

1. What is dienogest used for?

It’s a progestin specifically studied and used for managing endometriosis-associated pain and related symptoms.

2. How is dienogest typically taken?

It’s usually taken as a 2mg tablet once daily, though your doctor will confirm the right dosing for your specific situation.

3. How does dienogest reduce endometriosis symptoms?

It reduces hormonal stimulation of endometrial tissue, decreases inflammation, limits blood supply to lesions, and promotes shrinkage of endometriotic tissue over time.

4. How long does it take to see results with dienogest?

Benefits generally build over months rather than appearing immediately, with continued improvement often seen over 6–12 months or longer.

5. Can dienogest shrink ovarian endometriomas (chocolate cysts)?

Yes, some studies show gradual reduction in endometrioma size over 6–12 months of treatment, with further reduction over longer-term use.

6. What are the most common side effects of dienogest?

Irregular uterine bleeding is the most commonly reported side effect, along with headache, weight gain, and reduced libido in some patients.

7. Does dienogest carry a blood clot risk like combined birth control pills?

No, dienogest doesn’t carry the same thrombosis risk associated with oestrogen-containing hormonal contraceptives.

8. Can women over 40 use dienogest?

Yes, since it doesn’t carry the same thrombotic risk as combined hormonal contraceptives, it’s often considered a suitable option for this age group.

9. How does dienogest compare to GnRH agonists for endometriosis?

Research suggests comparable pain relief efficacy, but dienogest doesn’t cause the same degree of bone density loss that limits GnRH agonists to shorter-term use.

10. Can dienogest be used long-term?

Yes, studies have followed patients on dienogest for several years, showing continued efficacy and generally manageable side effects with ongoing use.

11. Does dienogest affect bone density?

A subset of patients using dienogest long-term have shown some reduction in bone density in certain studies, which is why periodic monitoring may be recommended for extended use.

12. Will I be able to get pregnant after stopping dienogest?

Ovulation typically resumes fairly quickly after stopping, though dienogest itself isn’t a fertility treatment — a separate conversation about conception timing is worthwhile.

13. Does dienogest stop periods completely?

Many patients experience reduced bleeding or amenorrhea (absence of periods) with continued use, though irregular bleeding, especially early in treatment, is common.

14. Is dienogest effective for deep infiltrating endometriosis specifically?

Yes, research has shown significant symptom improvement with dienogest across endometriosis types, including deep infiltrating disease.

15. What happens if I miss a dose of dienogest?

Follow your doctor’s specific guidance on missed doses, since consistency matters for its effectiveness in managing symptoms.

16. Can dienogest be taken vaginally instead of orally?

In some cases, particularly for patients with gastrointestinal symptoms, vaginal administration has shown similar efficacy and tolerability to oral use, though this should be discussed with your doctor.

17. Is dienogest the same as birth control pills?

No, dienogest is a progestin-only medication specifically studied for endometriosis, different from combined oestrogen-progestin birth control pills.

18. Can dienogest cause weight gain?

Yes, weight gain has been reported as a side effect in some patients, though it doesn’t occur in everyone.

19. Is dienogest safe for adolescents with endometriosis?

Some research supports its use in adolescents, including at lower doses, with studies showing it’s generally well tolerated without significant impact on bone turnover during short-term use.

20. Do side effects typically improve over time on dienogest?

Yes, particularly irregular bleeding, which tends to decrease the longer treatment continues, and side effects severe enough to stop treatment are more common in the first year.

21. Can dienogest be combined with surgery for endometriosis?

Yes, it’s often used alongside surgical treatment, either before surgery, after surgery to reduce recurrence risk, or as an ongoing management option when surgery isn’t immediately needed.

22. Where can I get a personalised endometriosis treatment plan including dienogest in Hyderabad?

Sree Swapna Fertility Centre offers comprehensive endometriosis evaluation and individualised treatment planning, including hormonal options like dienogest, at both our Kondapur and Attapur clinics.

Conclusion

Dienogest offers a genuinely effective, well-studied option for managing endometriosis symptoms, with the advantage of being suitable for longer-term use without some of the restrictions seen with other hormonal treatments. Like any medication, it comes with side effects worth understanding and monitoring — and it works best as part of a broader, personalised treatment plan rather than a stand-alone solution.

Discuss Whether Dienogest Is Right for You

Dr. Swapna Naik and the team at Sree Swapna Fertility Centre can help determine whether dienogest fits into your personalised endometriosis treatment plan.

📞 Call: +91 76708 04424 / +91 40 4995 3719 💬 WhatsApp: Message us directly 📧 Email: sreeswapna.fertility@gmail.com 📍 Visit us at: Kondapur (flagship centre) or Attapur, Hyderabad 🌐 Book an appointment: sreeswapnaivf.com/contact-us

Author: Swapna

For decades, if you wanted a confirmed endometriosis diagnosis, surgery was considered essential. That’s changed — significantly — and it’s worth understanding why, especially if a doctor has mentioned laparoscopy to you as a next step.

This guide explains what diagnostic laparoscopy actually involves, how its role has shifted in recent years, and when it’s genuinely still the right choice today.

What Is Diagnostic Laparoscopy?

Diagnostic laparoscopy is a minimally invasive surgical procedure where a thin, lighted camera (laparoscope) is inserted through a small incision near the navel, allowing direct visualisation of the pelvic organs — including any visible endometriosis lesions, adhesions, or structural abnormalities.

Historically, this direct visual and tissue-sample (biopsy) confirmation was considered the only truly definitive way to diagnose endometriosis.

What Has Changed: Laparoscopy Is No Longer the “Gold Standard”

This is genuinely important to understand. In 2022, the European Society of Human Reproduction and Embryology (ESHRE) updated its clinical guidelines, moving away from laparoscopy as the diagnostic gold standard for endometriosis. Instead, imaging — transvaginal ultrasound and MRI — is now recommended as the first-line approach, with laparoscopy reserved for more specific situations.

This shift happened for good reason. Requiring surgery before diagnosis contributed to a well-documented, lengthy diagnostic delay — historically averaging 7 to 10 years between first symptoms and confirmed diagnosis. Meanwhile, advances in ultrasound technique (particularly a standardised, detailed protocol for evaluating the pelvis) have shown diagnostic accuracy for ovarian and deep endometriosis that’s now considered comparable to surgical visualisation in experienced hands.

When Is Diagnostic Laparoscopy Still Recommended?

Despite this shift, laparoscopy remains genuinely important in specific circumstances:

  • Negative imaging with ongoing, unexplained symptoms: If ultrasound and/or MRI don’t show clear findings, but symptoms persist and haven’t responded to initial hormonal treatment, laparoscopy may still be recommended
  • Suspected superficial endometriosis: This form is harder to detect on imaging than deep or ovarian endometriosis, so laparoscopy remains relevant when superficial disease is suspected despite negative imaging
  • Atypical ovarian masses: If an ovarian cyst has features on imaging that raise concern for malignancy rather than a straightforward endometrioma, surgery may be needed to clarify the diagnosis
  • Alongside planned therapeutic surgery: If you’re already having surgery to treat suspected endometriosis (rather than purely to diagnose it), biopsy and confirmation naturally happen during that same procedure

Importantly, current guidelines note that even a negative laparoscopy doesn’t fully rule out endometriosis either — no single test is considered perfectly definitive.

What Happens During Diagnostic Laparoscopy?

  1. Anaesthesia: General anaesthesia is used
  2. Access: A small incision is made near the navel, and the abdomen is gently inflated with gas to create working space
  3. Visualisation: The laparoscope allows direct viewing of the uterus, ovaries, fallopian tubes, and surrounding pelvic structures
  4. Biopsy: If suspicious tissue is identified, a small sample is taken for histological confirmation
  5. Additional treatment, if needed: In many cases, if endometriosis is found, your surgeon may treat visible lesions during the same procedure, rather than performing a purely diagnostic surgery and a separate treatment surgery later

What Does Recovery Look Like?

  • Typically a same-day or overnight procedure, depending on findings and any additional treatment performed
  • Mild shoulder or abdominal discomfort from the gas used during the procedure, usually resolving within a few days
  • Most people return to normal activities within about a week, though this varies based on what was done during surgery

Why the Imaging-First Approach Matters for You

If you’re currently experiencing symptoms that suggest endometriosis, understanding this shift matters practically: a thorough ultrasound evaluation — ideally using a detailed, standardised scanning protocol — should generally come first, not surgery. This avoids unnecessary surgical risk and delay when imaging alone can often provide a confident diagnosis, particularly for ovarian and deep endometriosis.

Diagnostic Approach at Sree Swapna Fertility Centre

We follow current, evidence-based guidance rather than defaulting to surgery as a first step.

Dr. Swapna Naik, Clinical Director at Sree Swapna Fertility Centre, is a trained laparoscopic surgeon with over 15 years of experience, and our approach begins with thorough transvaginal ultrasound evaluation at both our Kondapur and Attapur clinics. Laparoscopy is recommended when imaging findings are inconclusive, symptoms persist despite initial treatment, or when therapeutic surgery is already planned — not as a routine first step for every suspected case.

Frequently Asked Questions

1. Is diagnostic laparoscopy still the gold standard for diagnosing endometriosis?

No, since 2022, updated international guidelines recommend imaging (ultrasound and/or MRI) as the first-line diagnostic approach, with laparoscopy reserved for specific situations.

2. Why did the approach to diagnosing endometriosis change?

Requiring surgery before diagnosis contributed to lengthy diagnostic delays, while imaging technology has improved enough to reliably detect ovarian and deep endometriosis in many cases.

3. When is laparoscopy still recommended for endometriosis diagnosis?

When imaging is negative but symptoms persist despite treatment, when superficial endometriosis is suspected, when an ovarian mass has atypical features, or alongside planned therapeutic surgery.

4. Can imaging alone confirm all types of endometriosis?

Not entirely — ultrasound and MRI are quite accurate for ovarian and deep endometriosis, but superficial endometriosis remains harder to detect through imaging alone.

5. Does a negative laparoscopy rule out endometriosis completely?

No, current guidelines note that even laparoscopy isn’t considered a perfectly definitive test — a negative result doesn’t fully exclude the condition.

6. What happens during diagnostic laparoscopy?

A thin camera is inserted through a small incision to directly visualise pelvic organs, with biopsy of any suspicious tissue for confirmation.

7. Is diagnostic laparoscopy painful?

It’s performed under general anaesthesia, and post-procedure discomfort is generally mild, often related to the gas used during surgery rather than the incisions themselves.

8. How long does recovery take after diagnostic laparoscopy?

Most people return to normal activities within about a week, though this depends on what was done during the procedure.

9. Can treatment be done during the same procedure as diagnosis?

Yes, if endometriosis is visually confirmed during laparoscopy, many surgeons treat visible lesions during the same procedure rather than scheduling separate surgeries.

10. What is the IDEA protocol mentioned in relation to ultrasound?

It’s a standardised, detailed ultrasound scanning approach shown to improve diagnostic accuracy for endometriosis, particularly deep and ovarian disease.

11. Why was the historical diagnostic delay for endometriosis so long?

Because laparoscopy was considered necessary for confirmation, and surgery isn’t something patients or doctors pursue quickly or lightly, leading to significant average delays before diagnosis.

12. Should I ask for an ultrasound before considering laparoscopy?

Yes, current guidance supports starting with thorough imaging evaluation before considering surgical diagnosis, in most cases.

13. Is MRI ever needed in addition to ultrasound?

Yes, particularly when ultrasound findings are inconclusive, or for detailed surgical planning if deep endometriosis is suspected.

14. Can blood tests like CA-125 diagnose endometriosis?

No, current guidelines don’t recommend blood tests like CA-125 for diagnosing or excluding endometriosis.

15. What if my ultrasound is negative but I still have symptoms?

Discuss this with your doctor — options may include empirical hormonal treatment first, with laparoscopy considered if symptoms don’t improve.

16. Is diagnostic laparoscopy a day procedure?

It’s often done as a same-day or overnight procedure, depending on findings and whether additional treatment is performed.

17. Does an ovarian cyst always need laparoscopy to confirm it’s an endometrioma?

Not always — typical endometriomas can often be confidently identified on ultrasound alone, though atypical-appearing cysts may need surgical evaluation to rule out other causes.

18. Can superficial endometriosis be missed on ultrasound?

Yes, this is one of the main reasons laparoscopy remains relevant — superficial disease is harder to detect through imaging compared to deep or ovarian endometriosis.

19. Is empirical hormonal treatment an alternative to laparoscopy?

Yes, in some cases, a trial of hormonal treatment based on clinical suspicion is considered a reasonable alternative to immediate laparoscopy.

20. Does having laparoscopy always mean I’ll need further surgery later?

Not necessarily — if endometriosis is confirmed during a diagnostic procedure, treatment is often performed during that same surgery.

21. How experienced does a sonographer need to be for accurate endometriosis imaging?

Diagnostic accuracy for endometriosis on ultrasound is closely tied to the specific training and experience of the person performing the scan, since it requires a detailed, systematic approach.

22. Where can I get thorough endometriosis imaging evaluation in Hyderabad?

Sree Swapna Fertility Centre offers in-house transvaginal ultrasound evaluation at both our Kondapur and Attapur clinics, following current imaging-first diagnostic guidance.

Conclusion

Diagnostic laparoscopy hasn’t disappeared from endometriosis care, but its role has genuinely changed. Thorough imaging is now the appropriate starting point for most patients, with laparoscopy reserved for specific situations where imaging alone isn’t enough. Understanding this shift can help you have a more informed conversation with your doctor about what’s really needed for your diagnosis.

Start With a Thorough Evaluation

Dr. Swapna Naik and the team at Sree Swapna Fertility Centre follow an evidence-based, imaging-first approach to endometriosis diagnosis, reserving surgery for when it’s genuinely needed.

📞 Call: +91 76708 04424 / +91 40 4995 3719 💬 WhatsApp: Message us directly 📧 Email: sreeswapna.fertility@gmail.com 📍 Visit us at: Kondapur (flagship centre) or Attapur, Hyderabad 🌐 Book an appointment: sreeswapnaivf.com/contact-us

Scroll to Top

To Book an Appointment

+917670804424 📞 Call Now

Recent Posts